Hello, I am Dr. Peter C. Kang.
Today, I would like to share the case of a patient who came to improve contracture symptoms and a crooked nose that developed after multiple nasal surgeries.
📍 Surgical history
6 to 7 years ago: Ear cartilage + silicone implant surgery (tip swelling, hardening, cartilage show-through)
5 years ago: Silicone implant replacement + additional ear cartilage + septal surgery (recurrence of contracture symptoms)
4 years ago: Silicone implant removal + autologous dermis (buttock) + autologous rib cartilage + alar reduction surgery
2 years ago: Revision surgery on the nasal tip only with autologous rib cartilage
July-August of last year: nasal filler treatment for a low nasal bridge
🔎 Initial consultation findings
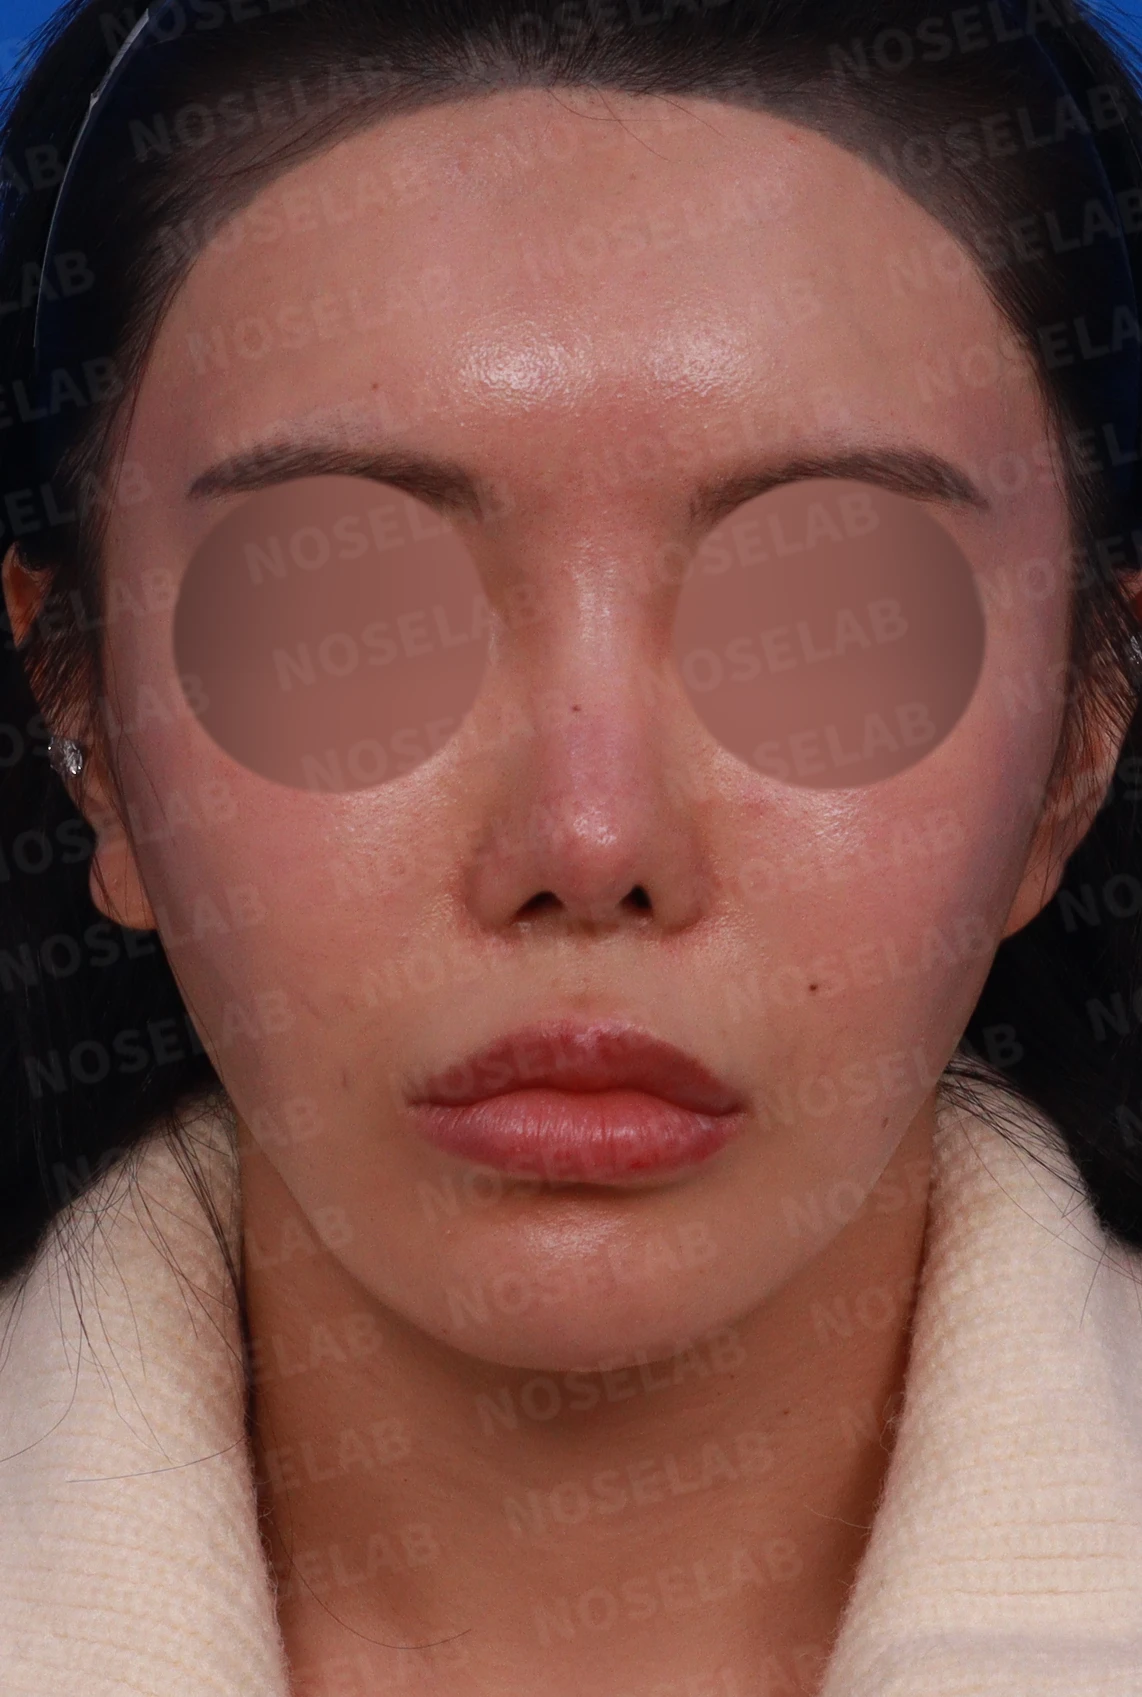
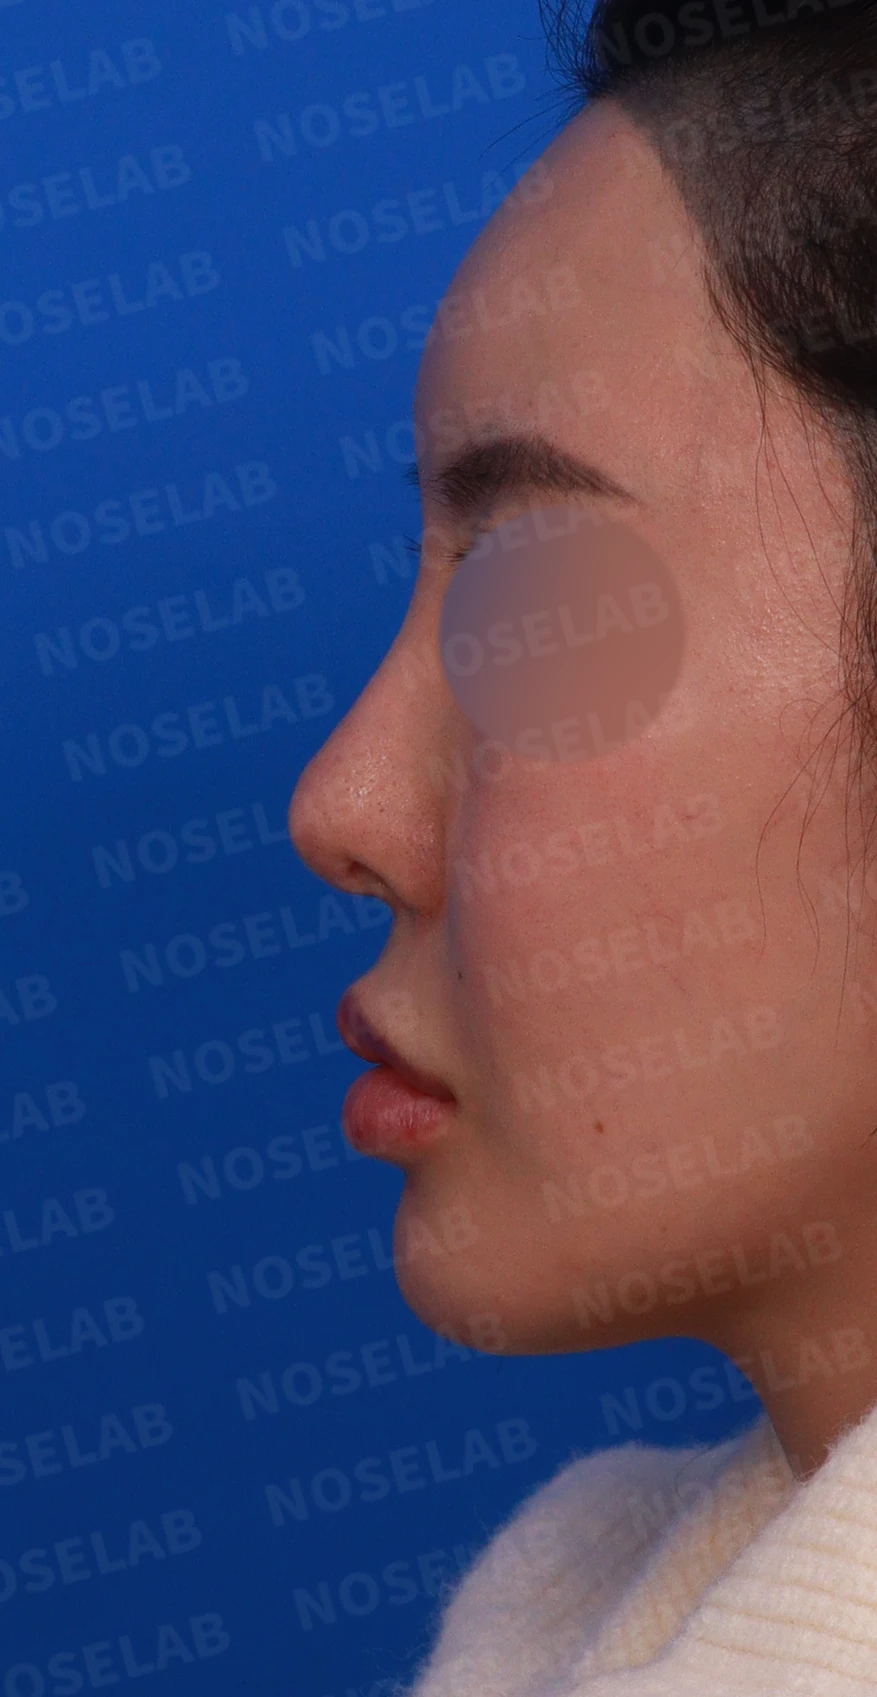
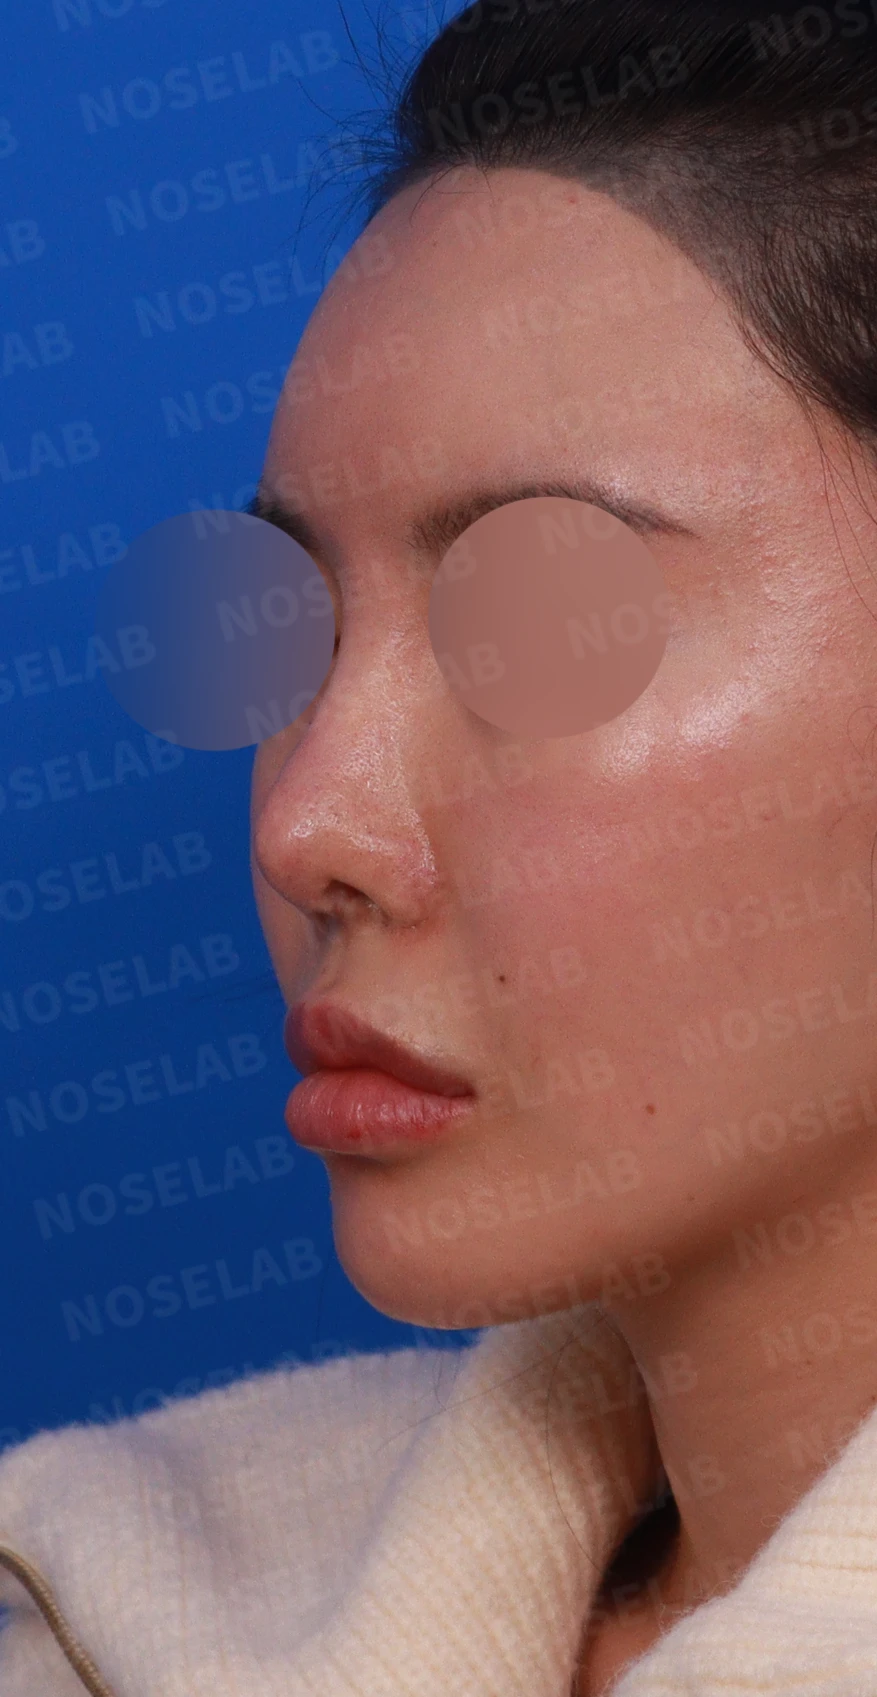
Front, left profile, and oblique views during design consultation
Front view
Deviated nose
Broadened nasal bridge due to foreign material
Bulbous nasal tip
Alar asymmetry
Nostril asymmetry (pinched left nostril)
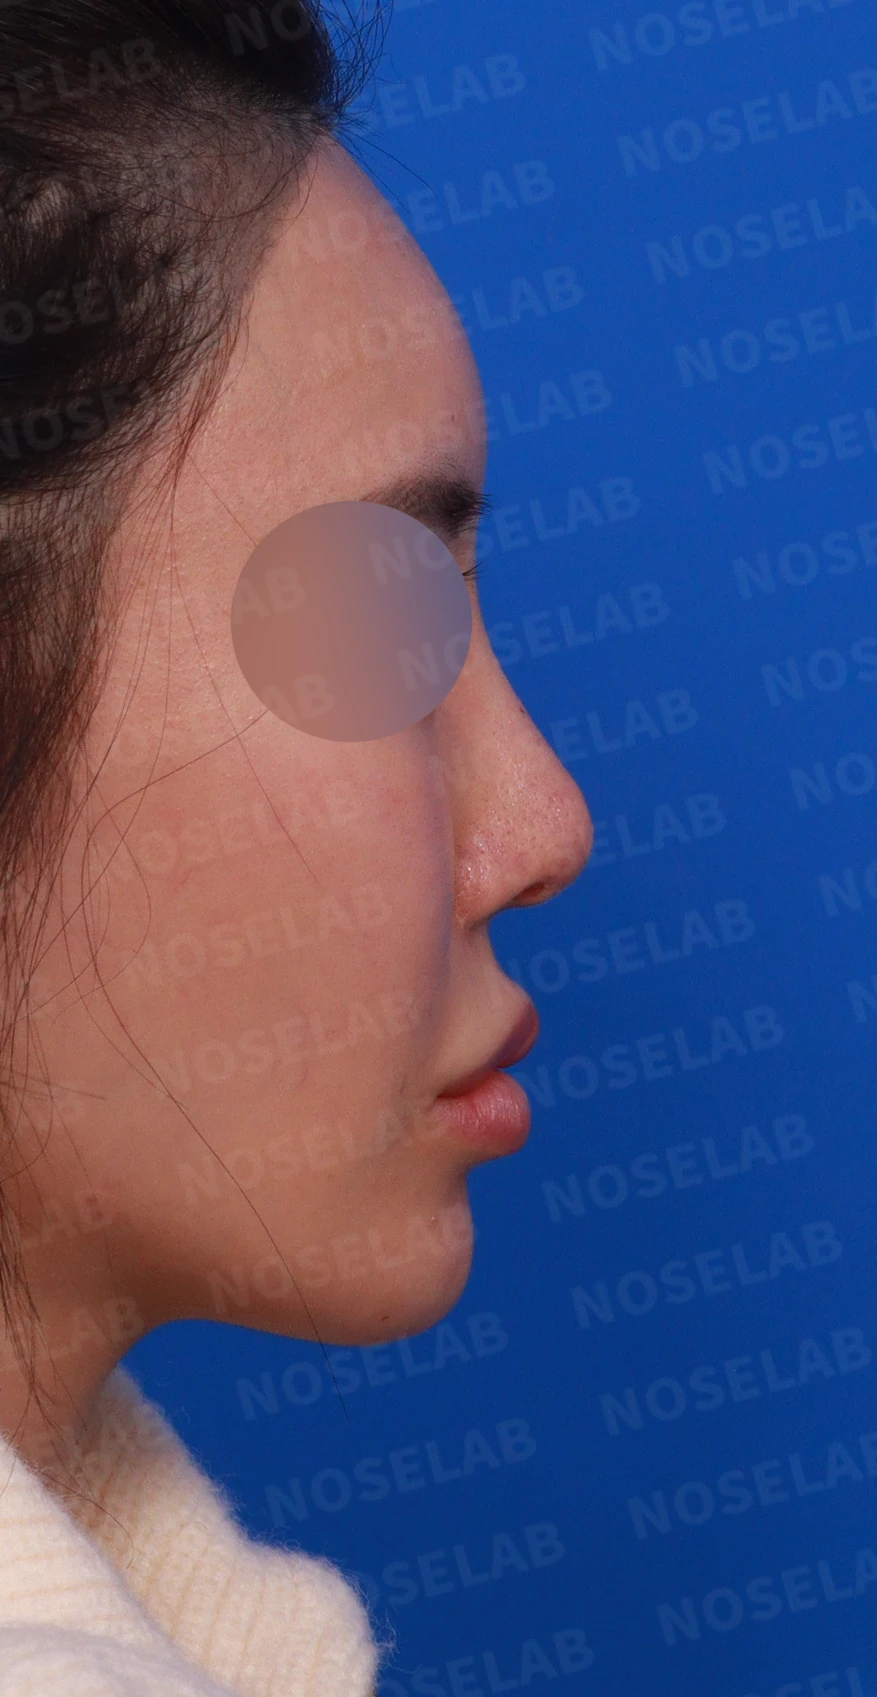
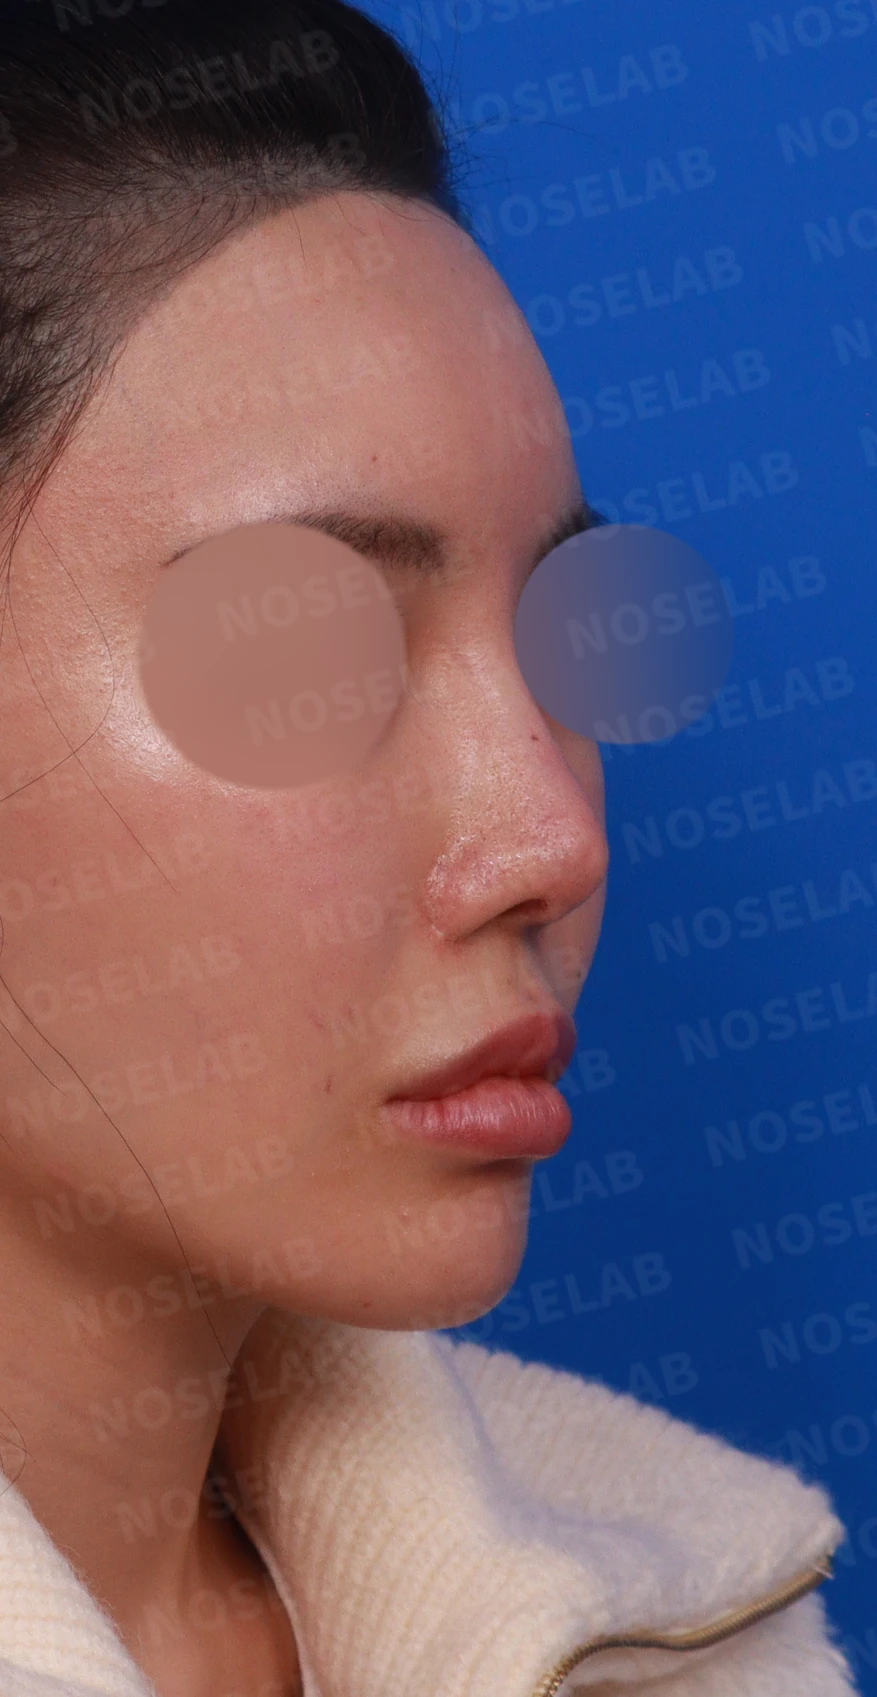
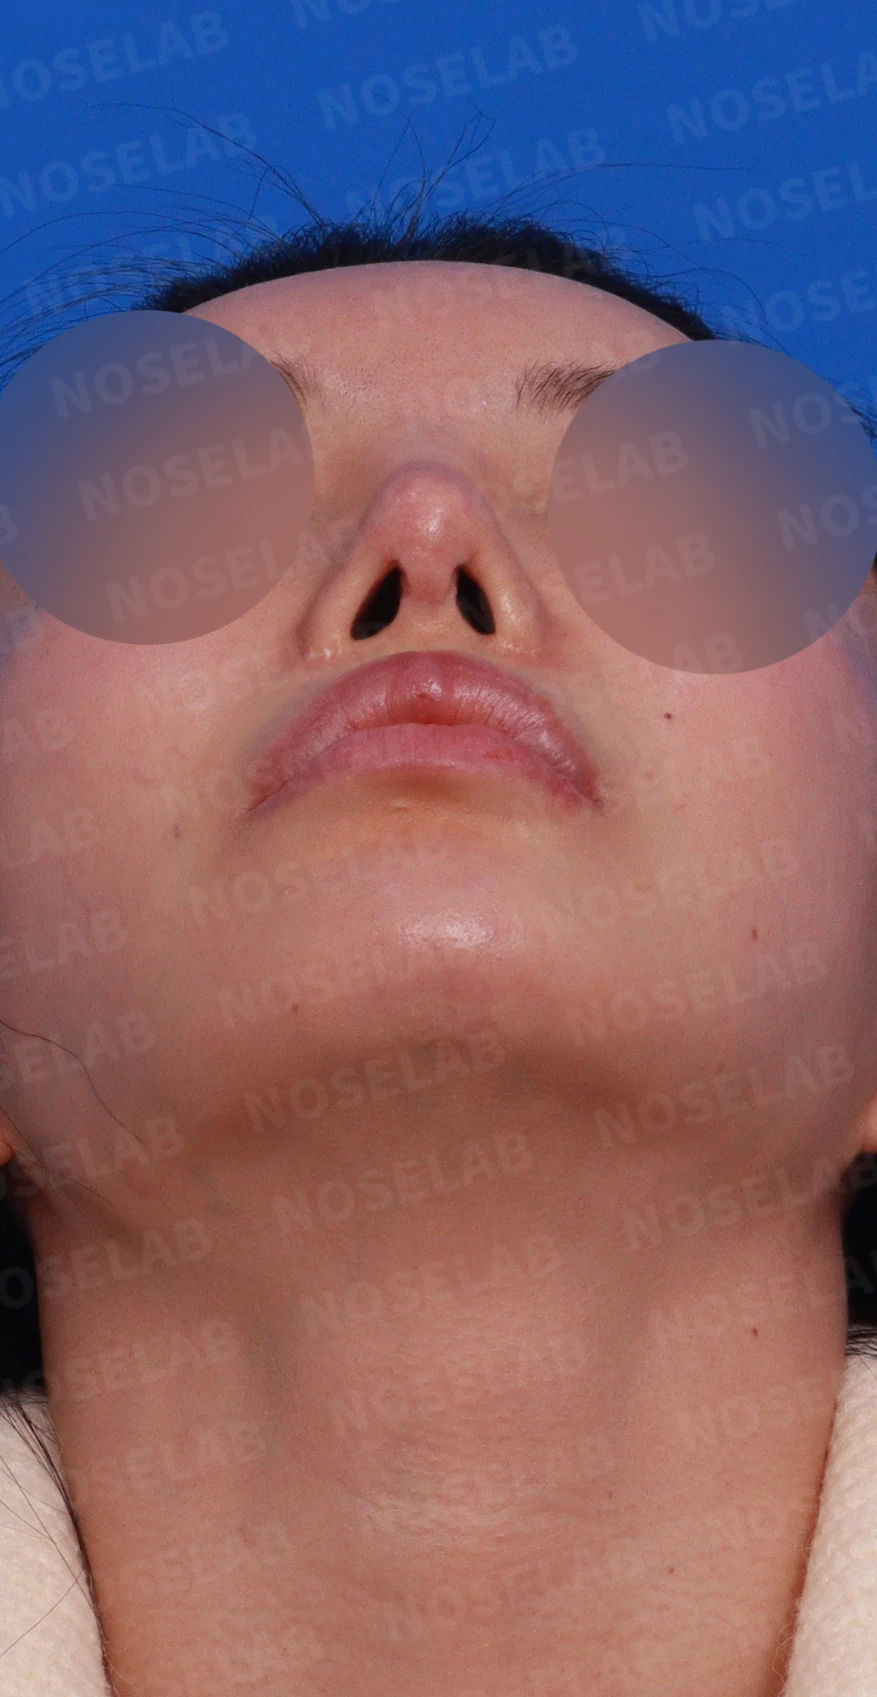
Design consultation: right oblique, profile, and basal (nostril) views
2. Profile view
High radix
Bulbous and drooping nasal tip
Acute nasolabial angle
Protruding mouth findings
3. Nostrils
Left nostril smaller than the right
Nostril asymmetry
✨ Patient's requests
Correction of deviated nose
Lowering the upturned tip (primary request)
Elevation of the nasal tip
Preference for silicone implant use
💉 Surgical procedure details
Structural improvement
Septal extension using autologous rib cartilage
Correction of the left nostril narrowed after alar reduction
Lateral repositioning of the ala
2. Shape improvement
Correction of crooked nose
Lowering the position of the nasal tip (top priority)
Adequate elevation of tip height
Slimming the broadened nasal bridge
3. Foreign material management
Removal of existing foreign material
Achieving balanced height using a silicone implant
Improvement of protruding mouth through nasolabial angle correction
✅ Surgical results
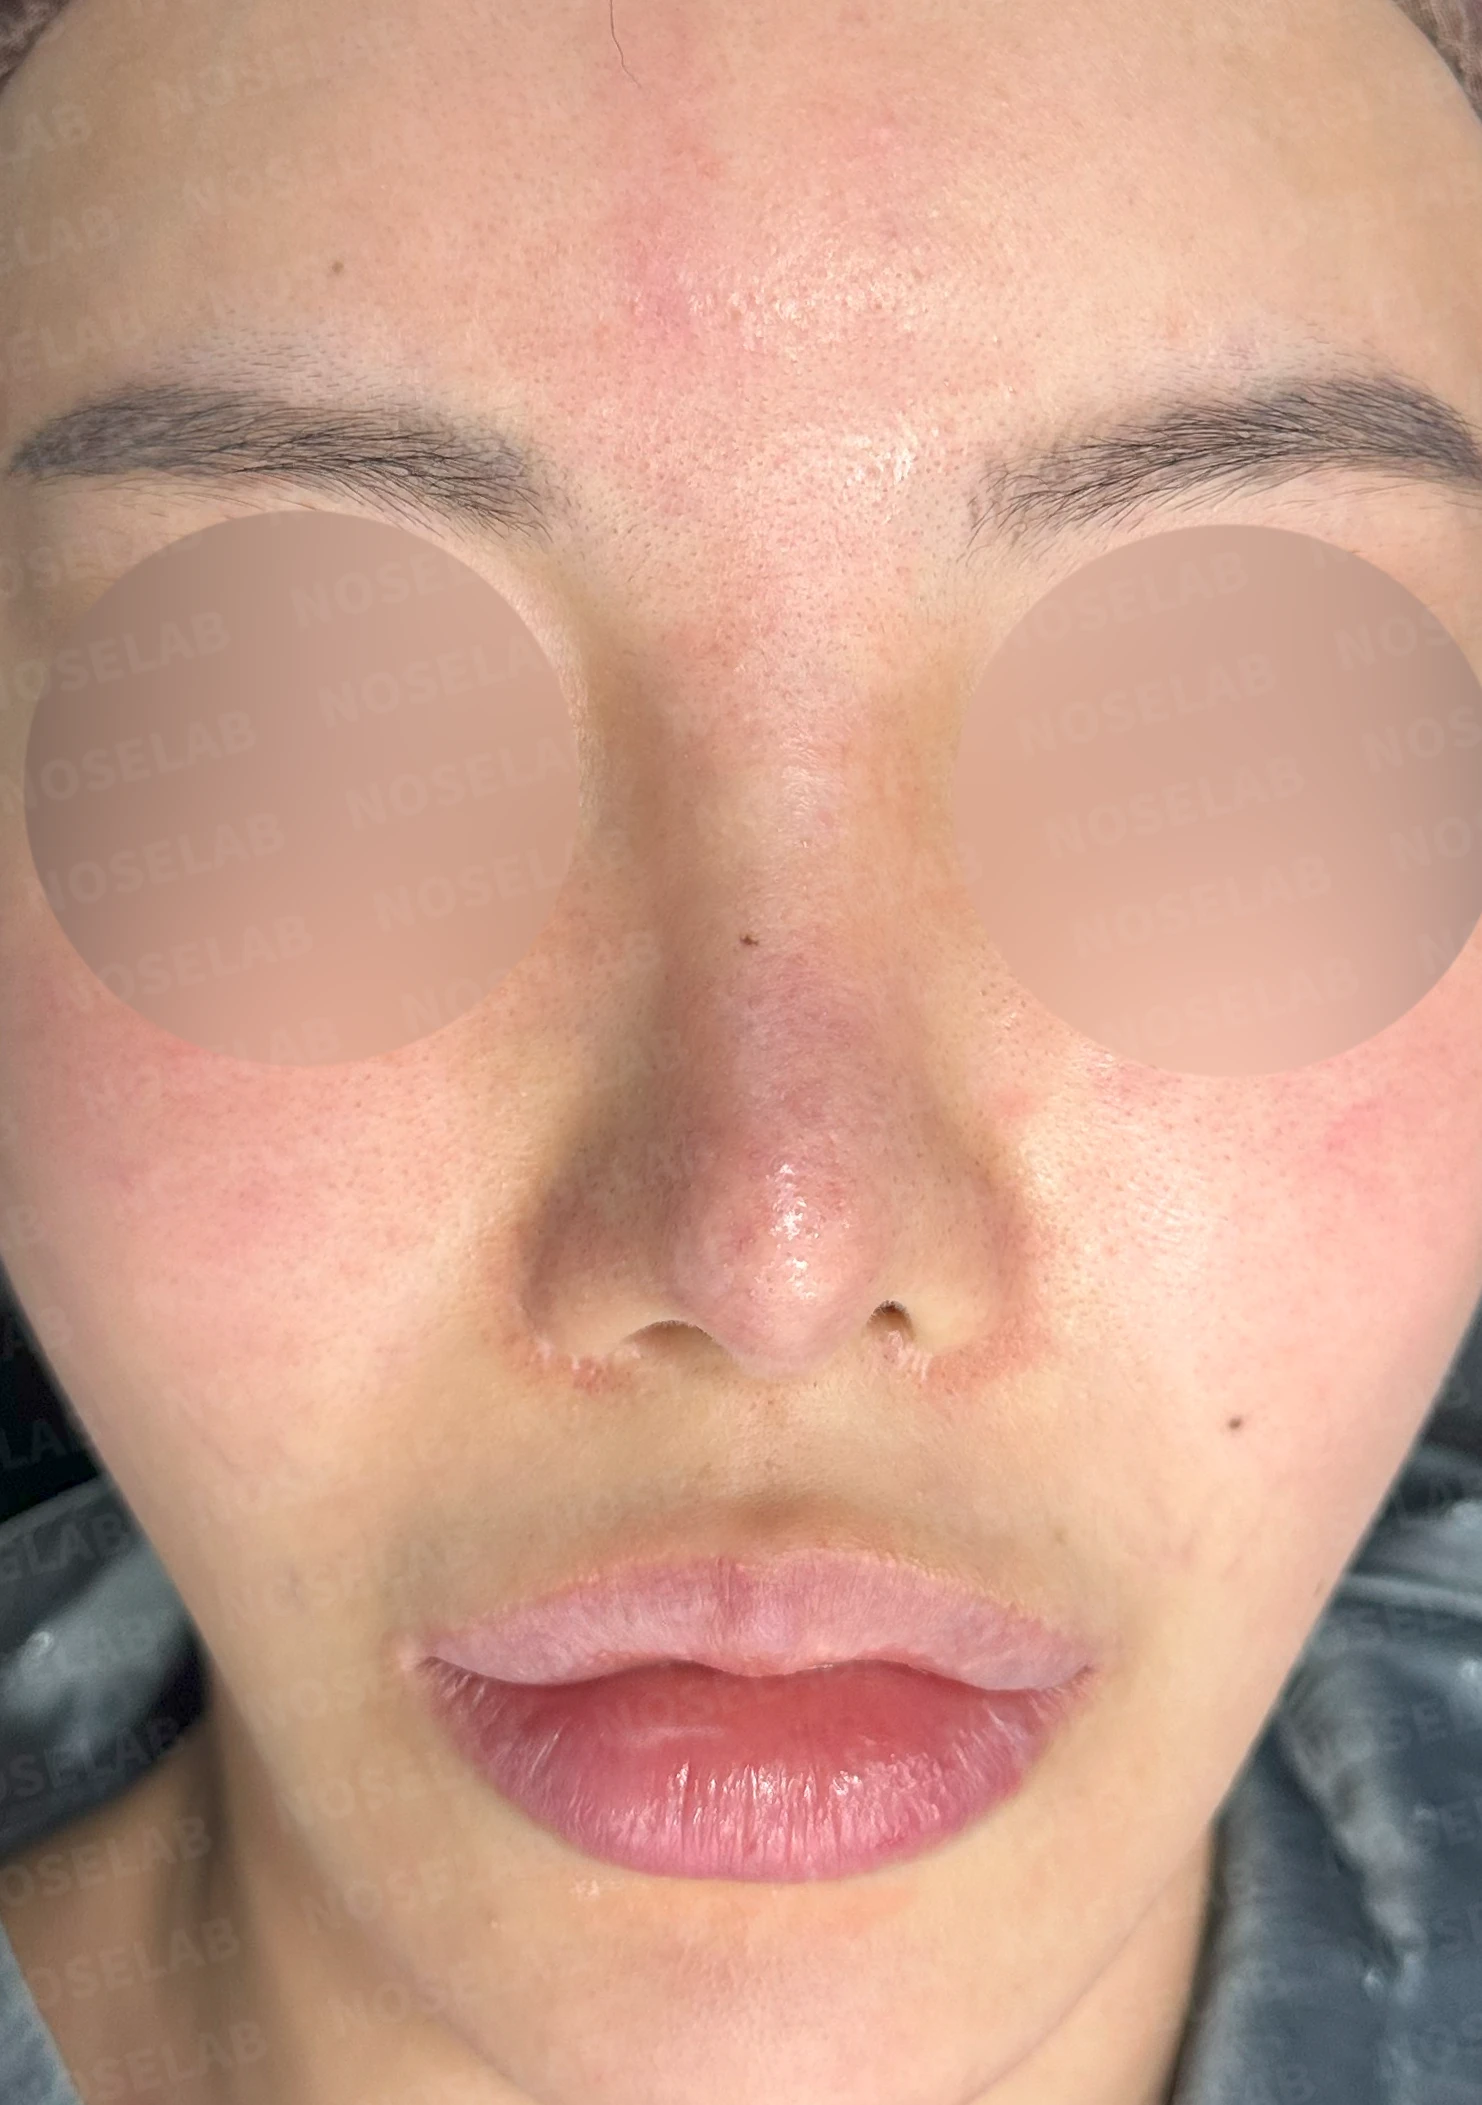
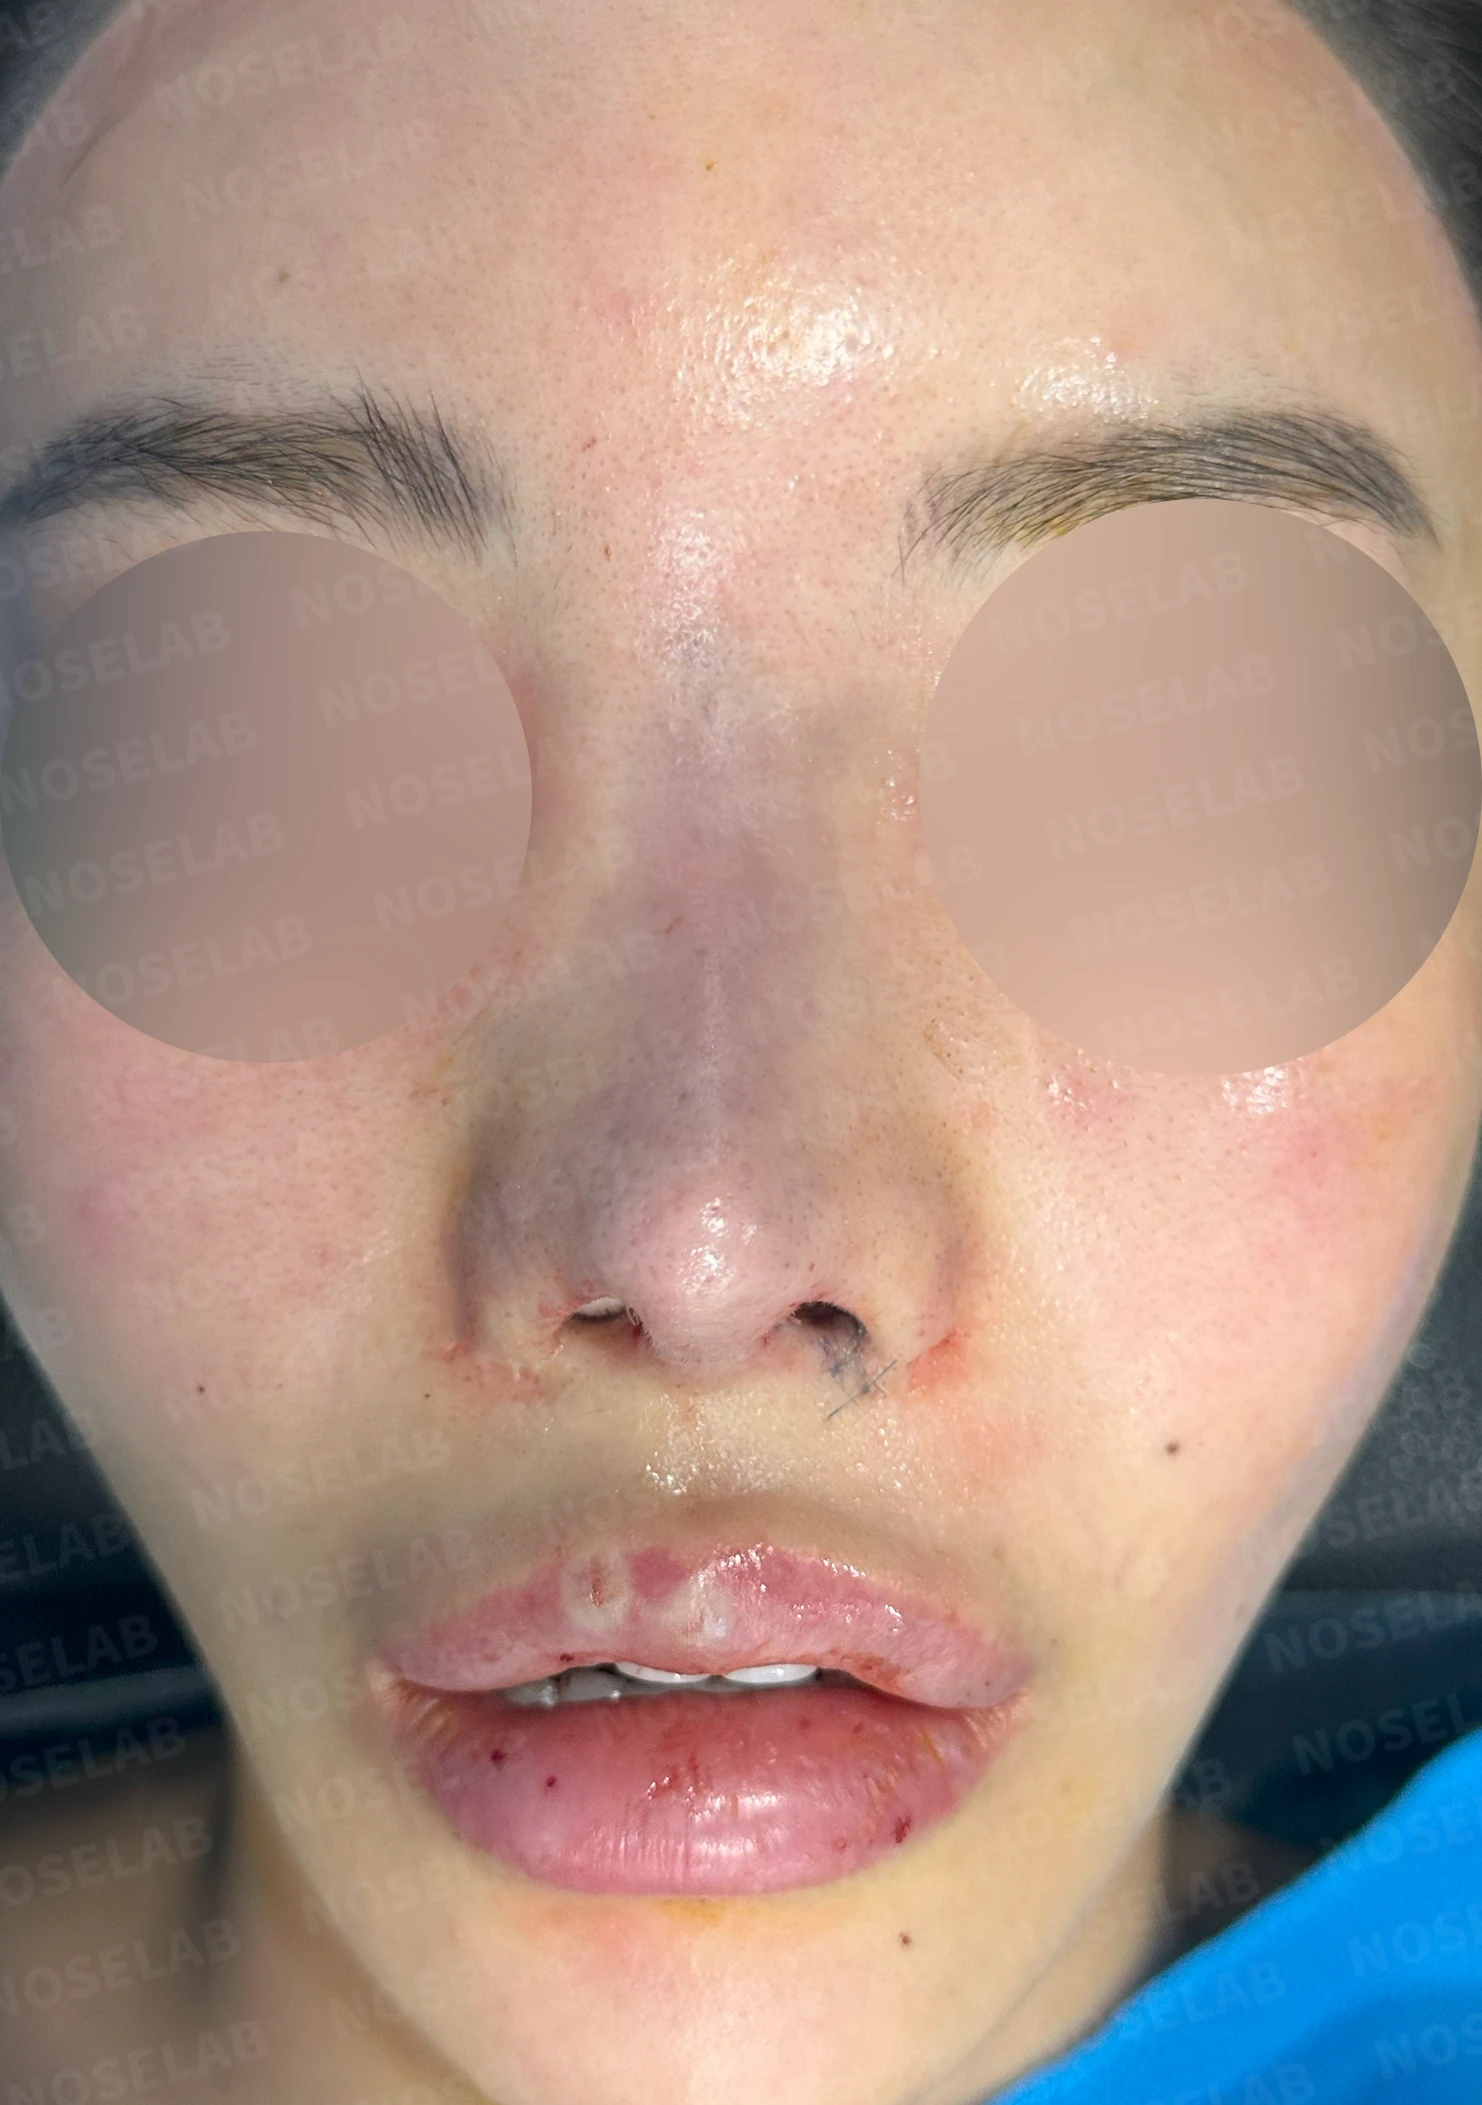
Front view
Crooked nose correction
Slimmer nasal bridge
Correction of the pinched left nostril
Restoration of the left ala

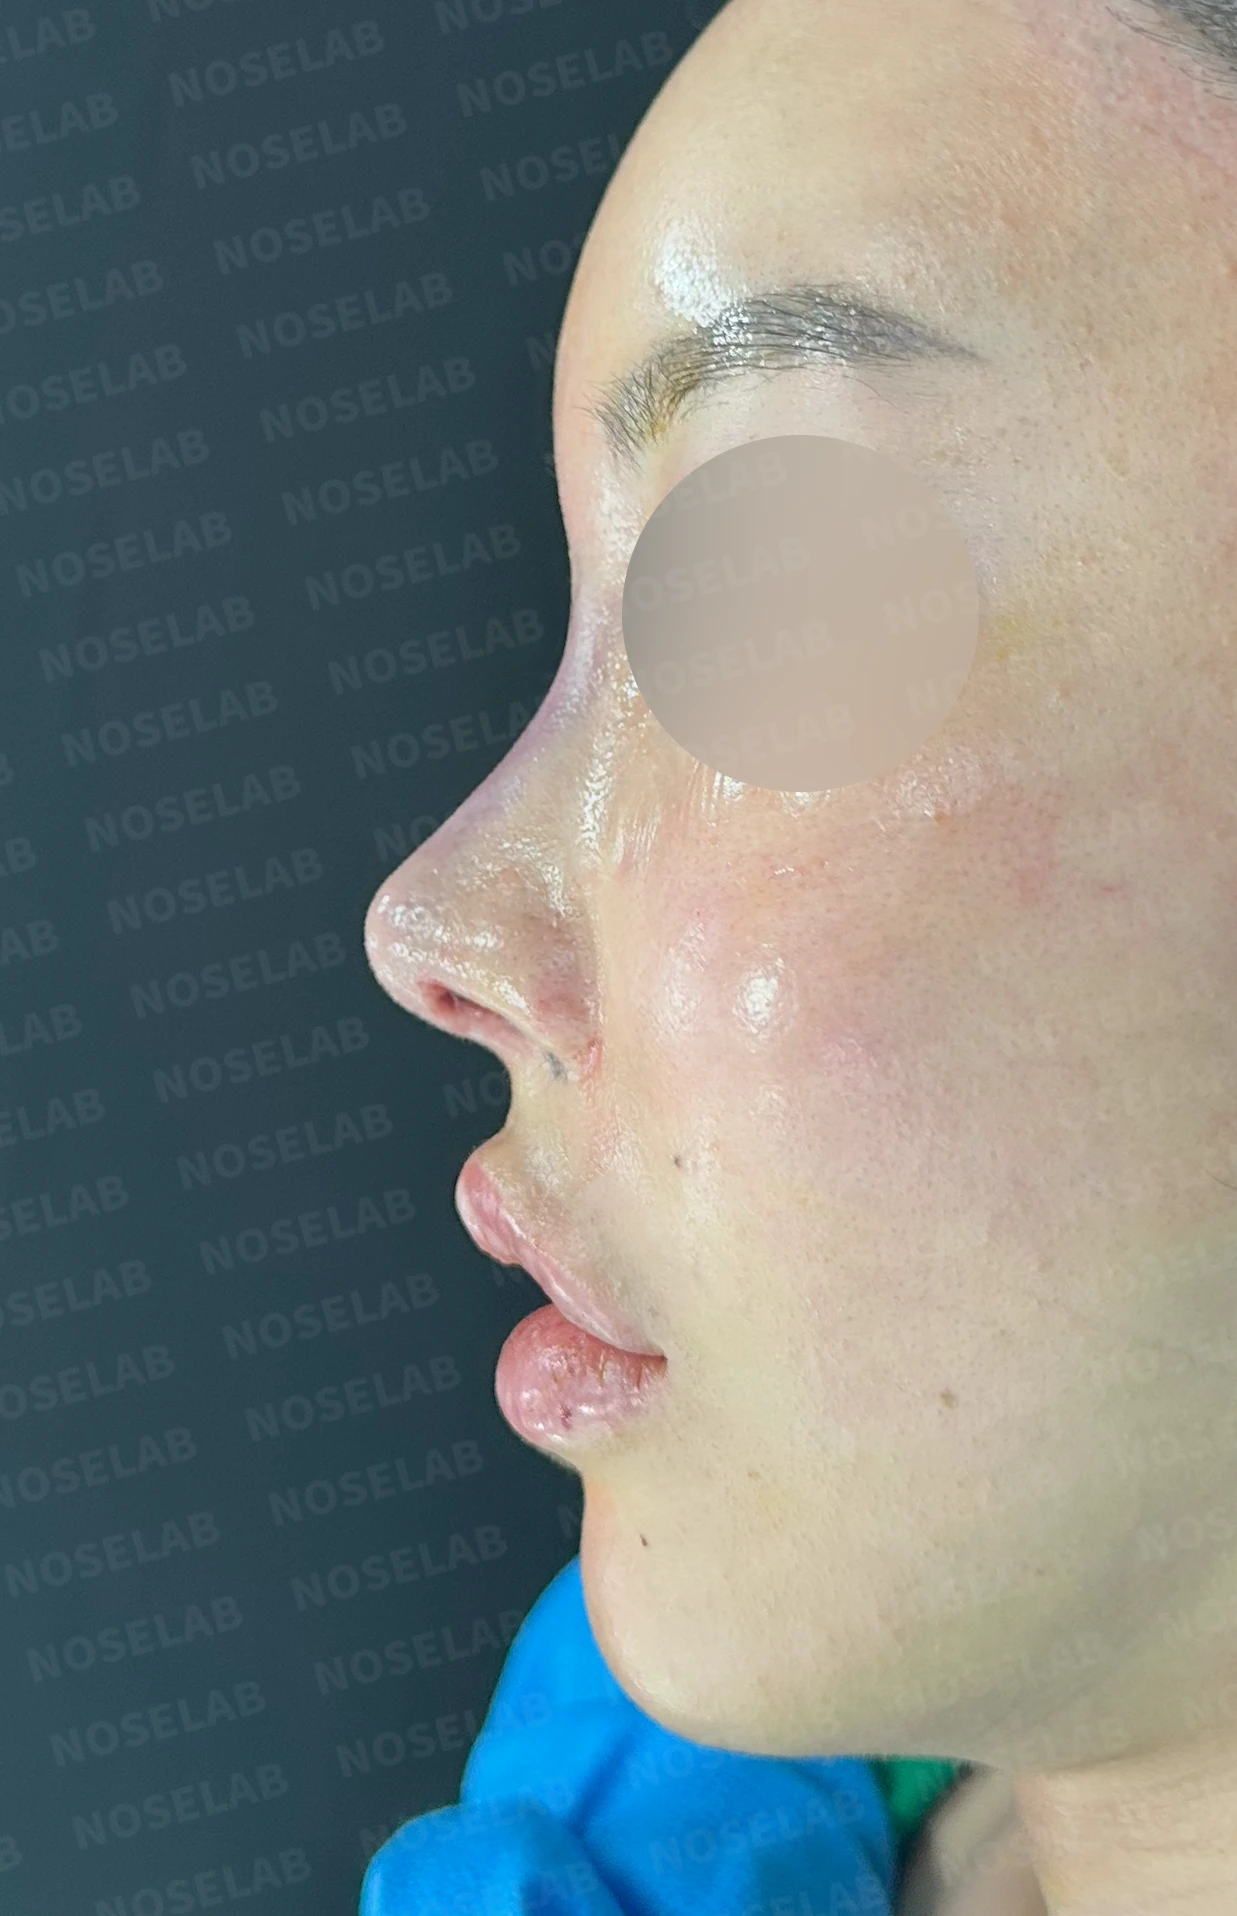
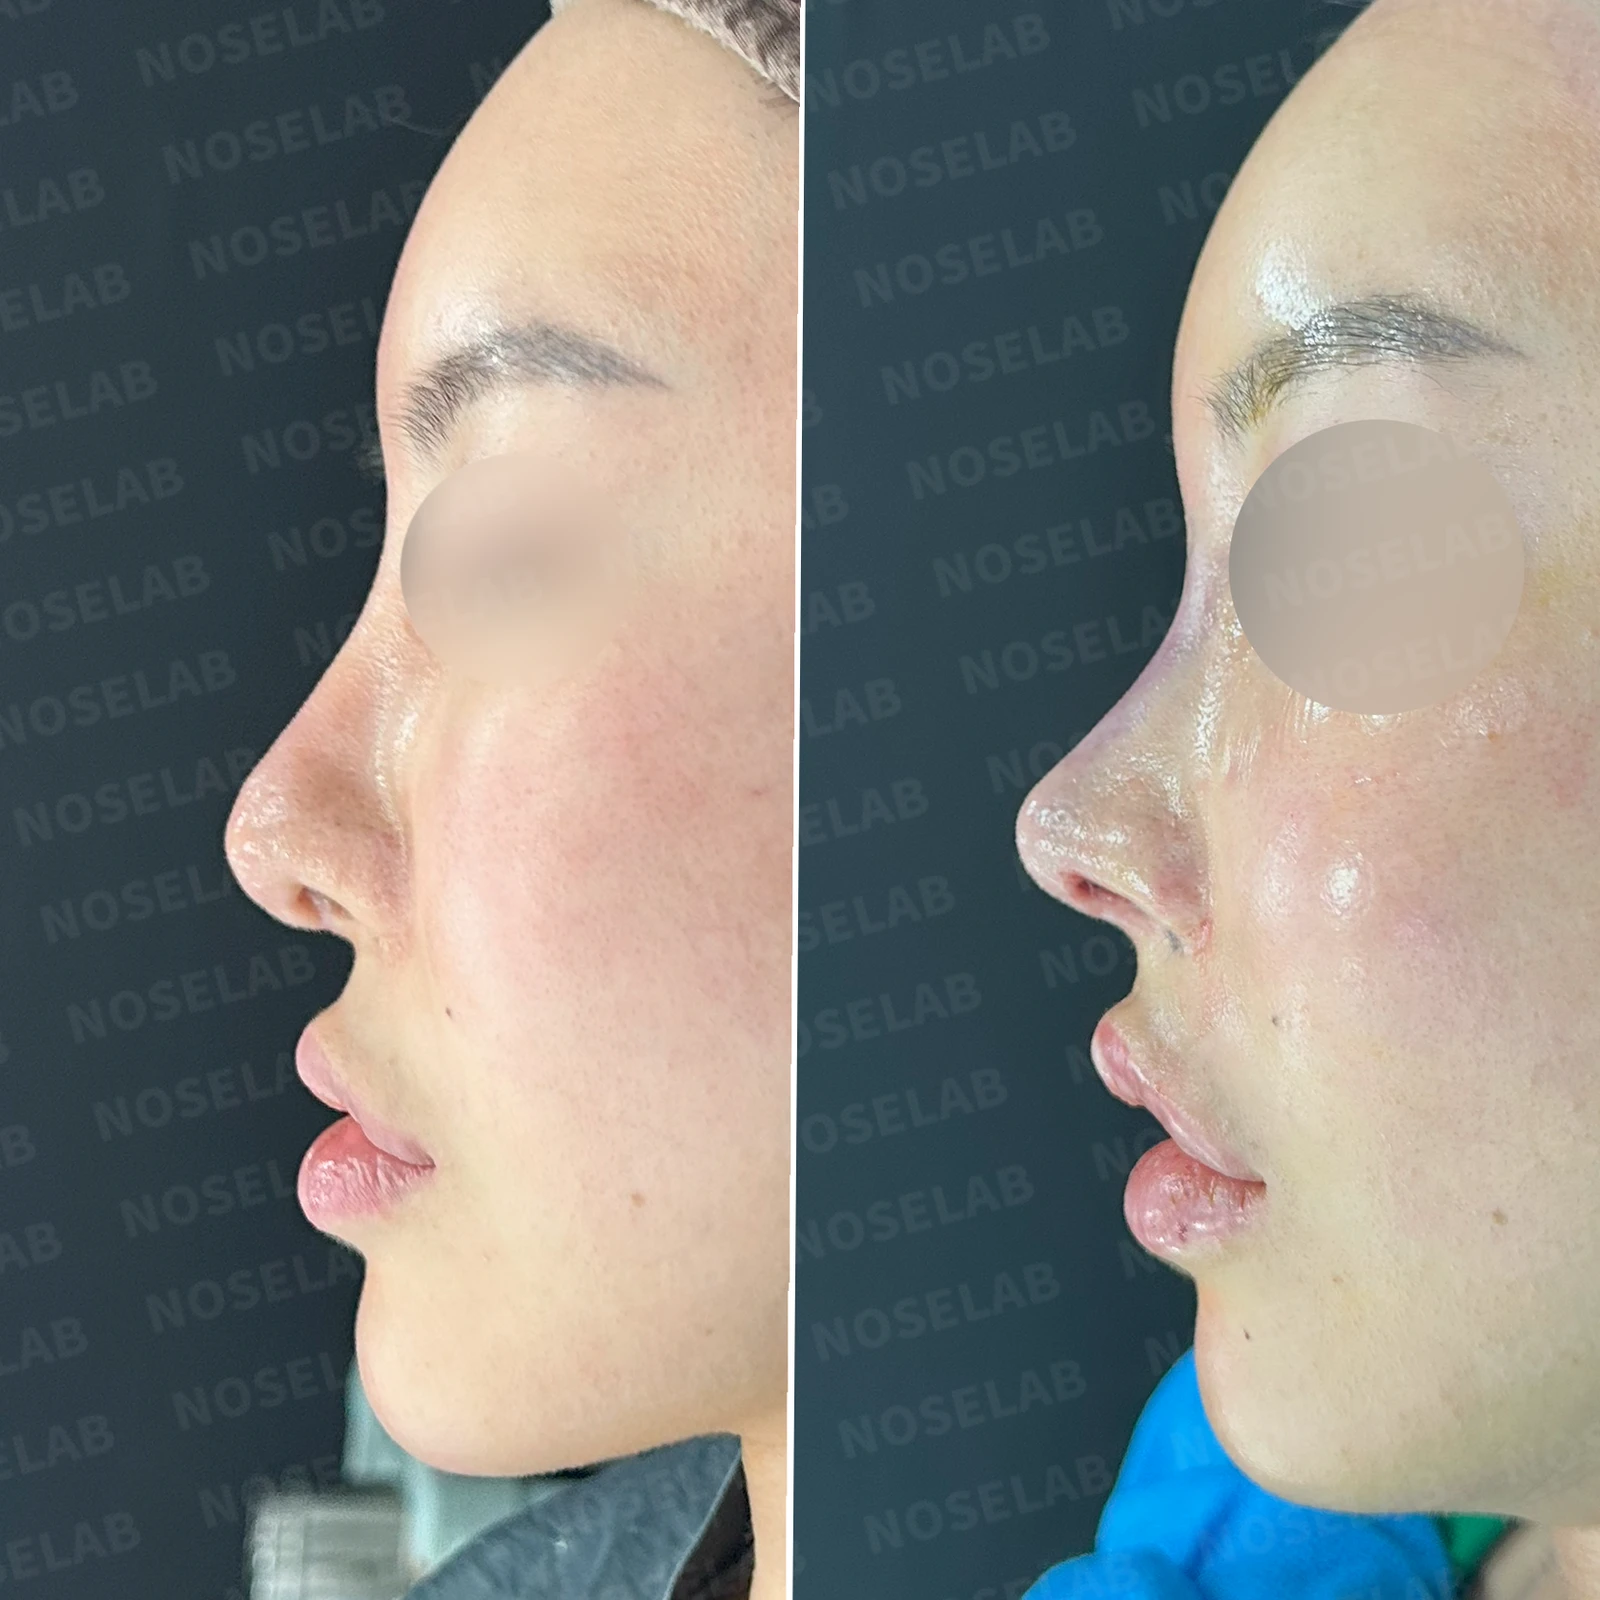
2. Profile view
Natural radix position
Adequately lowered nasal tip
Improved nasolabial angle
Correction of protruding mouth appearance by adjusting the nasolabial angle
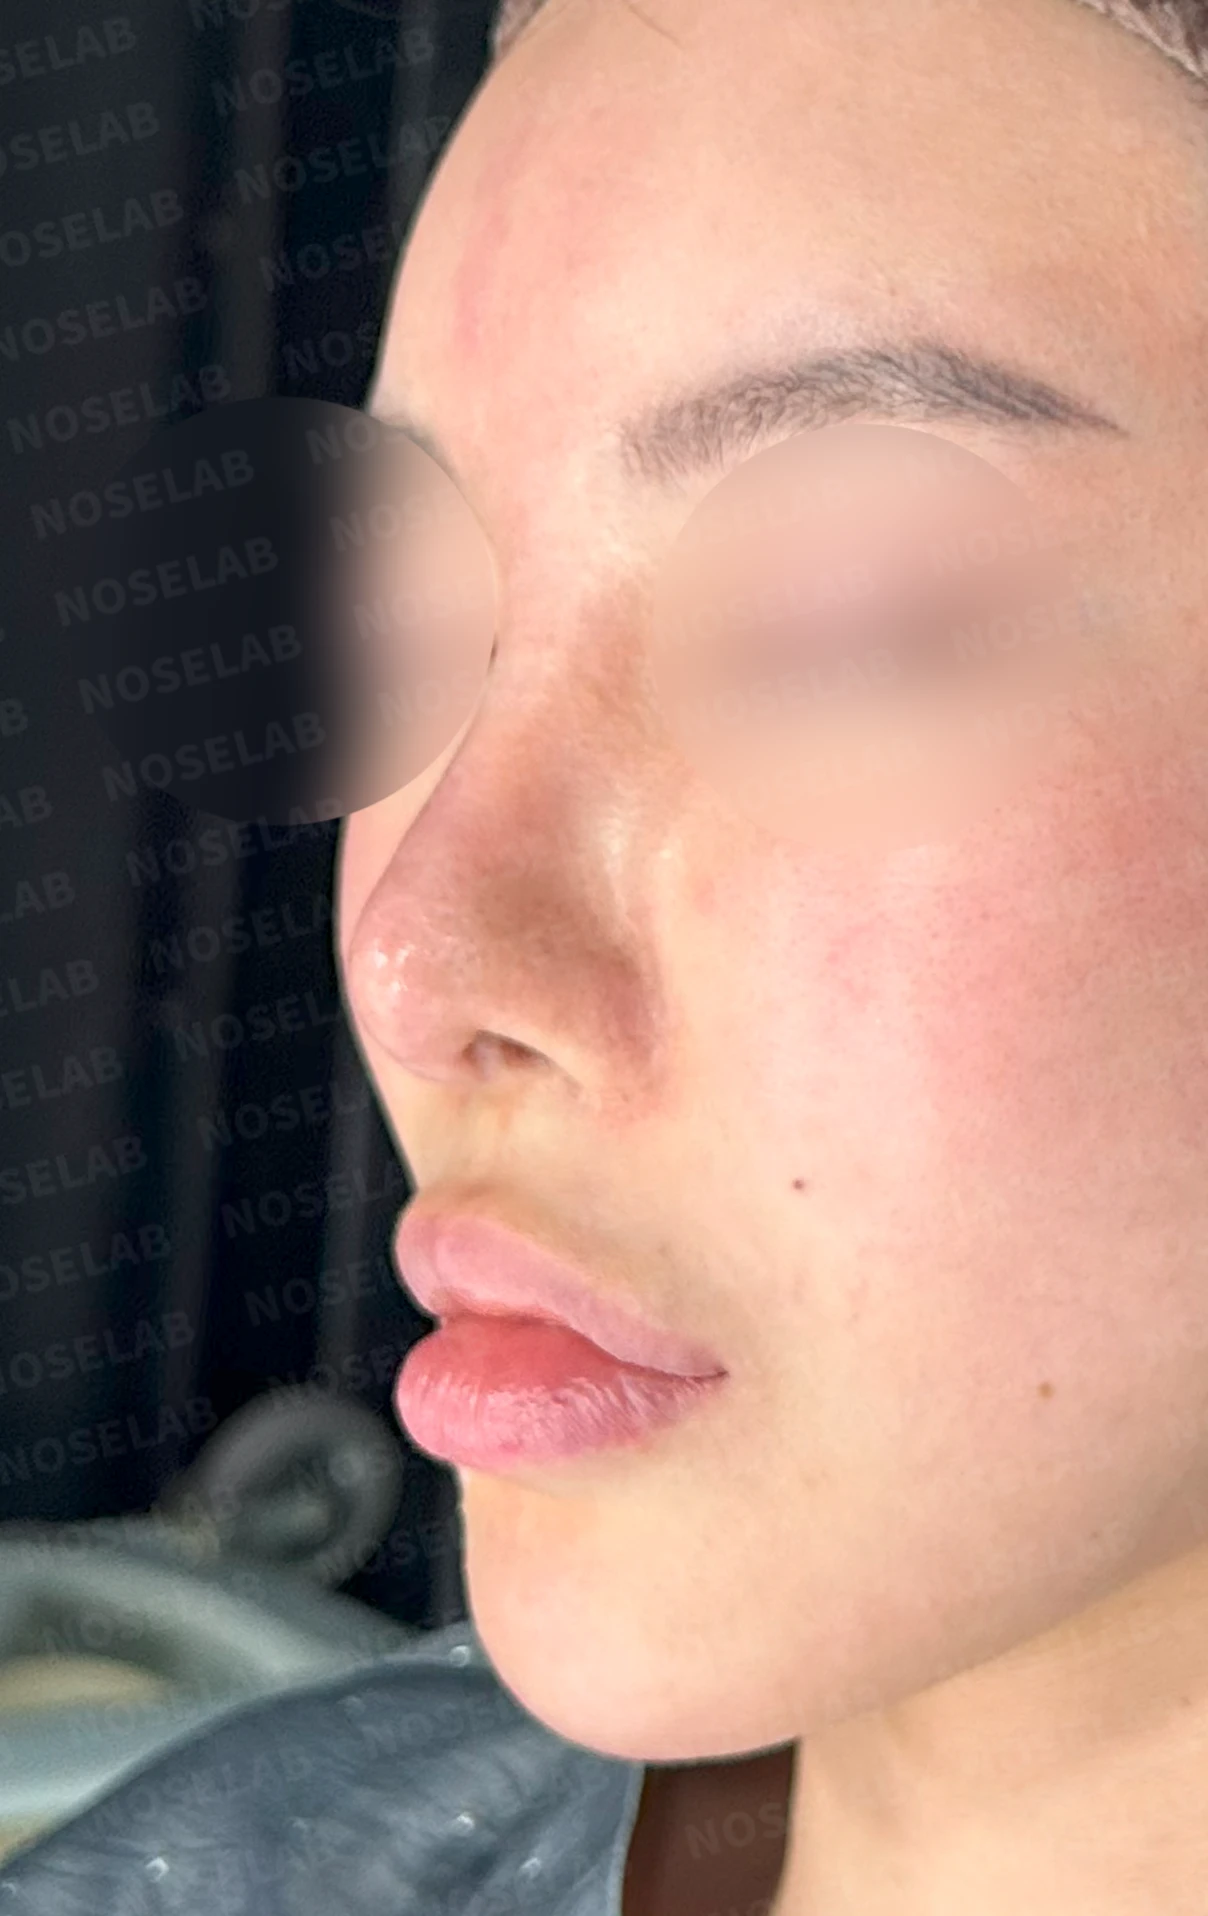
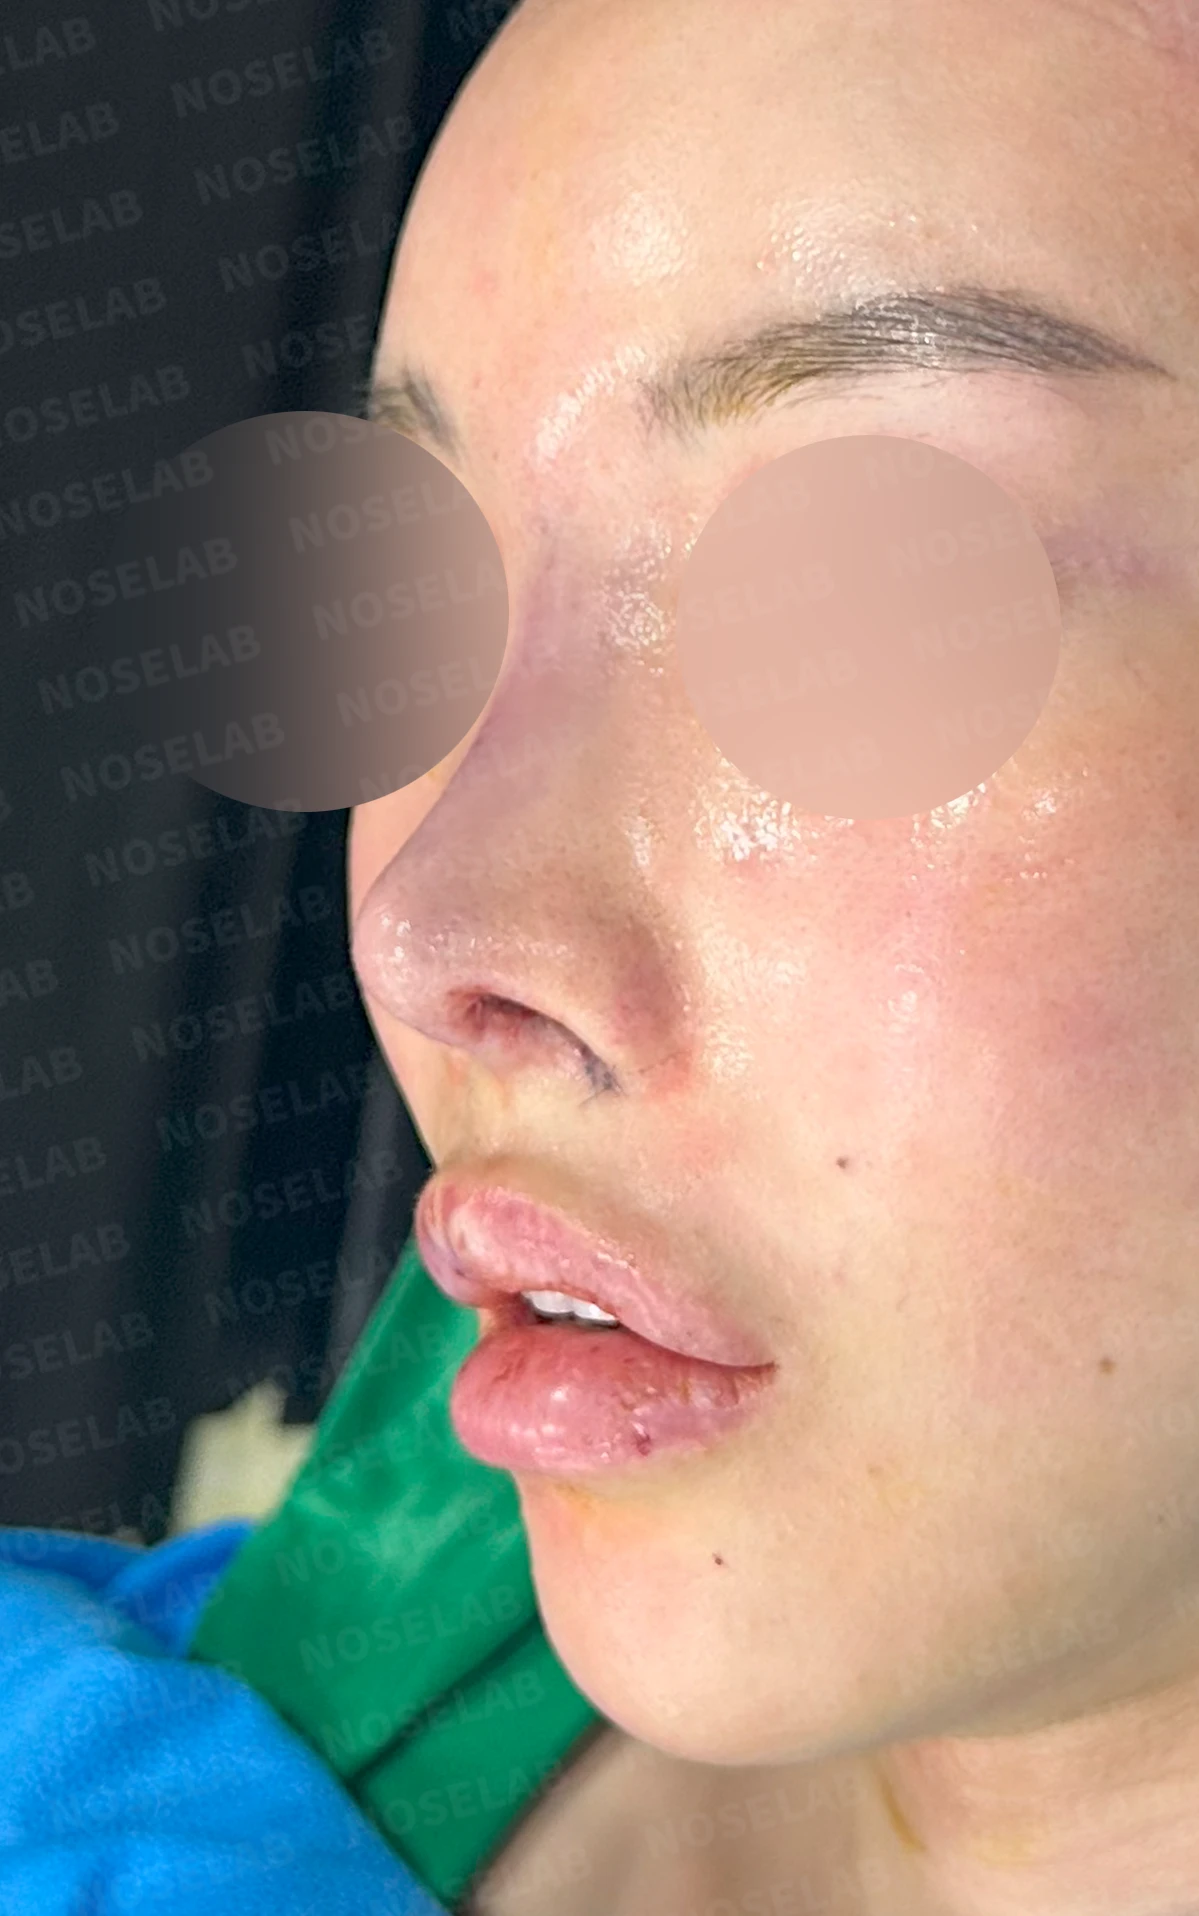
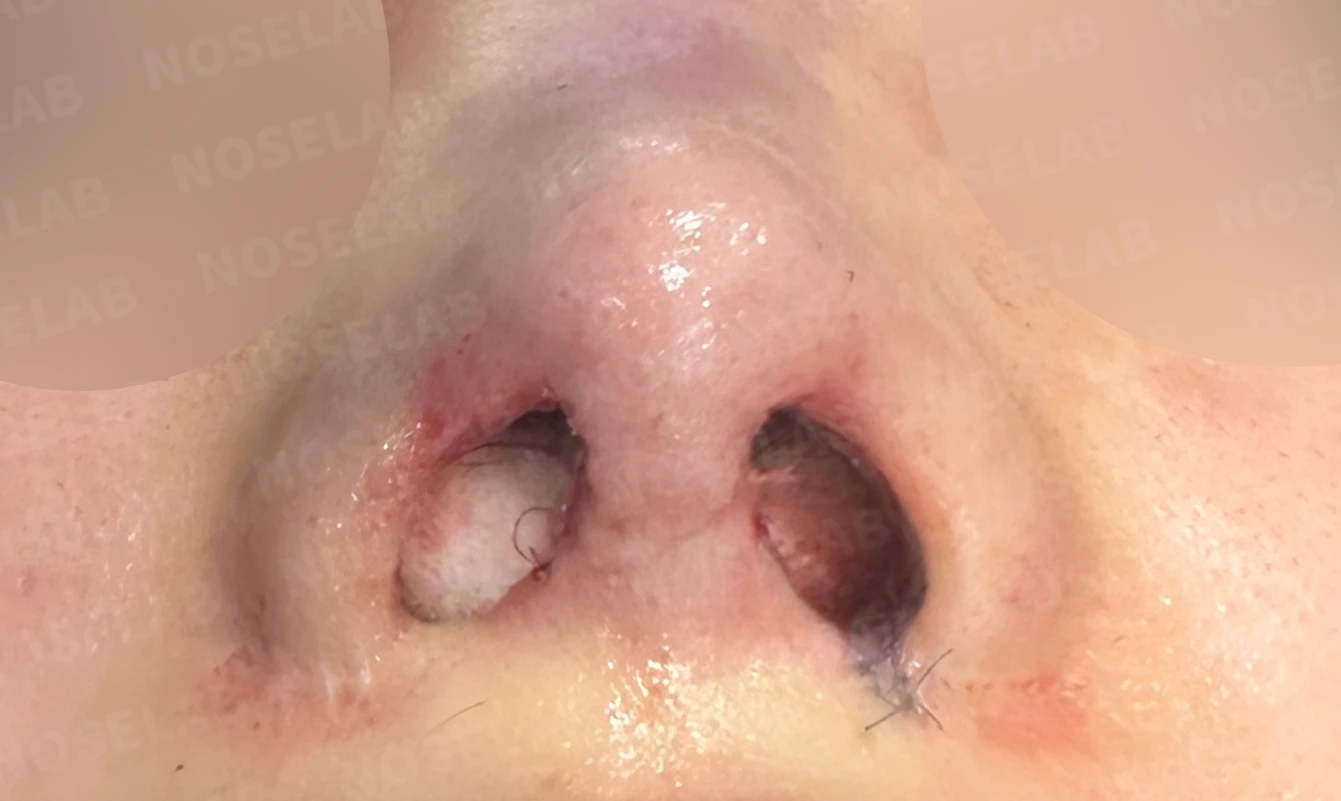
3. Nostrils
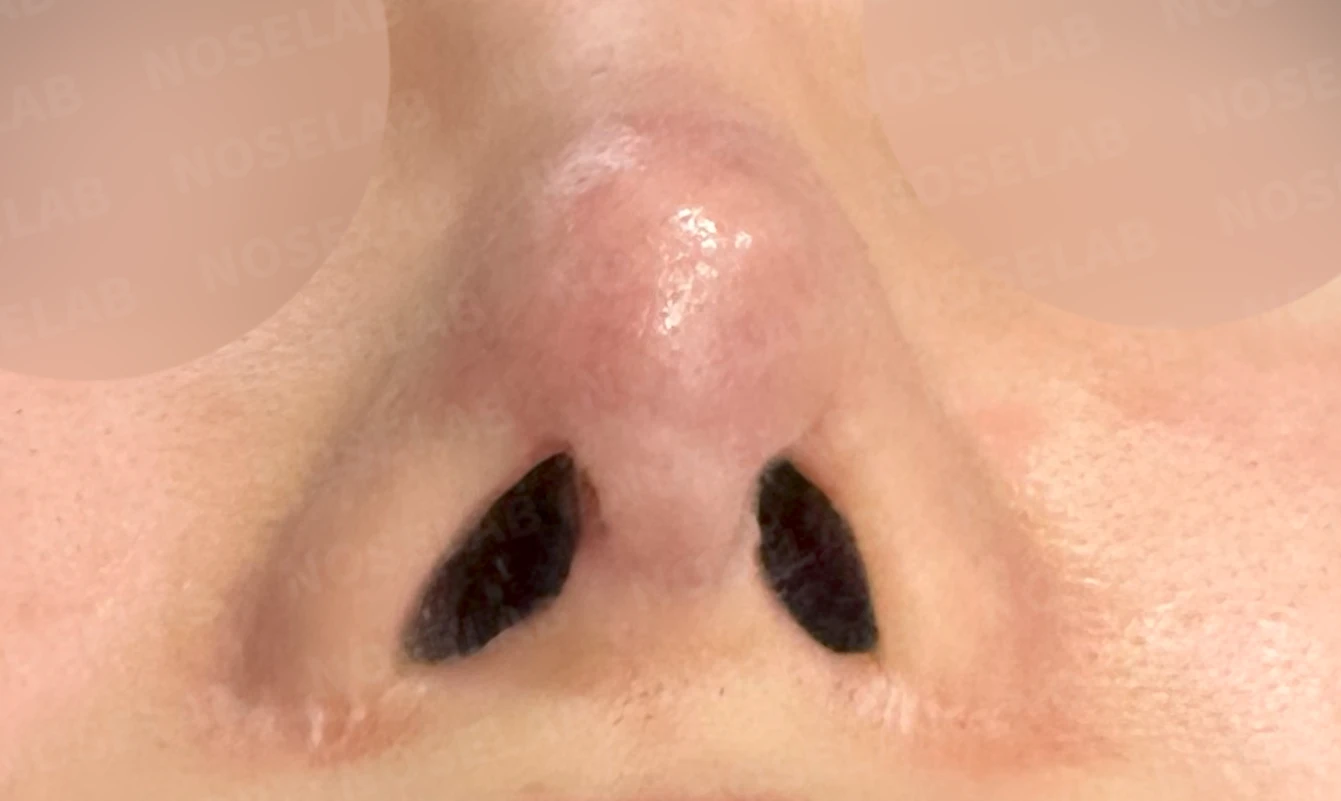
Asymmetric correction
Enlargement of left nostril size
Balanced overall structure
👨⚕️ Specialist's assessment
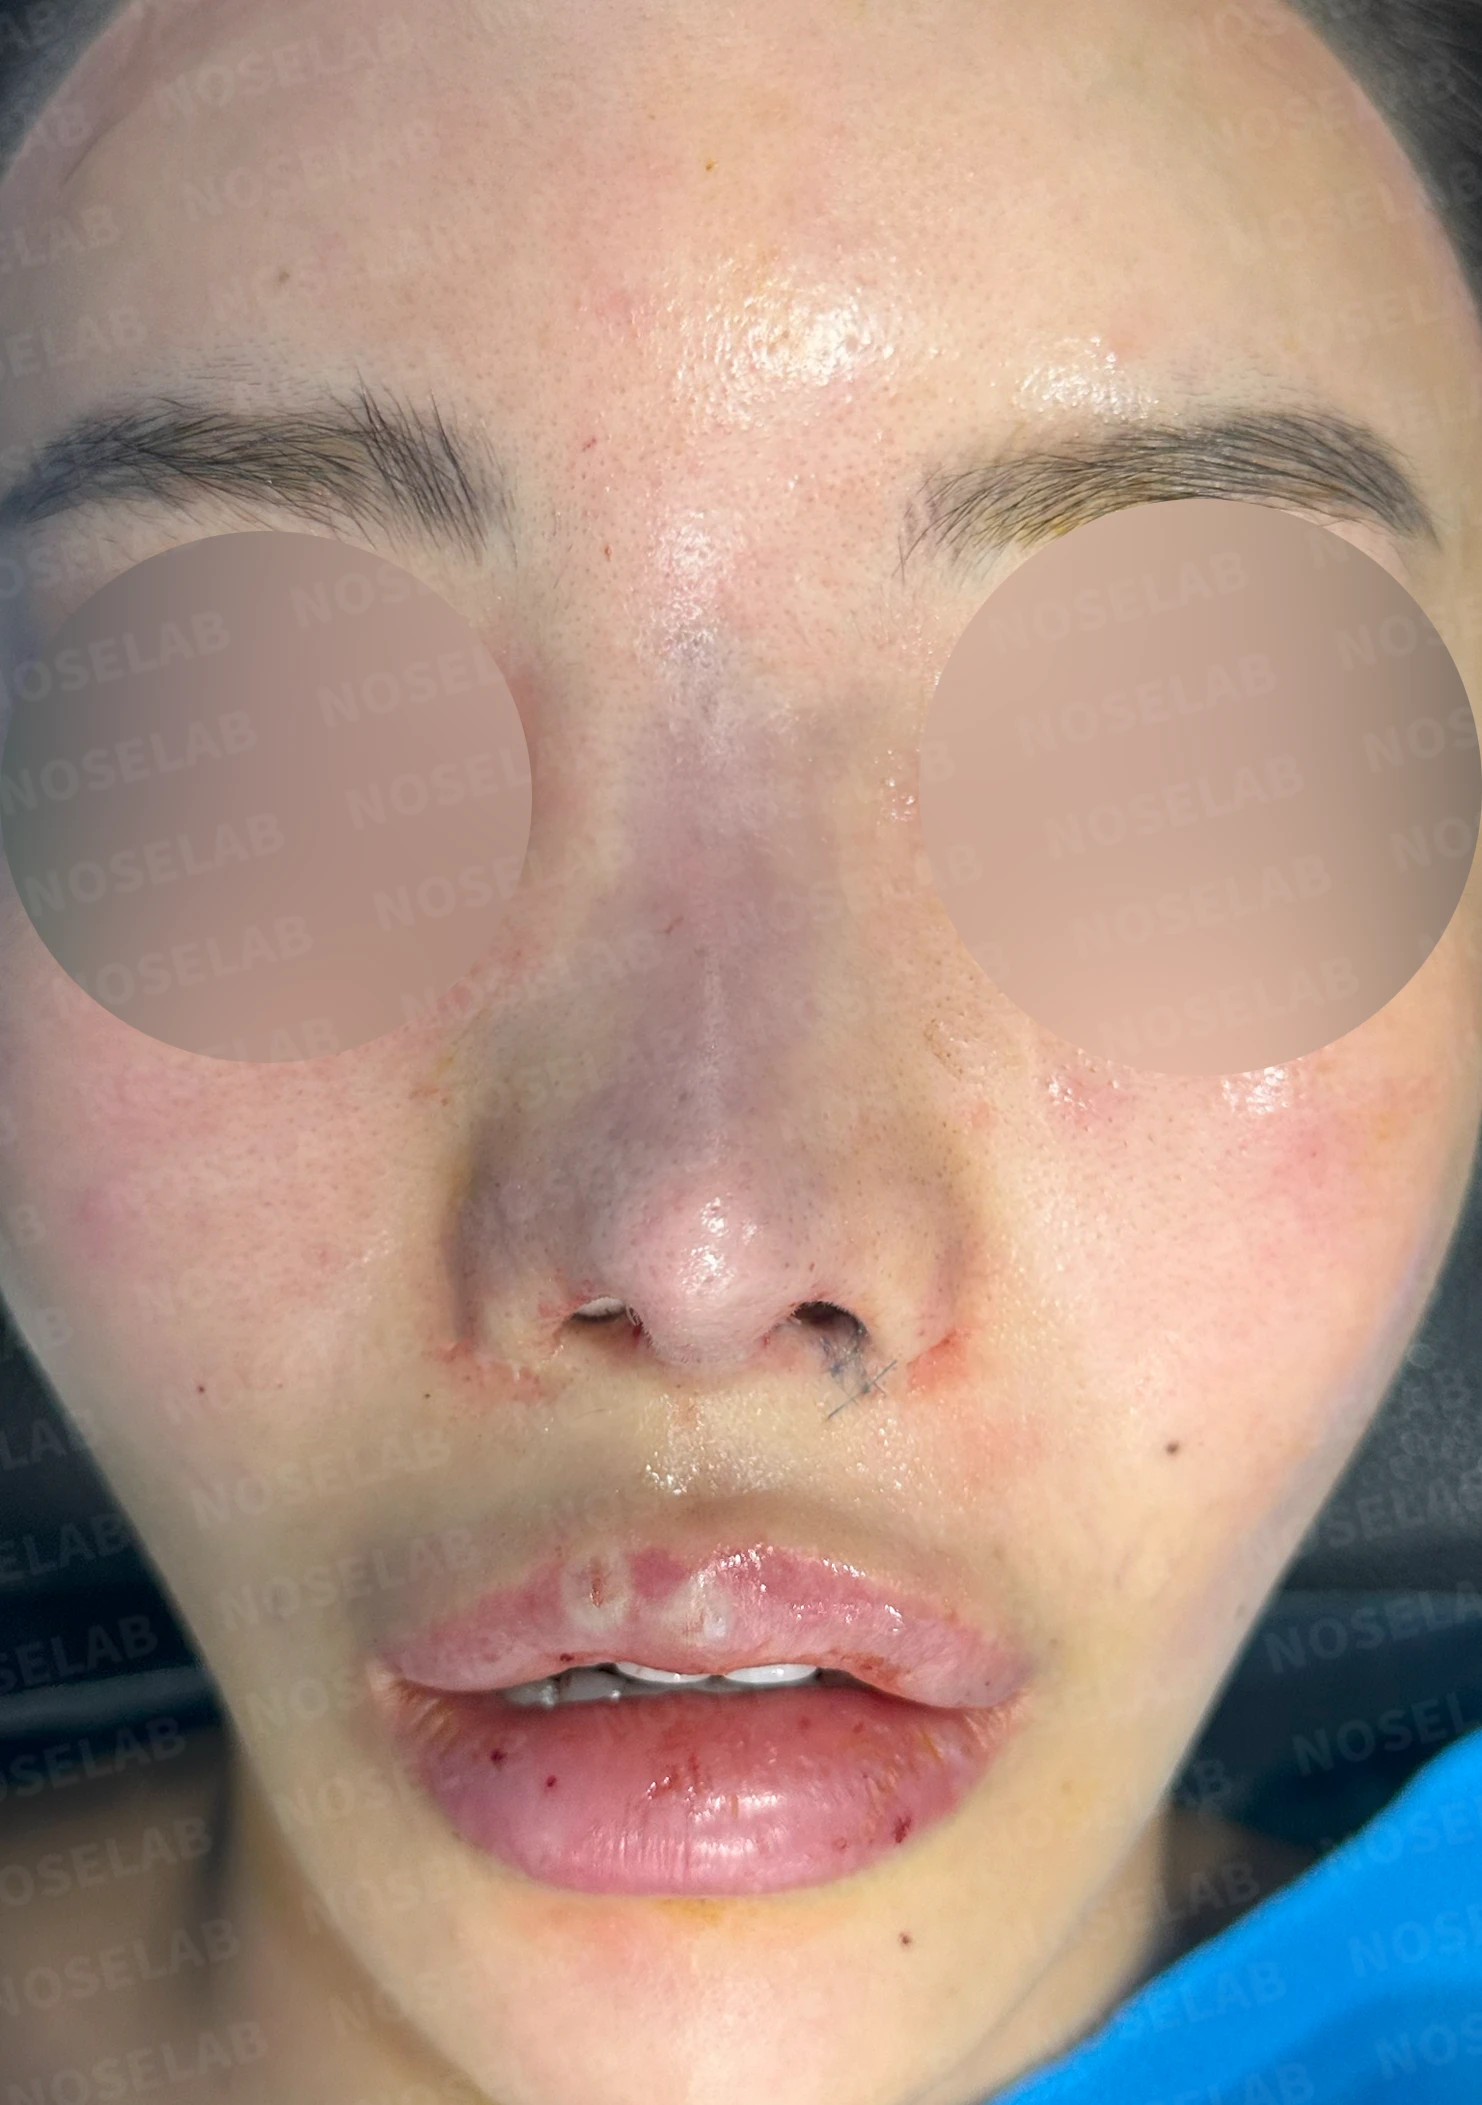
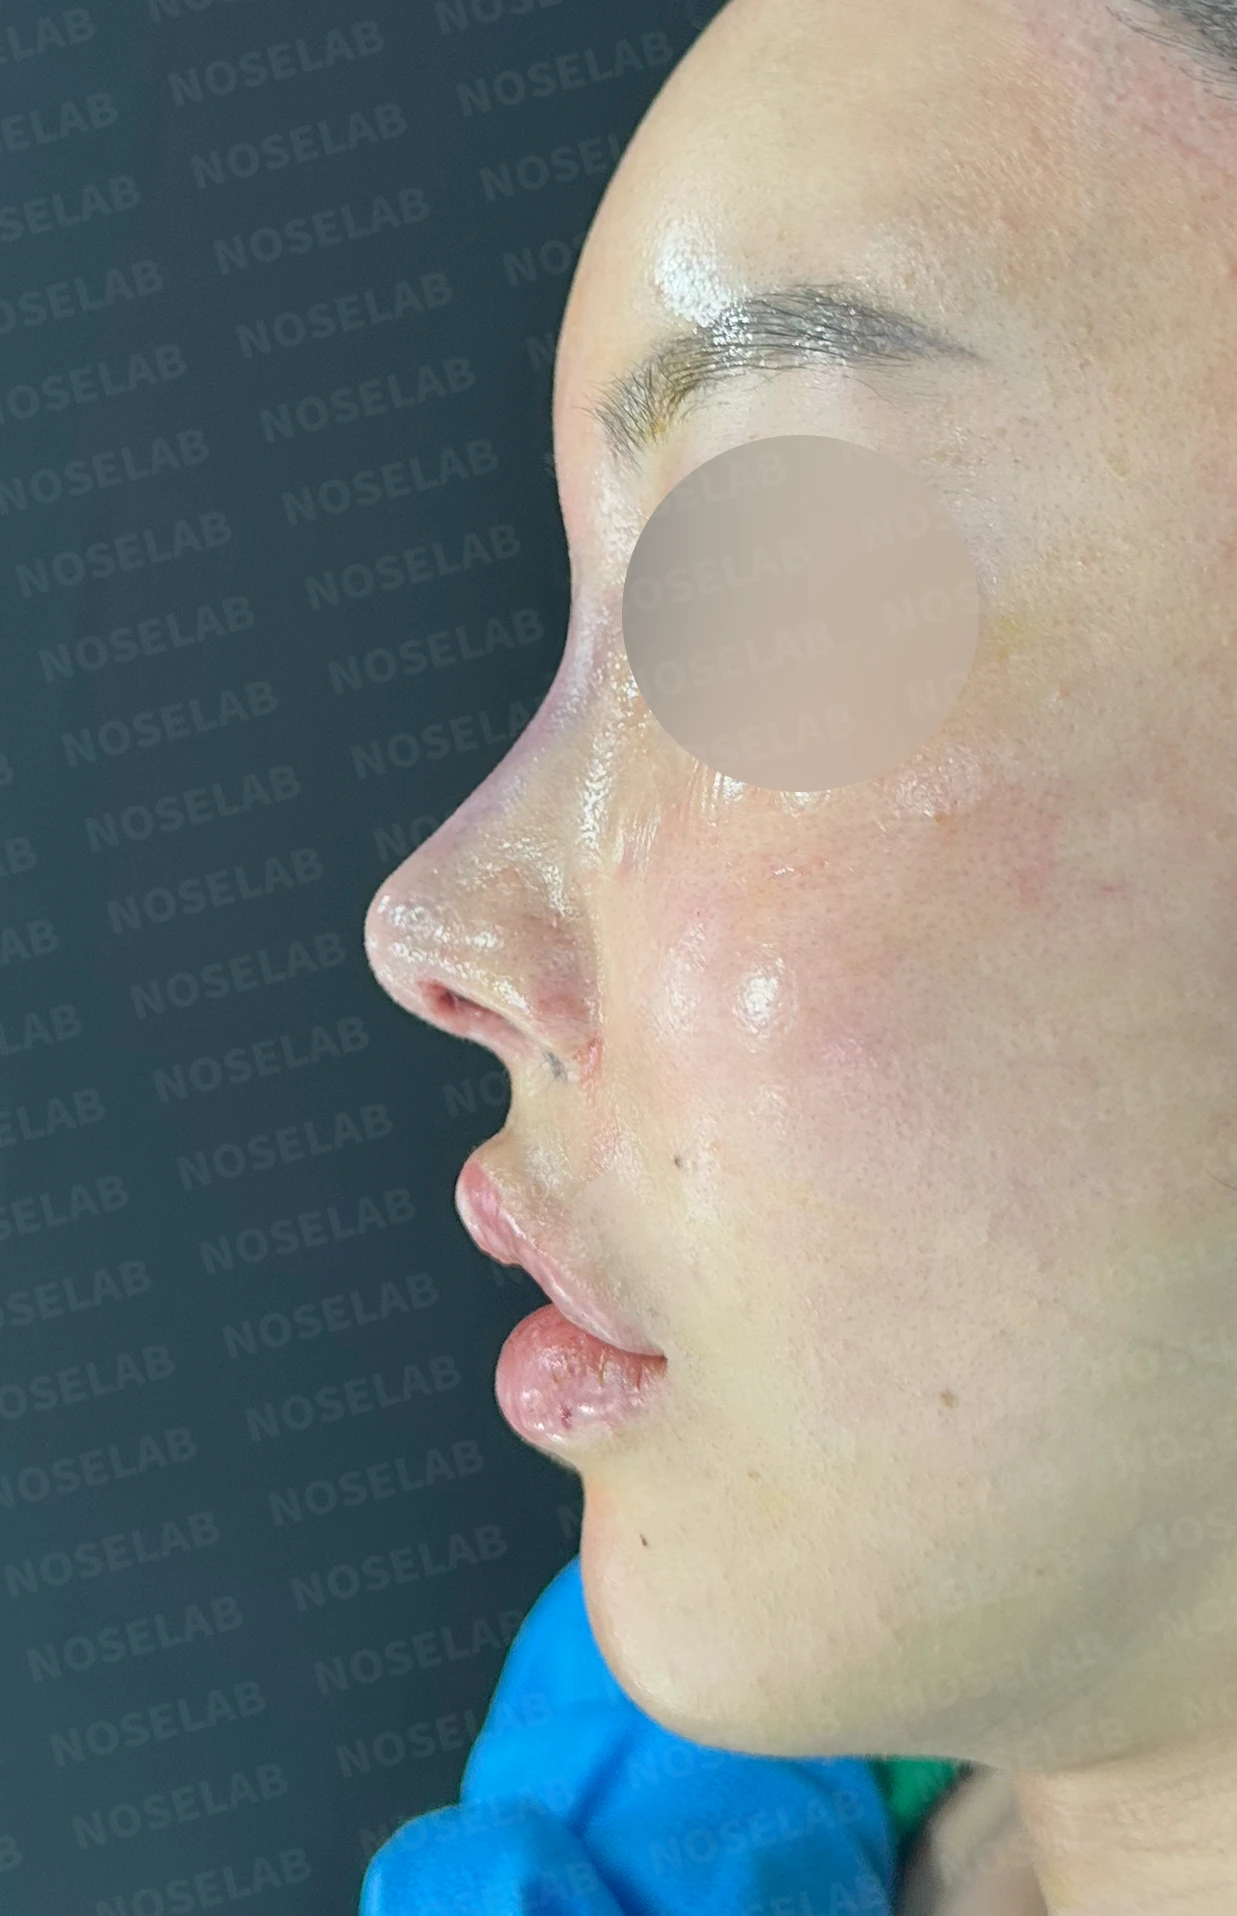
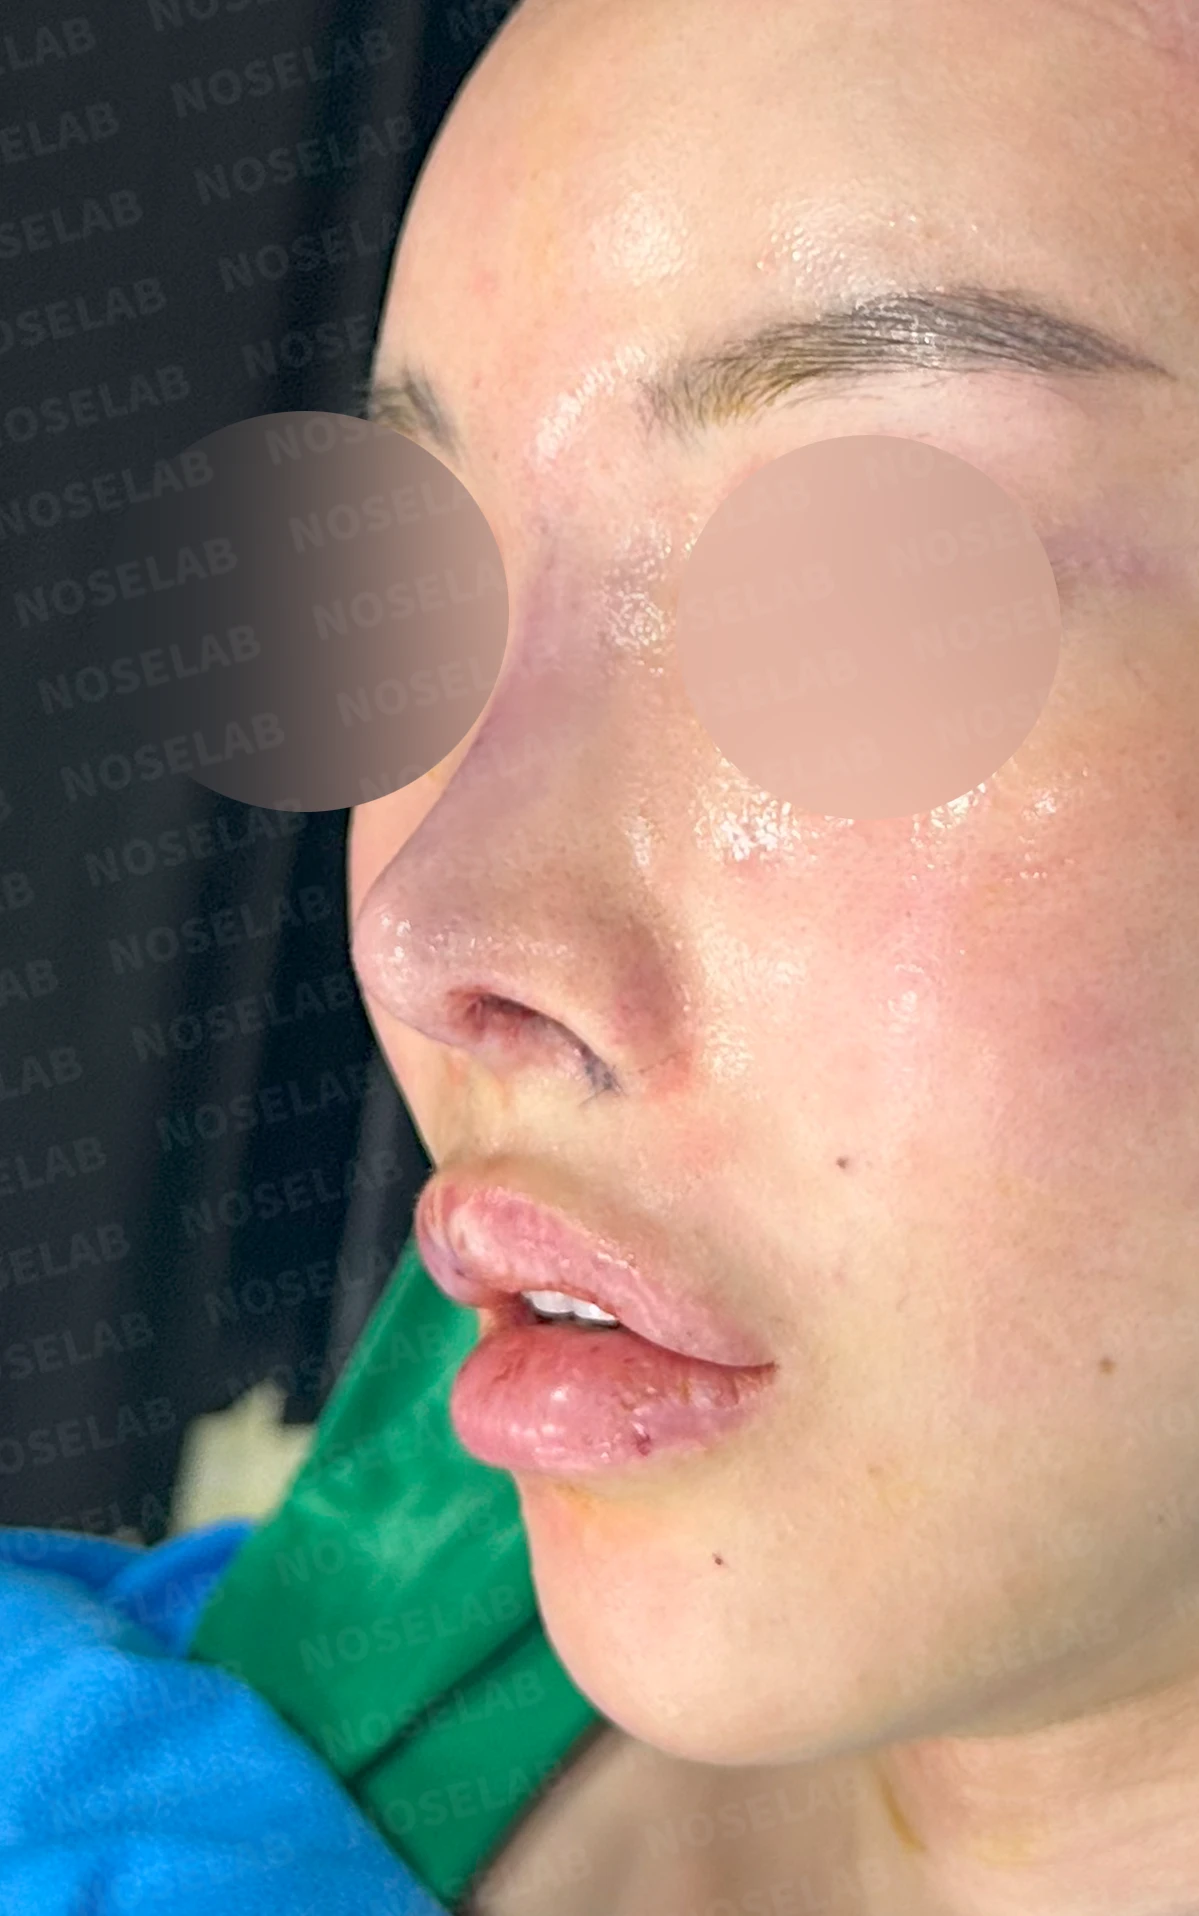
Front, profile, and oblique views taken immediately after surgery (day 0).Immediate postoperative photos show swelling and may differ from the final result.
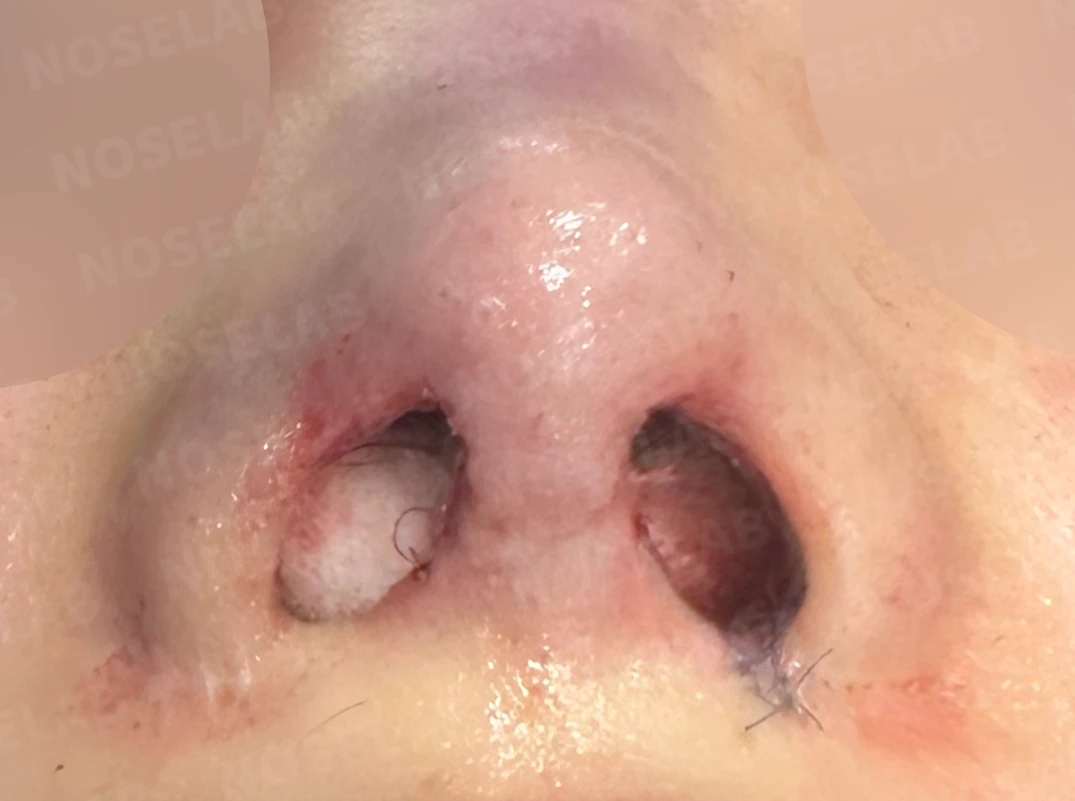
Nostril view on day 0 immediately after surgery. Photos taken immediately after surgery show swelling and may differ from the final result.
This case was complex, involving multiple prior surgeries and contracture symptoms. In particular, the left nostril, which had narrowed from previous alar reduction surgery, was improved by repositioning the ala laterally.
To fulfill the patient's primary request of 'lowering the upturned nose,' septal extension using autologous rib cartilage was performed to stably adjust the tip position while also securing adequate height. Using a silicone implant supplemented the height of the nasal bridge, achieving overall facial harmony.
Considering the patient's history of contracture symptoms, the surgery was performed with a focus on minimizing tissue tension, and detailed post-operative care instructions were provided to help maintain long-term stability.
This was Dr. Peter C. Kang. Thank you.
Thank you.
#closedrhinoplasty #revisionrhinoplasty #contracturecorrection #crookednosecorrection #customrhinoplasty

Limitations and risks
When autologous rib cartilage is used, scarring and pain may remain at the donor site on the chest, and pneumothorax (pleural injury) can occur rarely. Over time, the grafted cartilage may warp or undergo partial resorption.
When revising after implant removal, contracture may progress again after removal, the nasal height and length may decrease, and staged surgery may be necessary depending on the skin condition.
When foreign materials such as injected fillers are removed and reconstructed, contracture may recur, nasal height and length may decrease, and staged surgery may be necessary depending on the skin condition.
When the septum is corrected at the same time, nasal obstruction may persist or recur, and in rare cases, septal perforation or changes in smell may occur.
Common potential risks include infection, bleeding, asymmetry, scarring, skin necrosis, and insufficient improvement; results vary depending on individual skin condition and previous surgical history.