Hello, this is Dr. Peter C. Kang, medical director.
Today, I would like to introduce a revision rhinoplasty case of a patient presenting with excessive nostril show and a dorsal hump that had persisted for 17 years.
📍 Surgical history
17 years ago: Dorsal hump shaving surgery
10 years ago: Nasal filler injection (removed on the day of surgery)
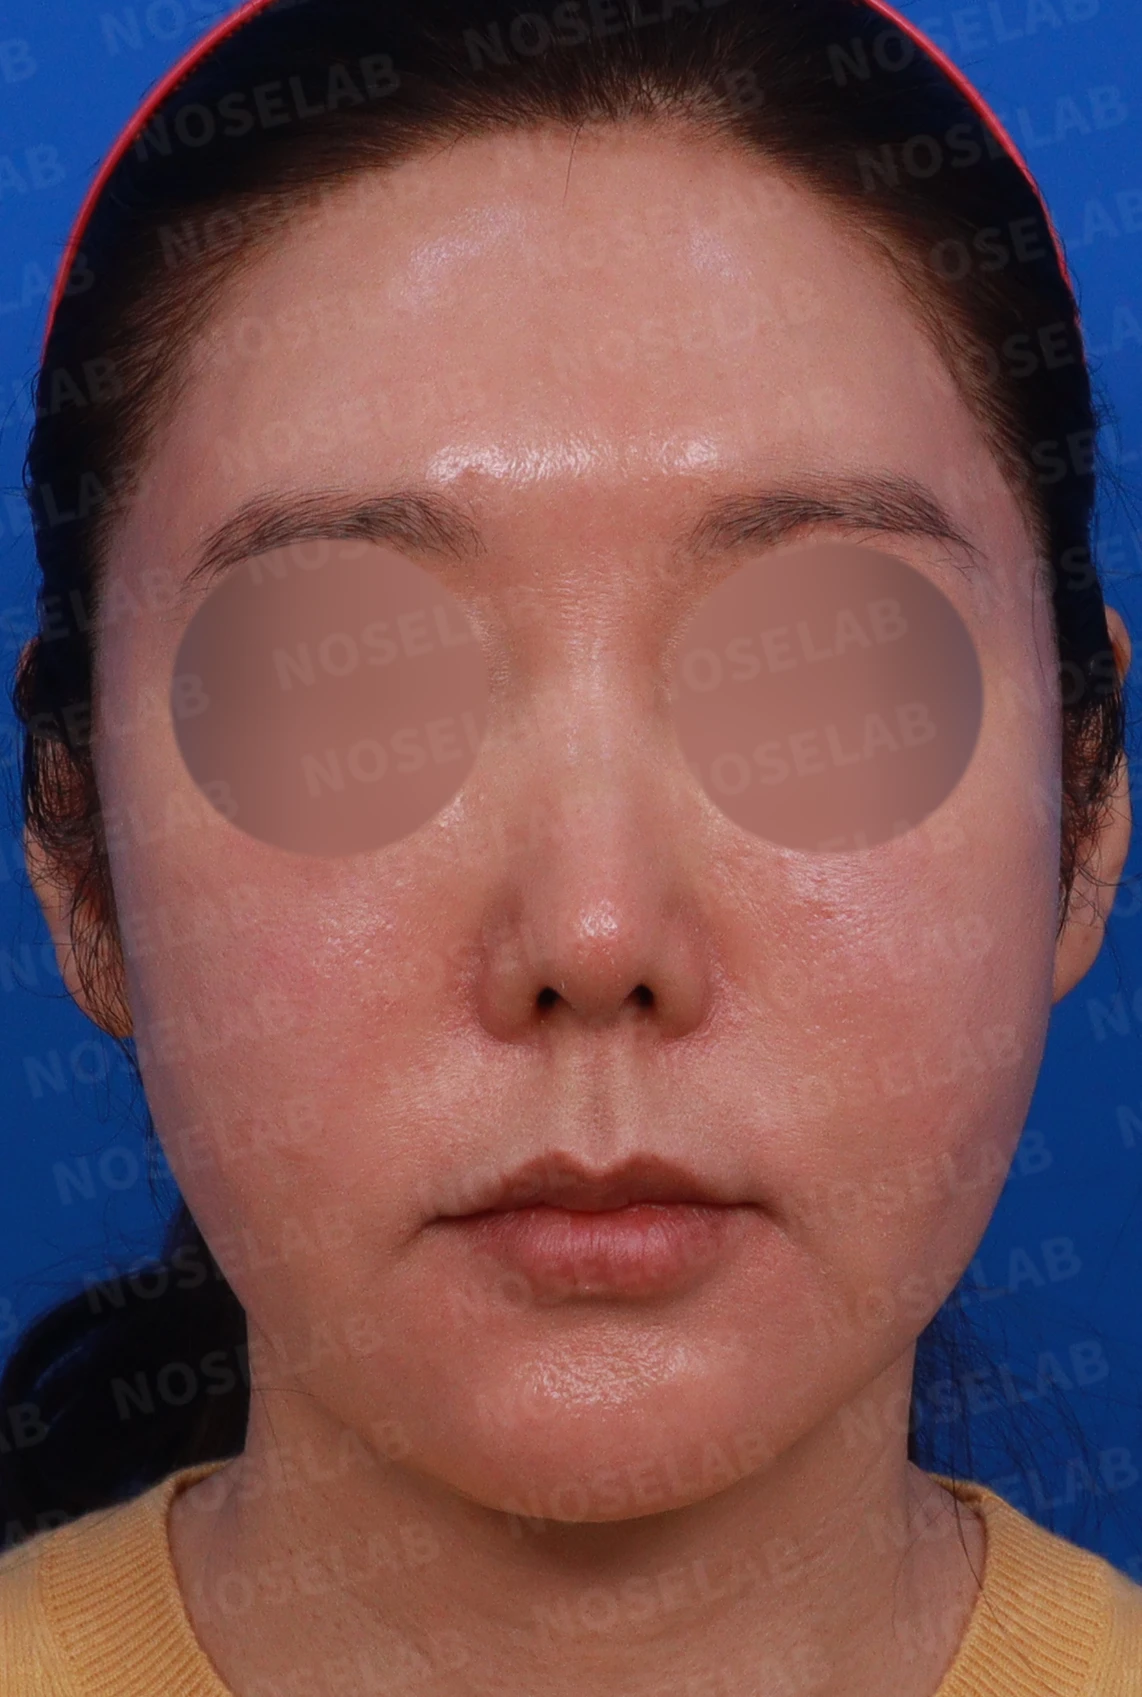
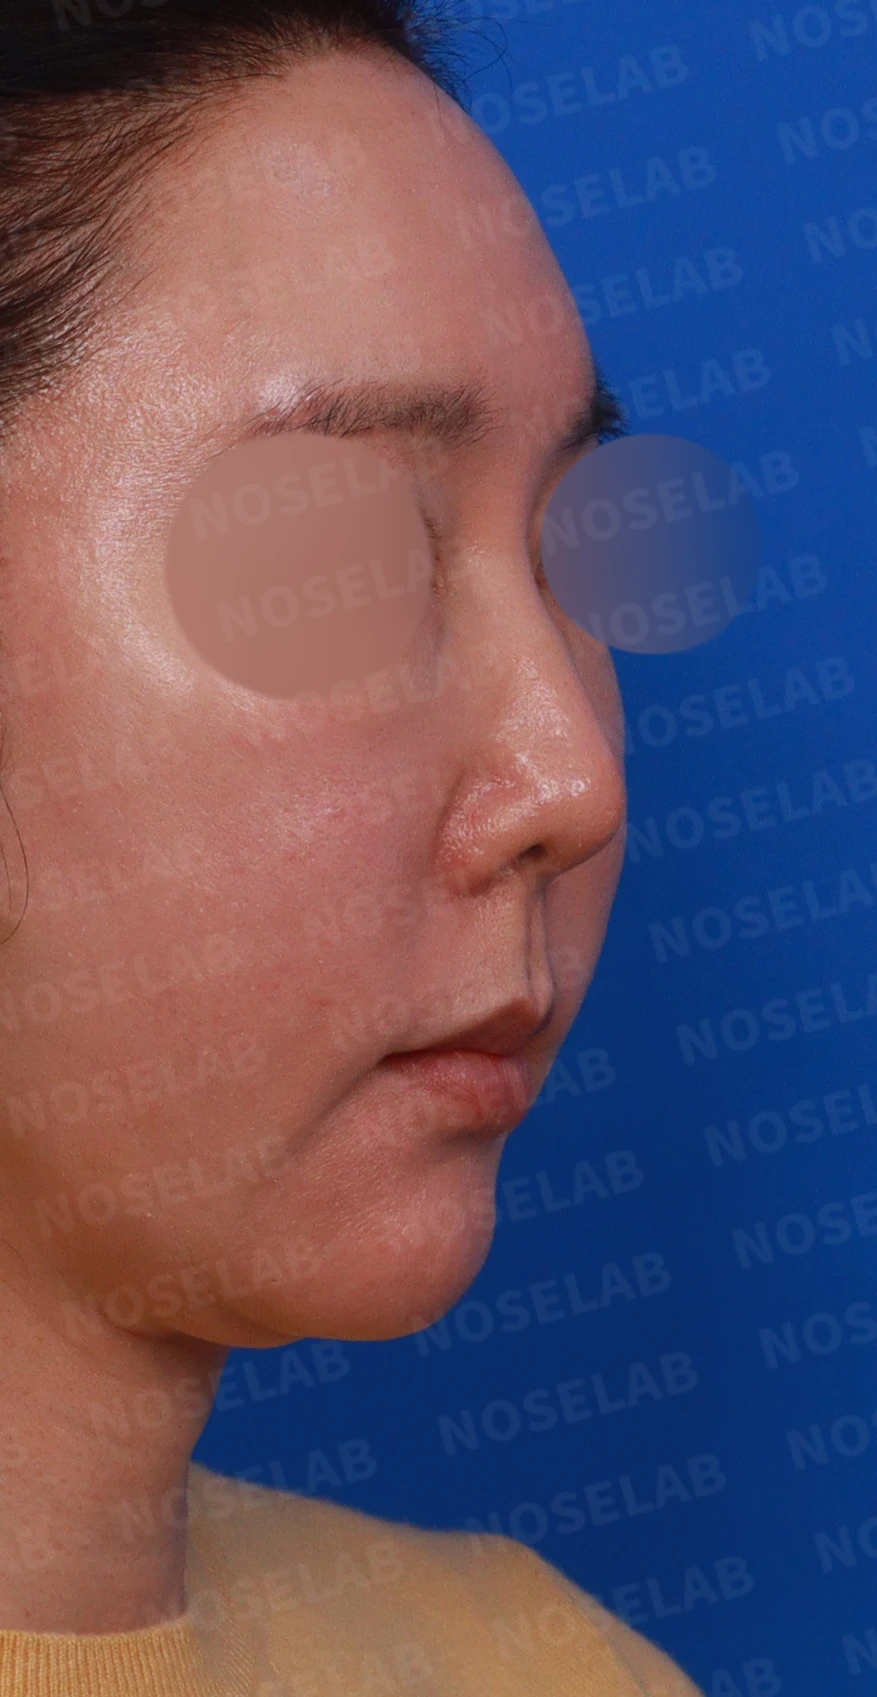
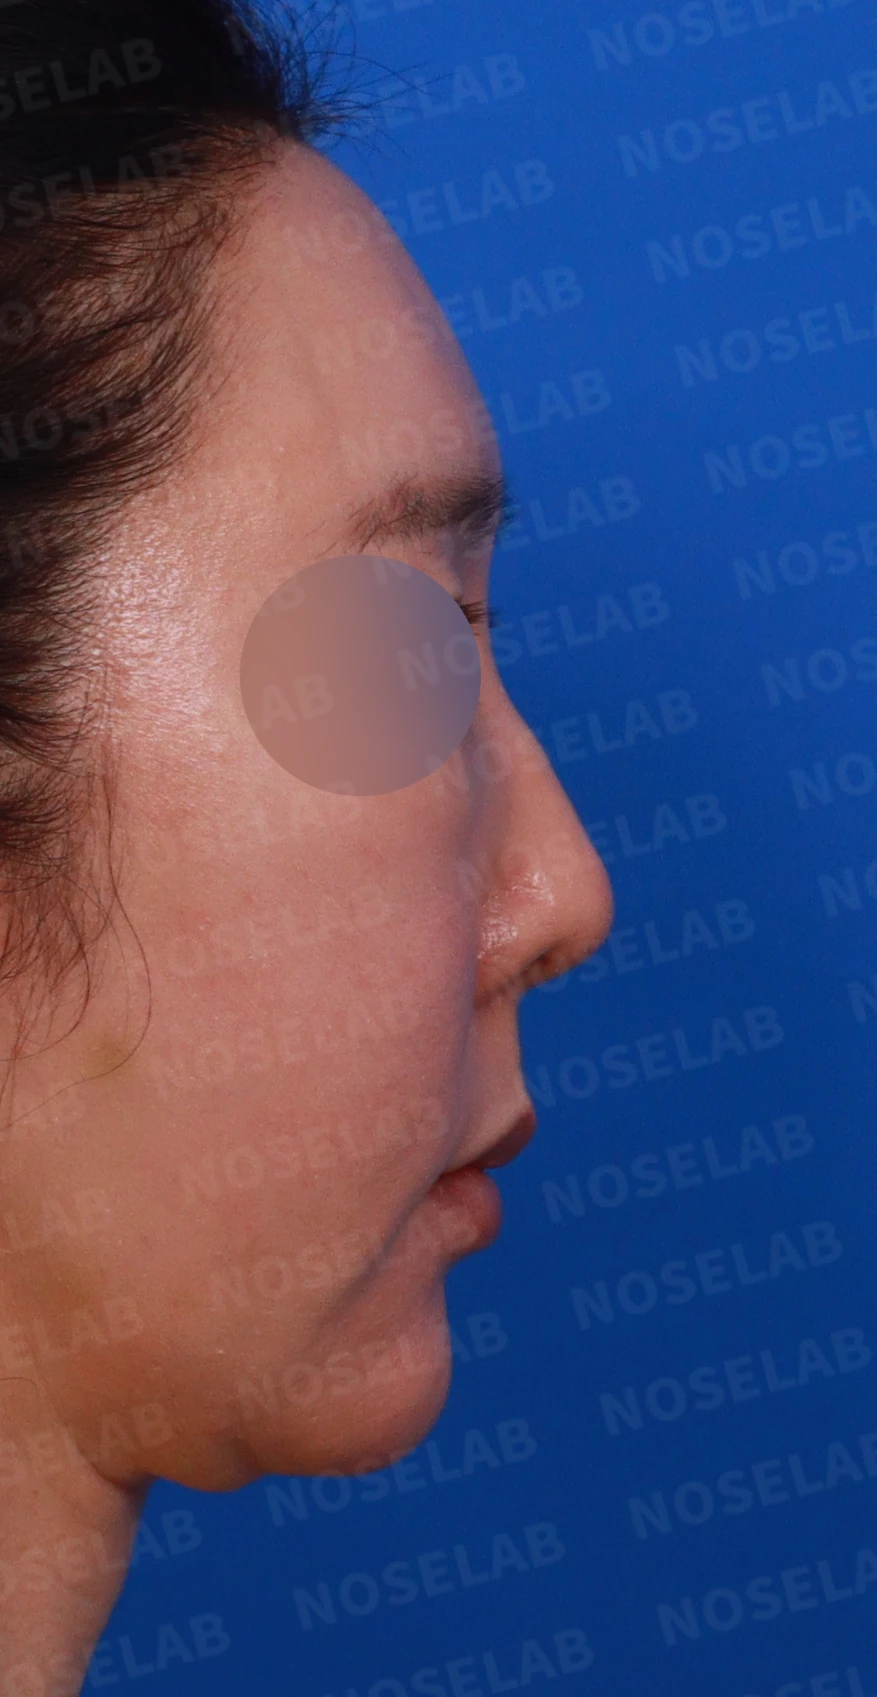
Design consultation front, left oblique, and profile views
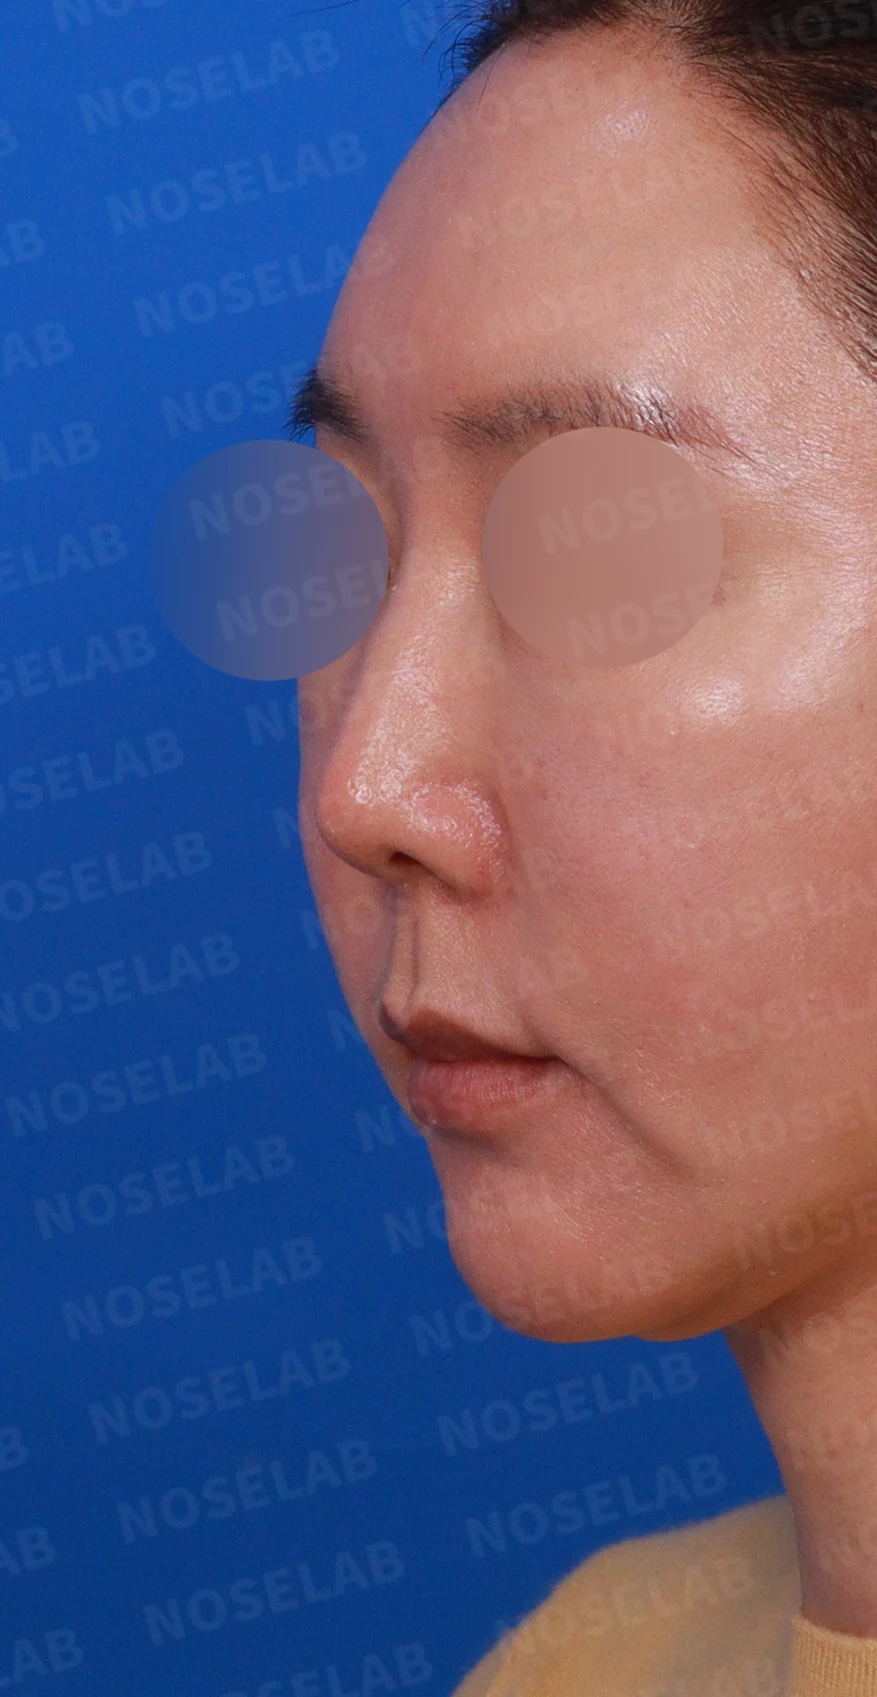
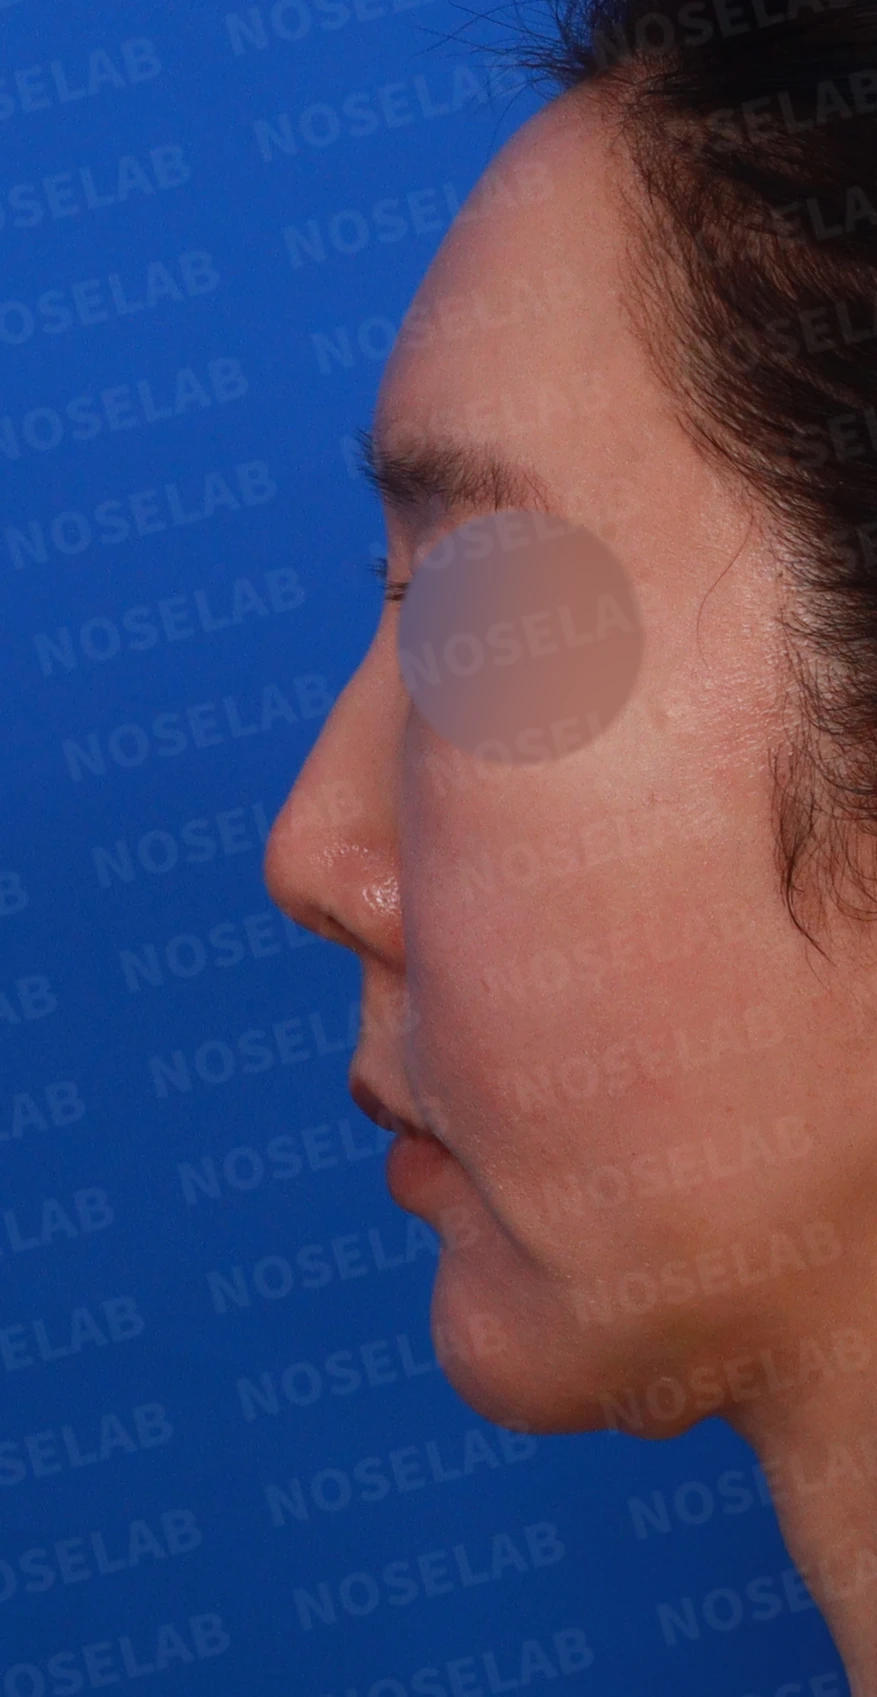
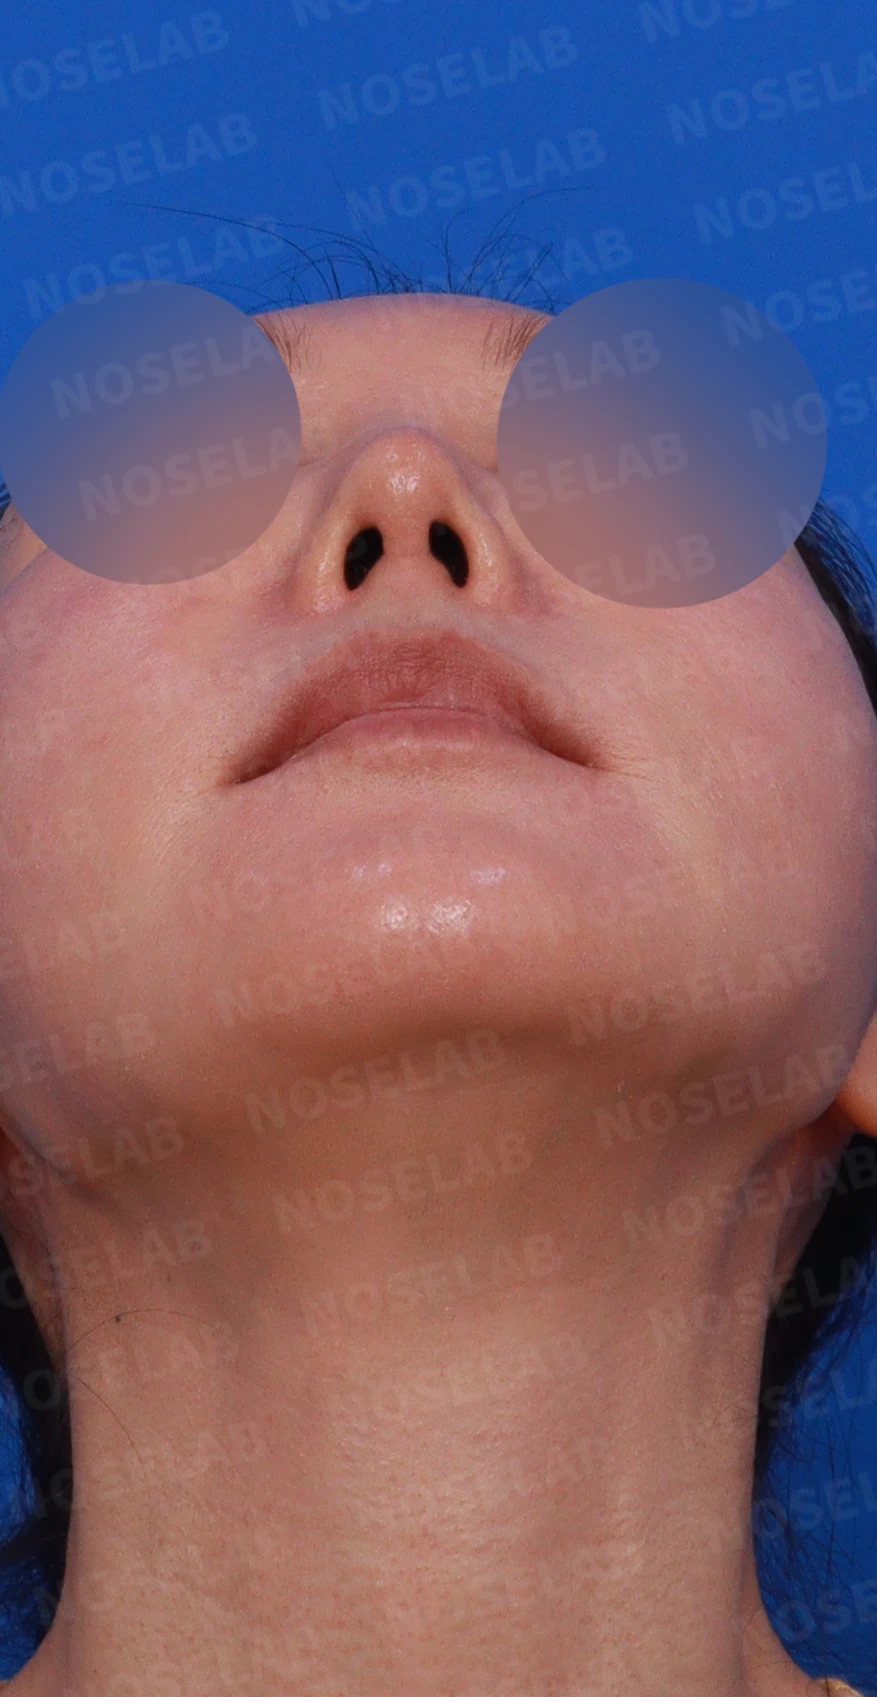
Design consultation: right oblique, profile, and basal (nostril) views
🔎 Initial consultation findings
Front view
Flared nasal shape
Flat nasal bridge
Deviated nose
Excessive nostril show
Profile view
Drooping tip
Residual dorsal hump
Wide nasolabial angle
Elongated-looking philtrum
Nostrils
Nostril asymmetry
Columella tilted to the right
✨ Patient's requests
Improvement of excessive nostril show
Naturally elevating the nose
Result harmonious with the face
💉 Surgical procedure details
Structural improvement
Septal extension using autologous cartilage
Complete removal of existing filler
Correction of the nasolabial angle
Improvement in shape
Repositioning the nasal tip to reduce excessive nostril show
Correcting the nasolabial angle to improve the appearance of an elongated philtrum and an upturned look
Creating a harmonious nasal bridge height
Performing lateral osteotomies to correct the crooked nose
Smoothing down the residual dorsal hump
✅ Surgical results
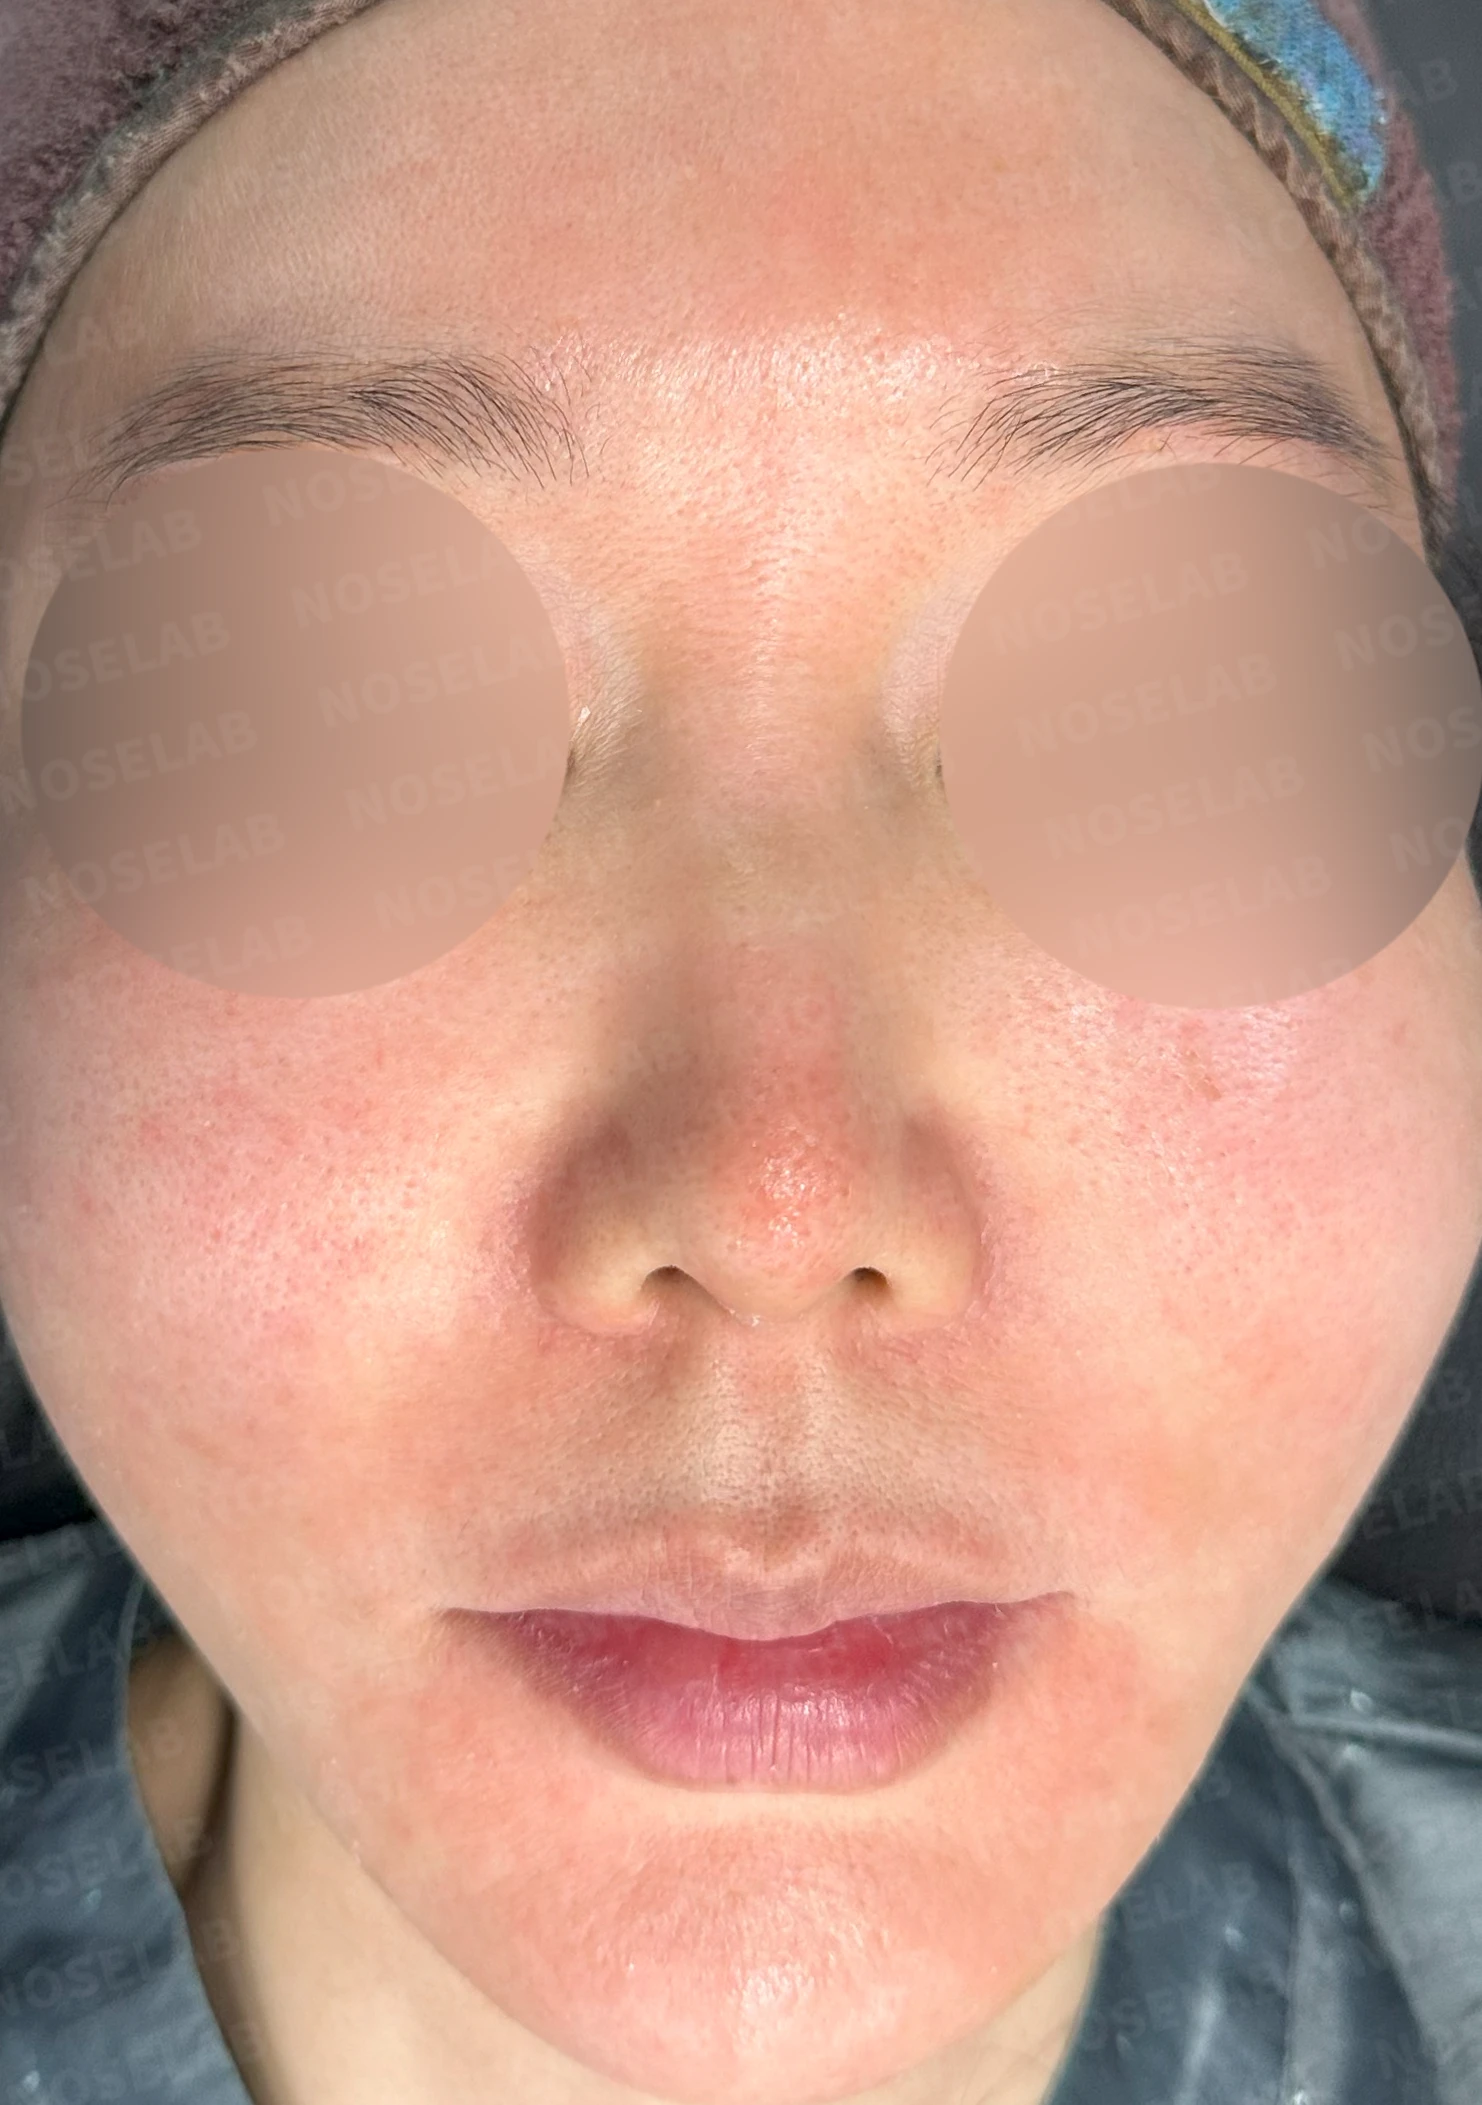
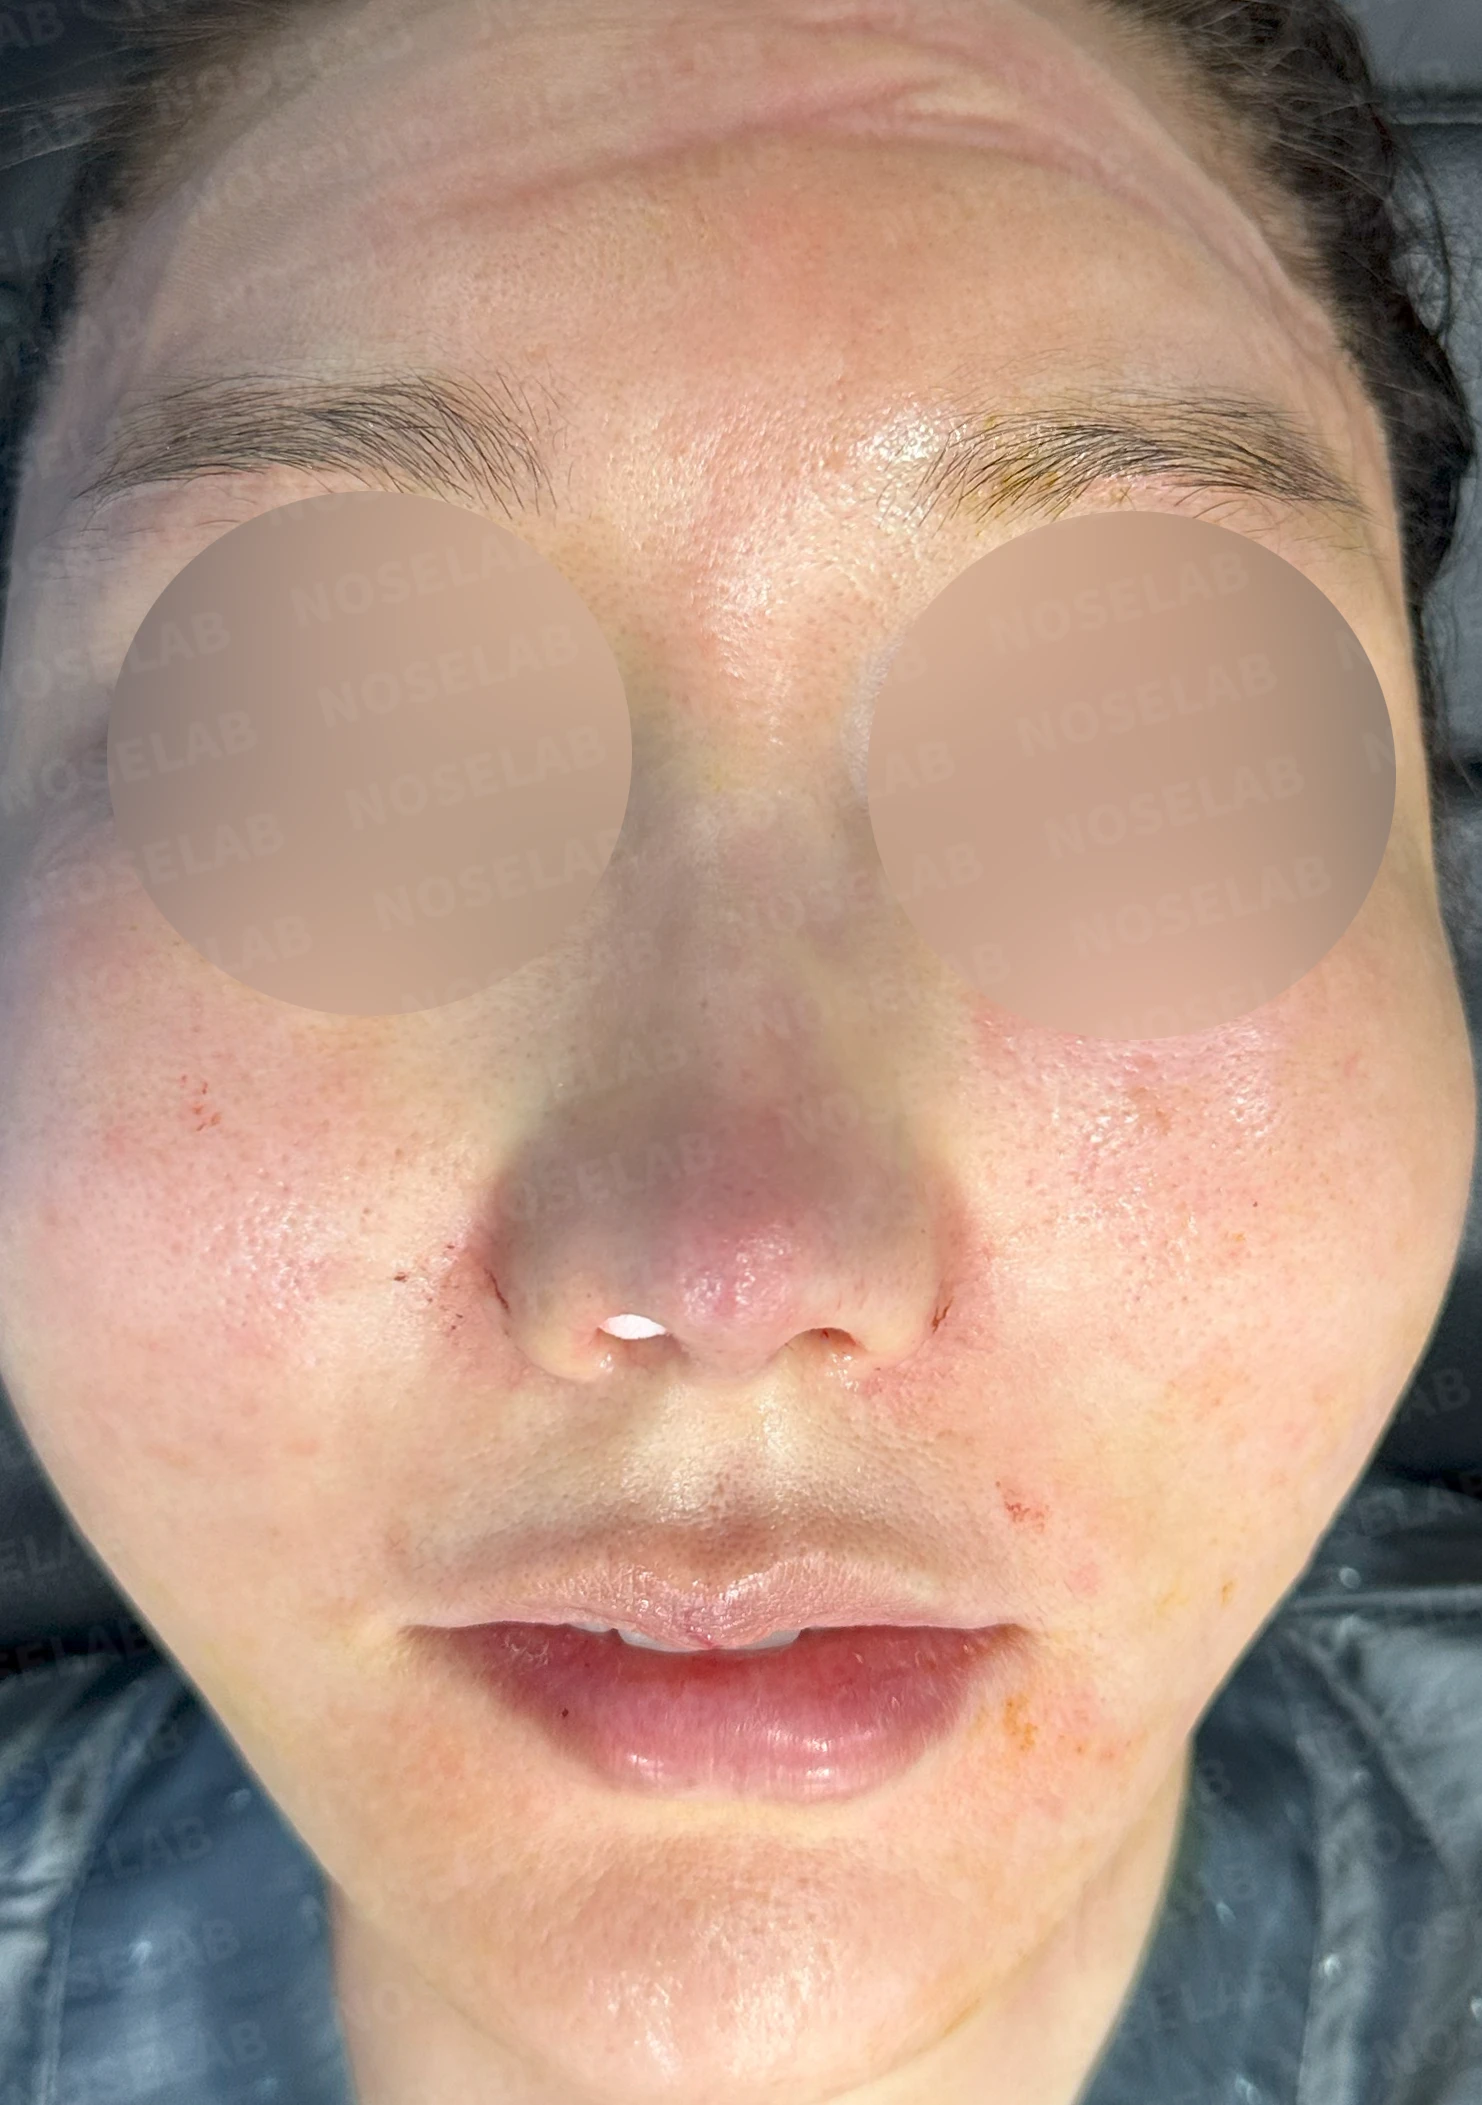
Before surgery / Day 0 immediately after surgery Photos taken immediately after surgery show swelling and may differ from the final result.
Front view
The crooked nose is corrected and straightened
Excessive nostril show is naturally improved
The previously flat and spread-out nasal contour has transformed into a well-balanced shape
Overall natural impression
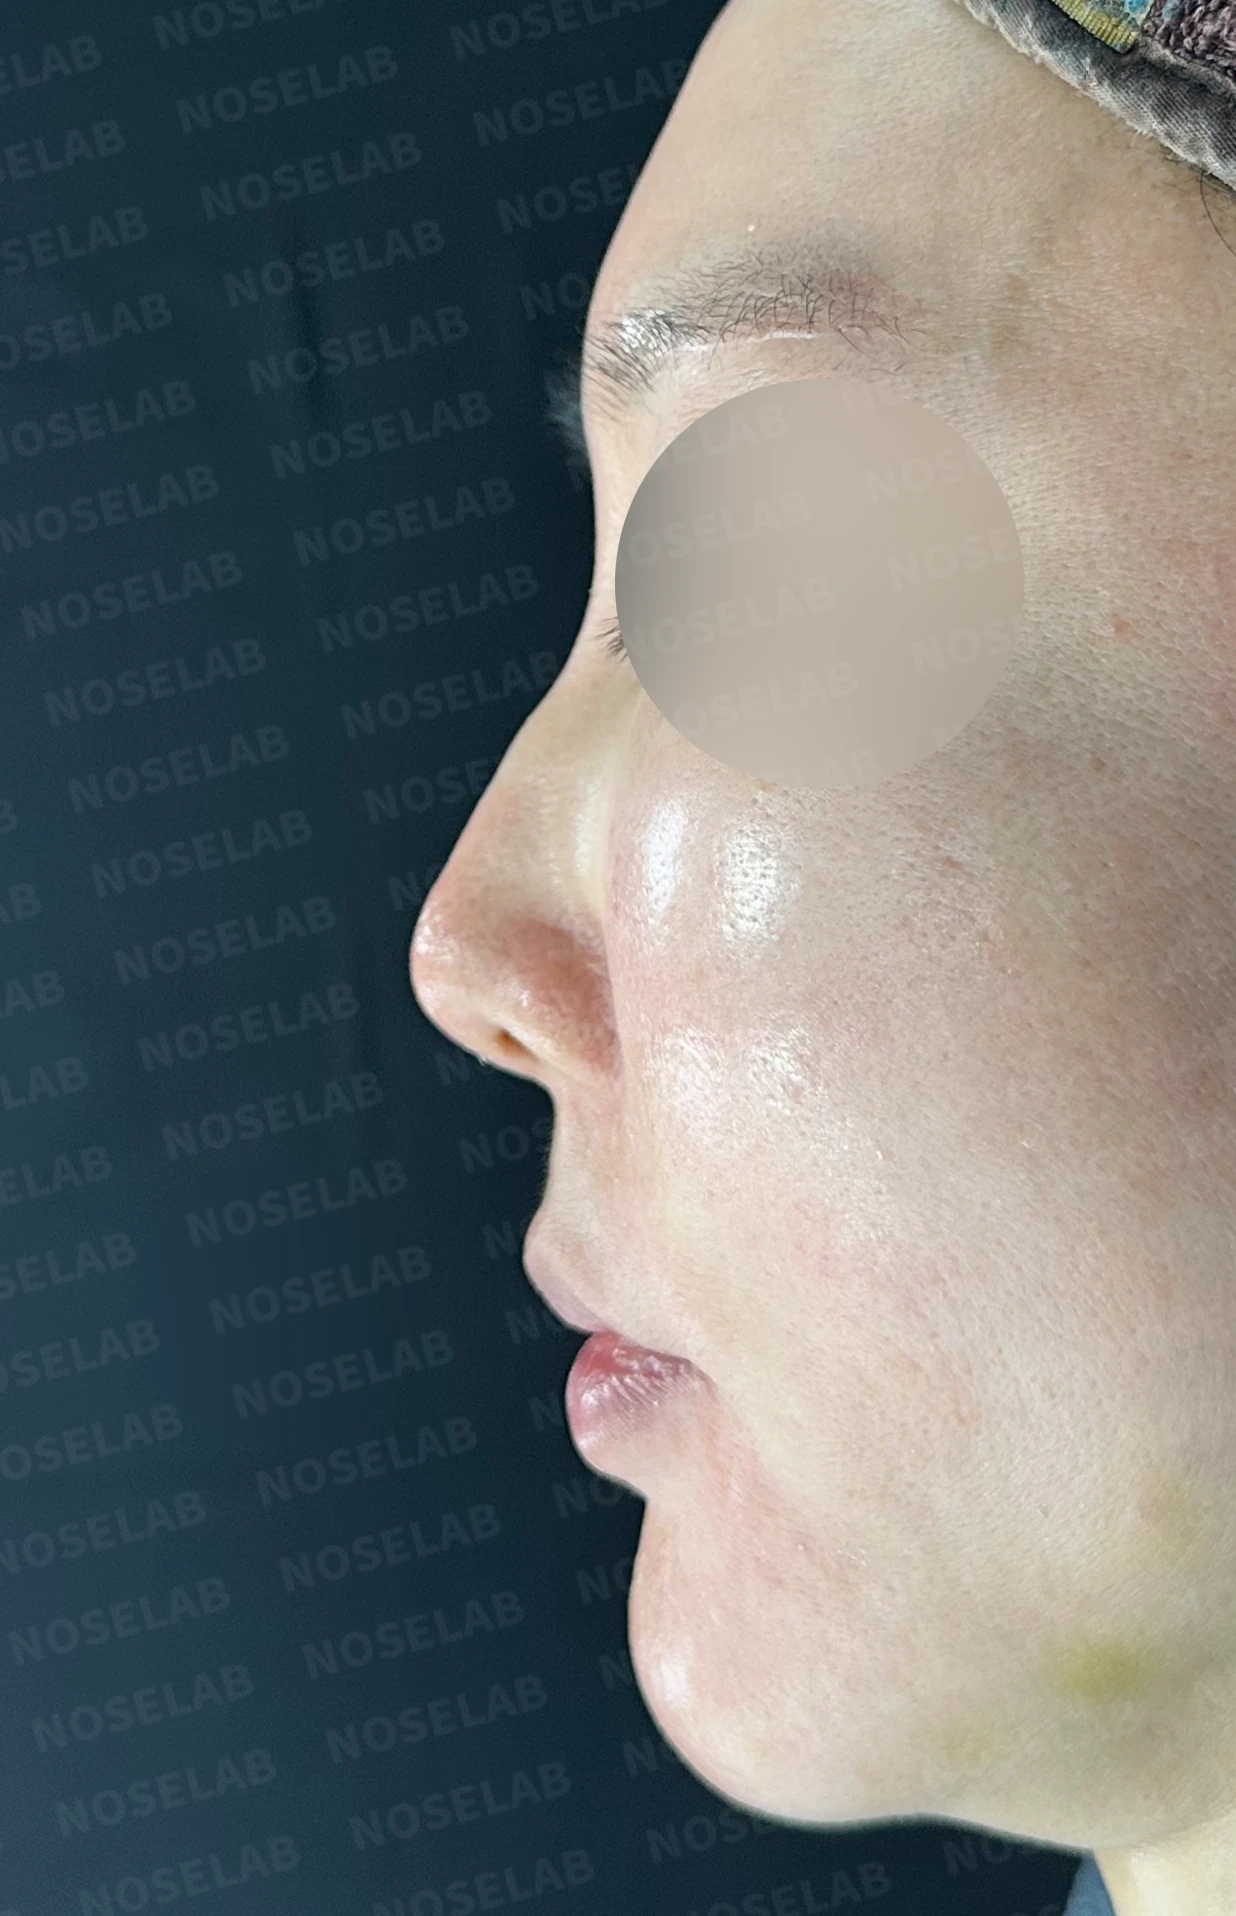
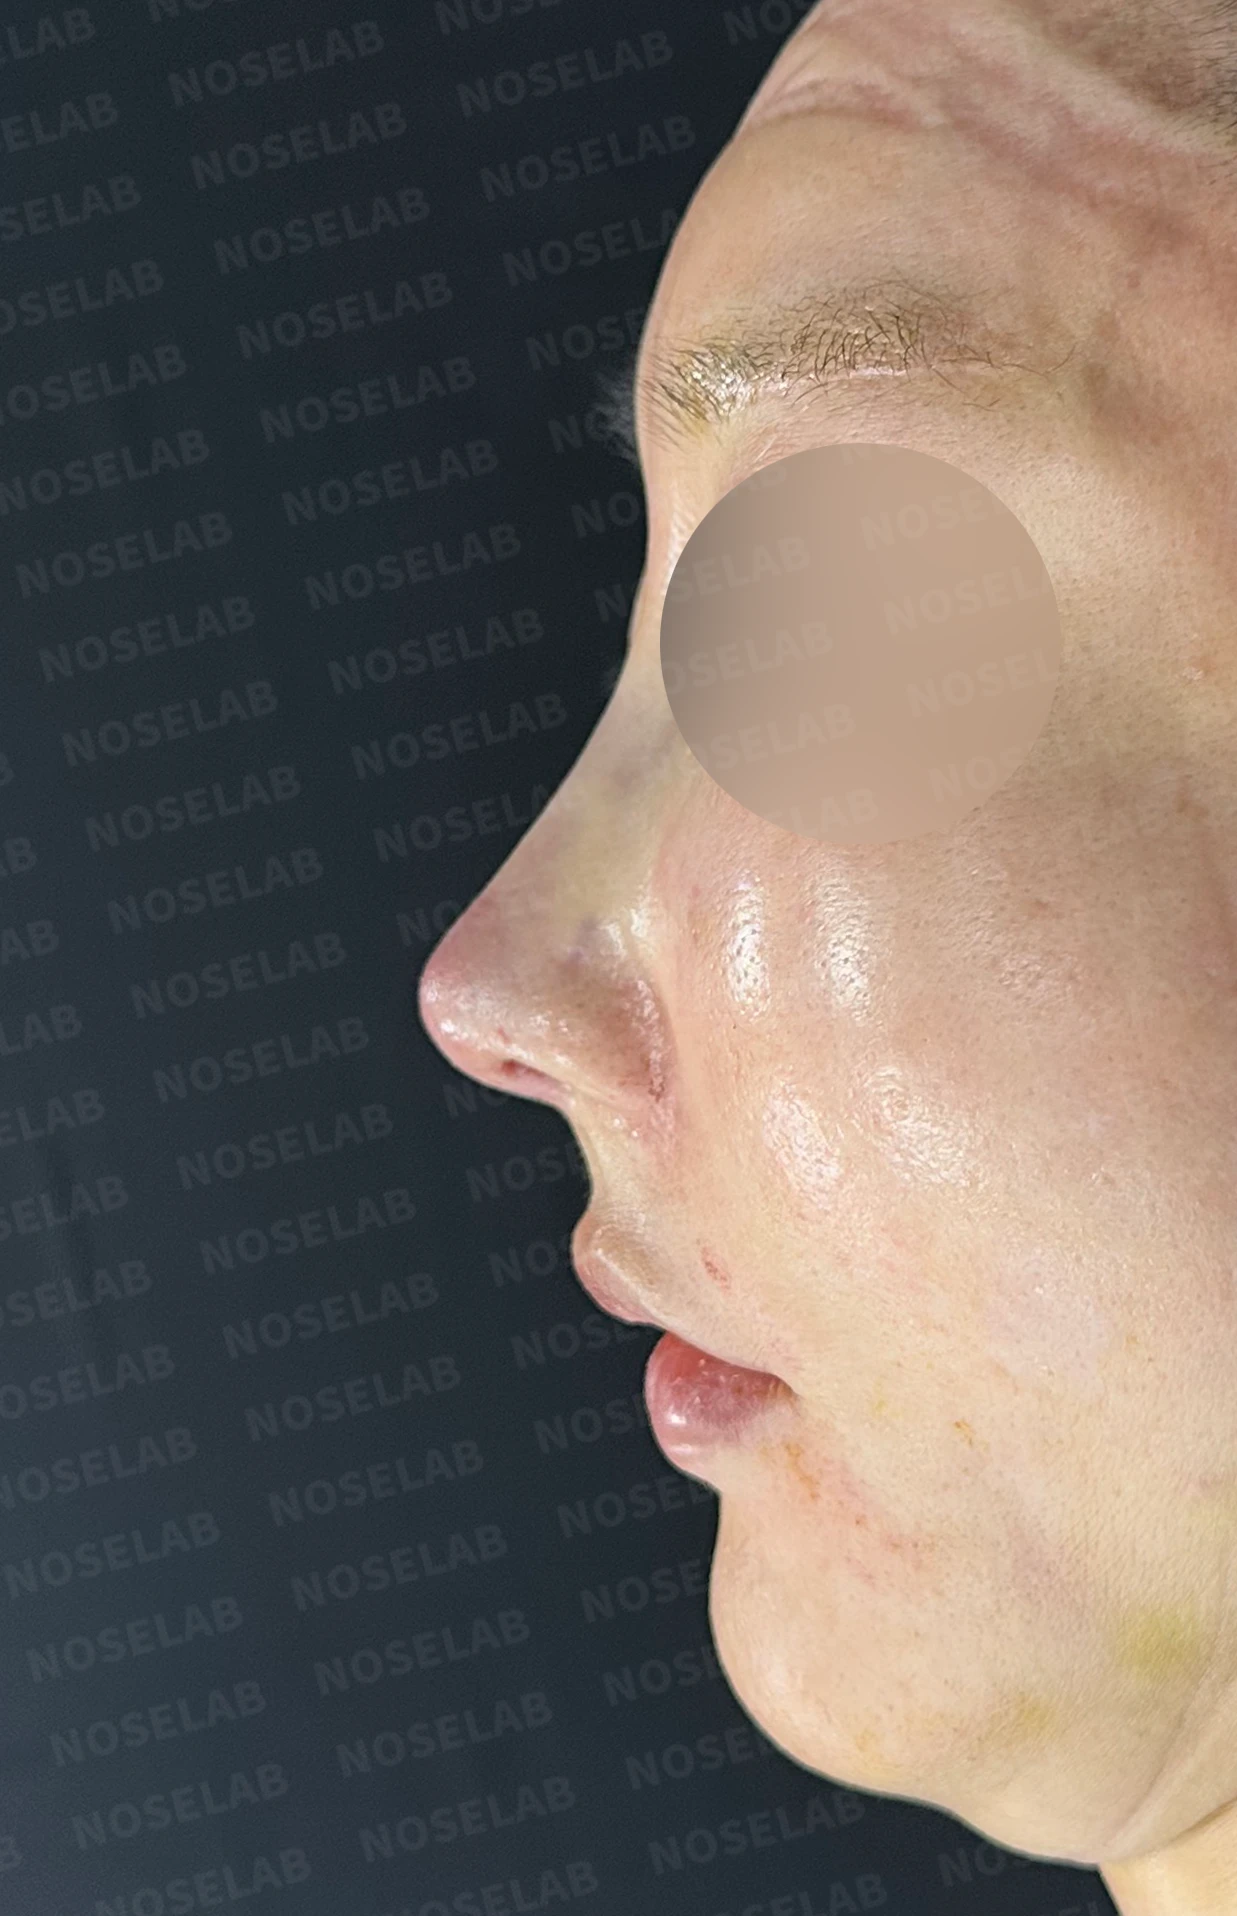
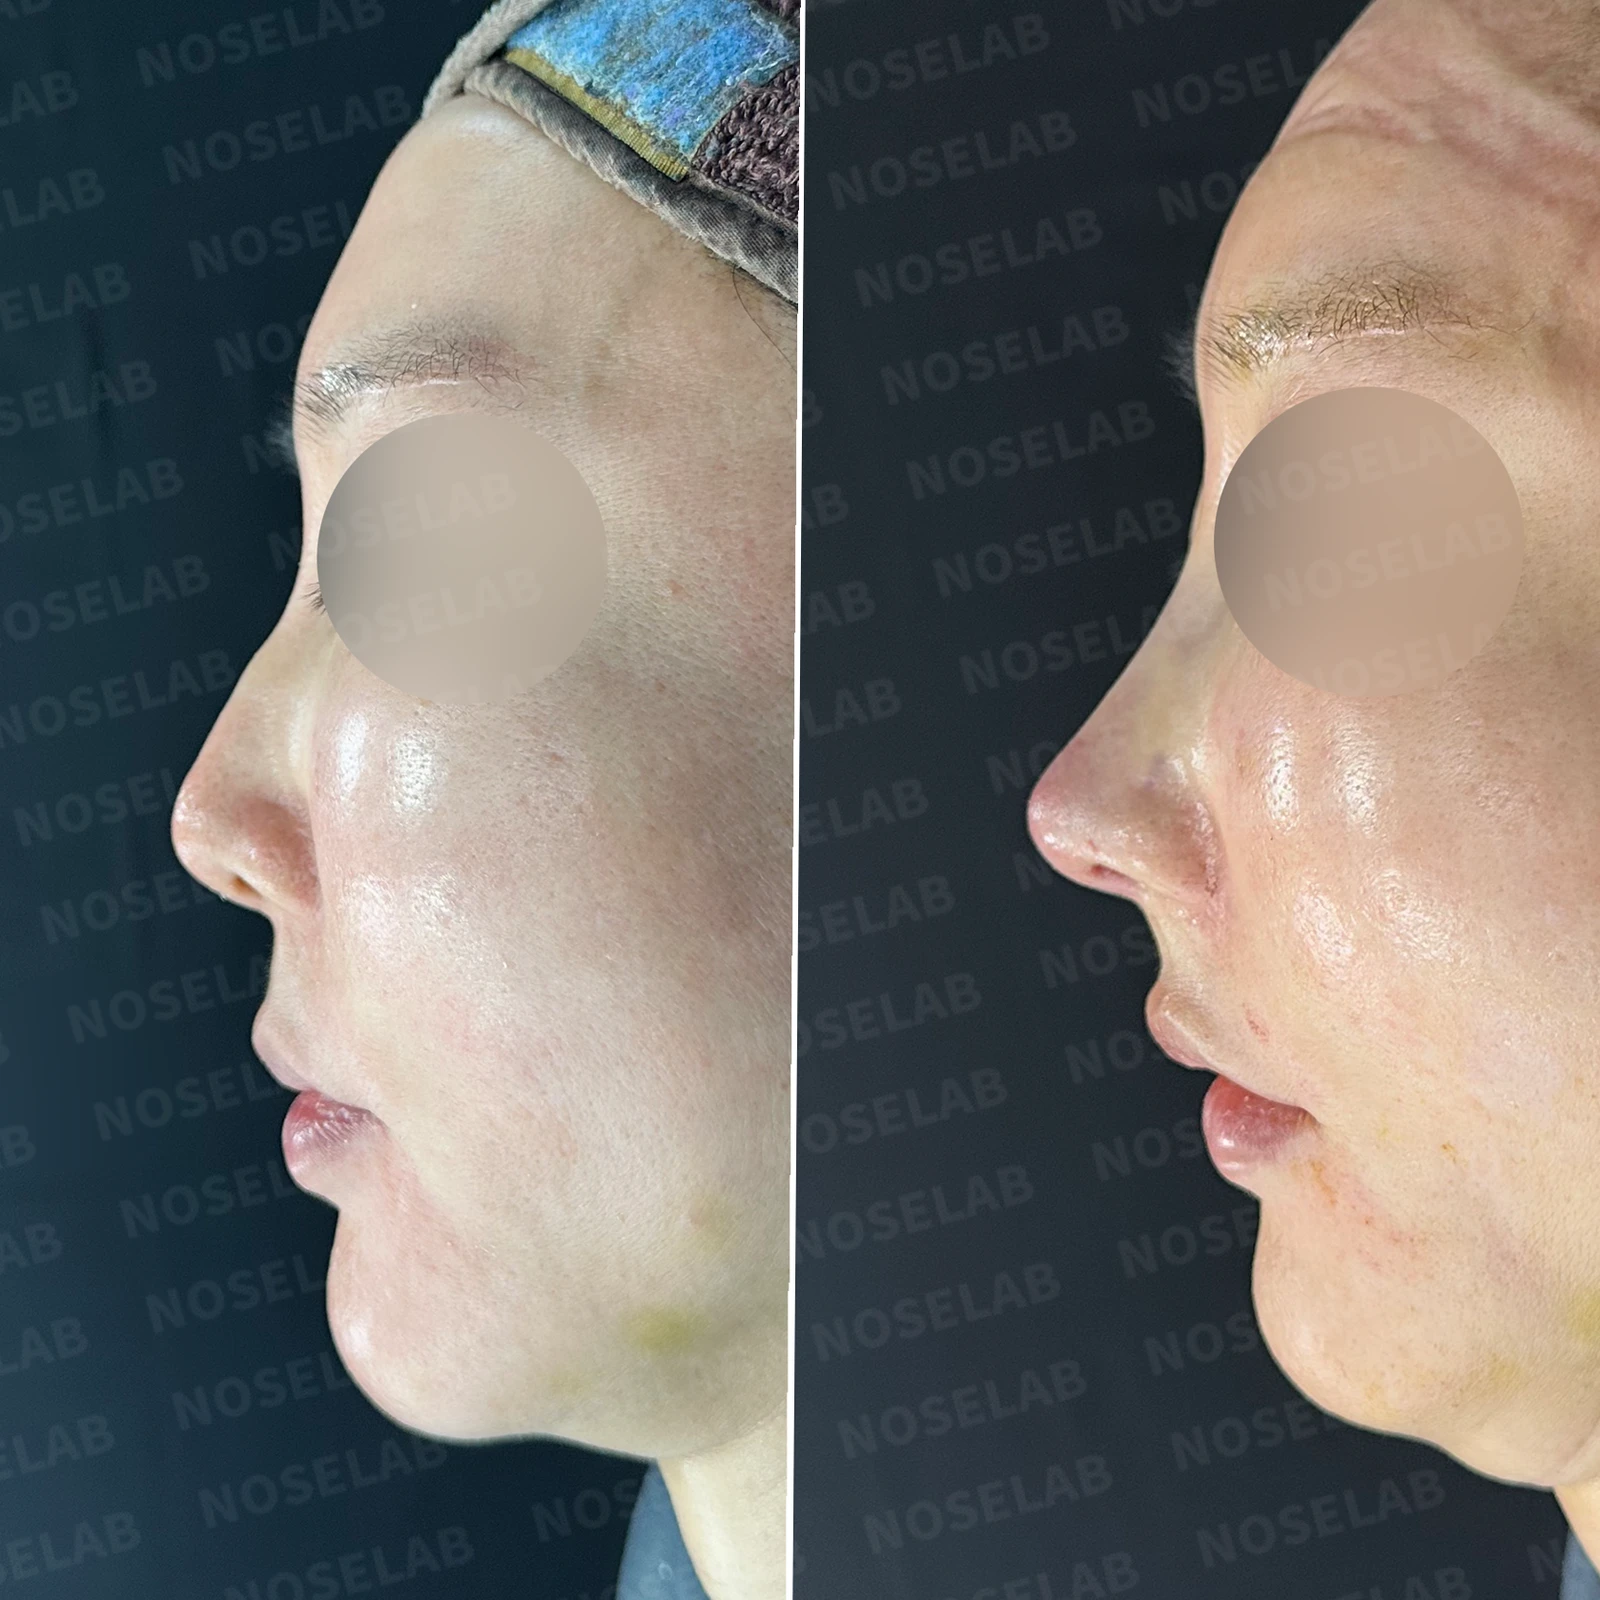
Before surgery / Day 0 immediately after surgery Photos taken immediately after surgery show swelling and may differ from the final result.
Profile view
Naturally elevated nasal bridge
Improved nasolabial angle
The philtrum no longer appears elongated
Dorsal hump reduction
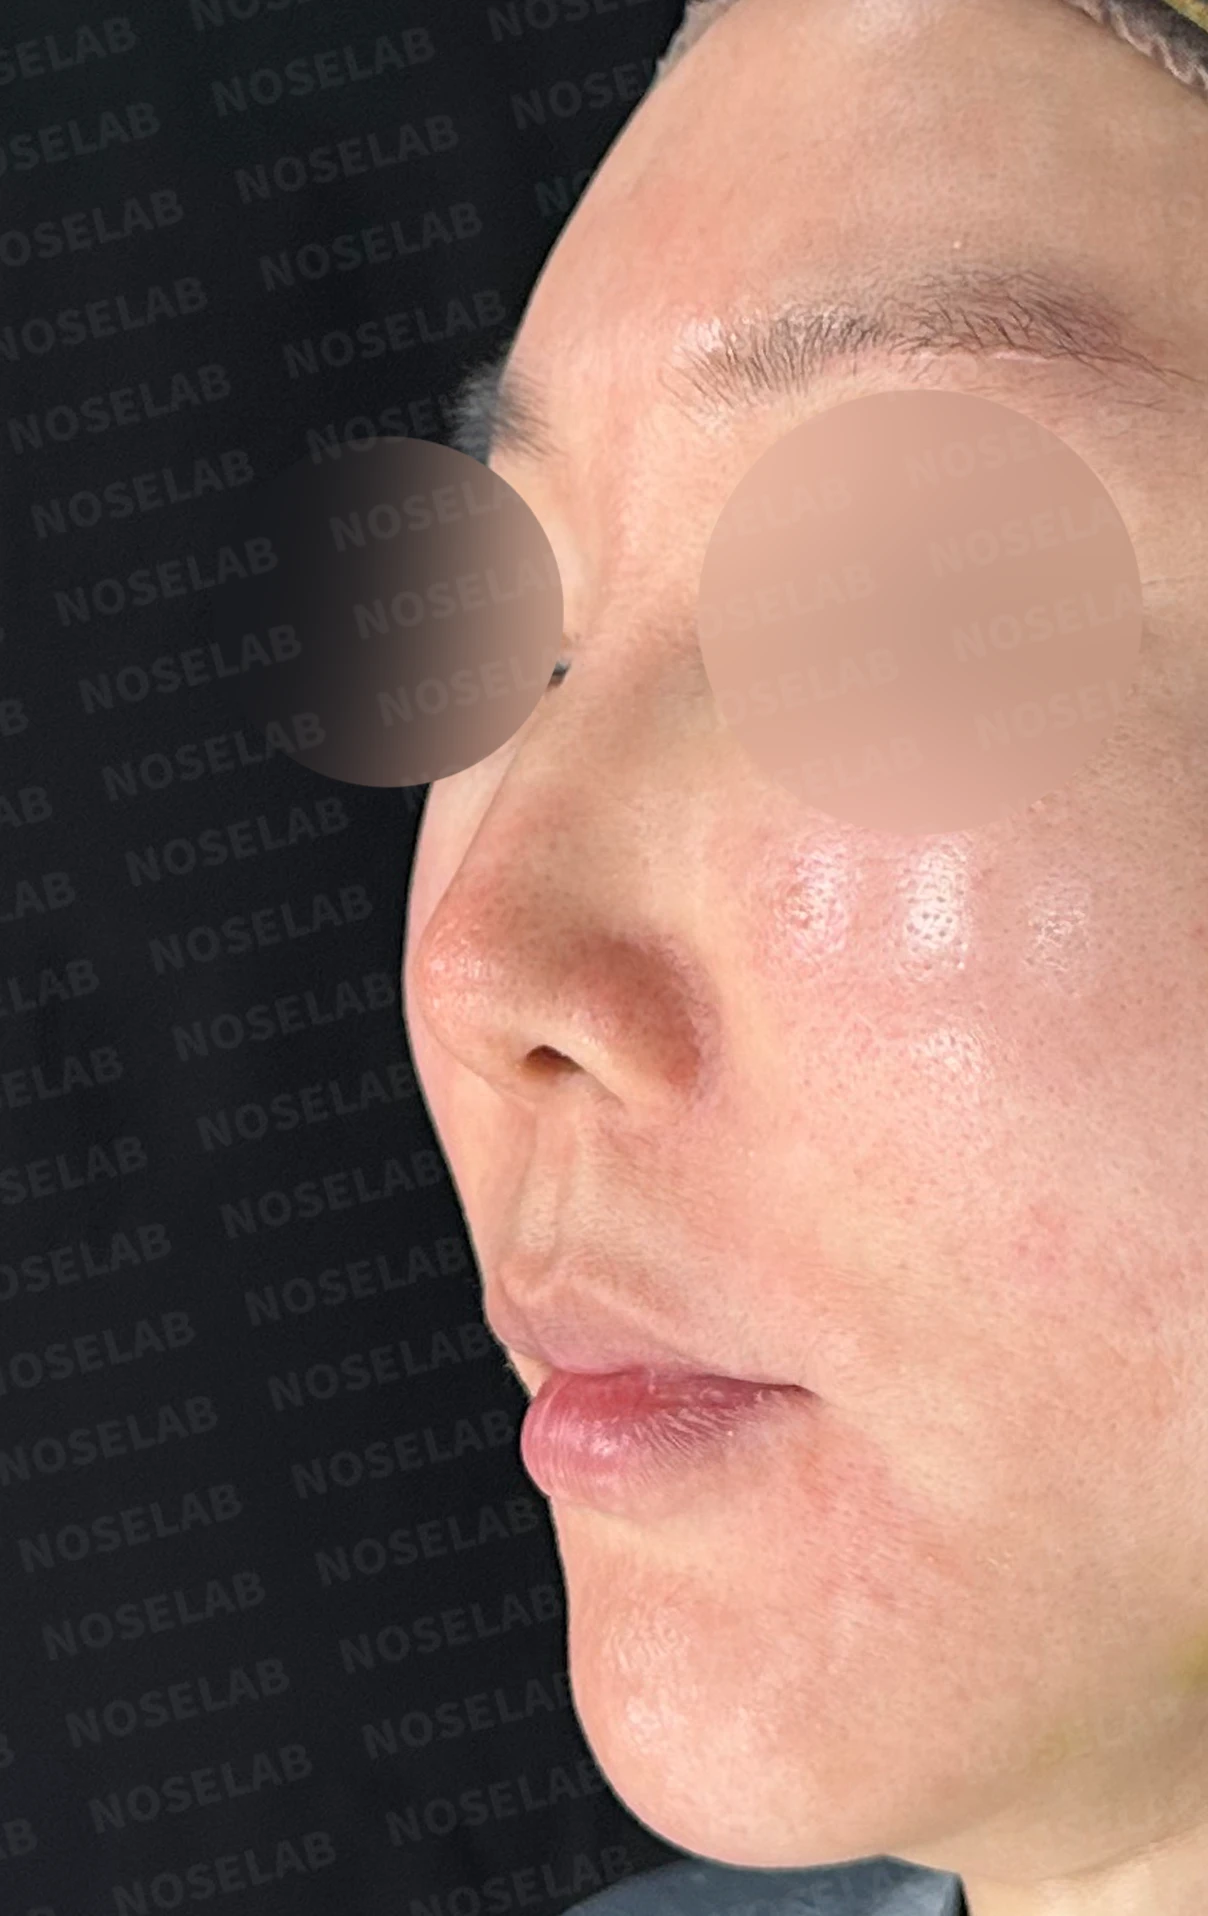
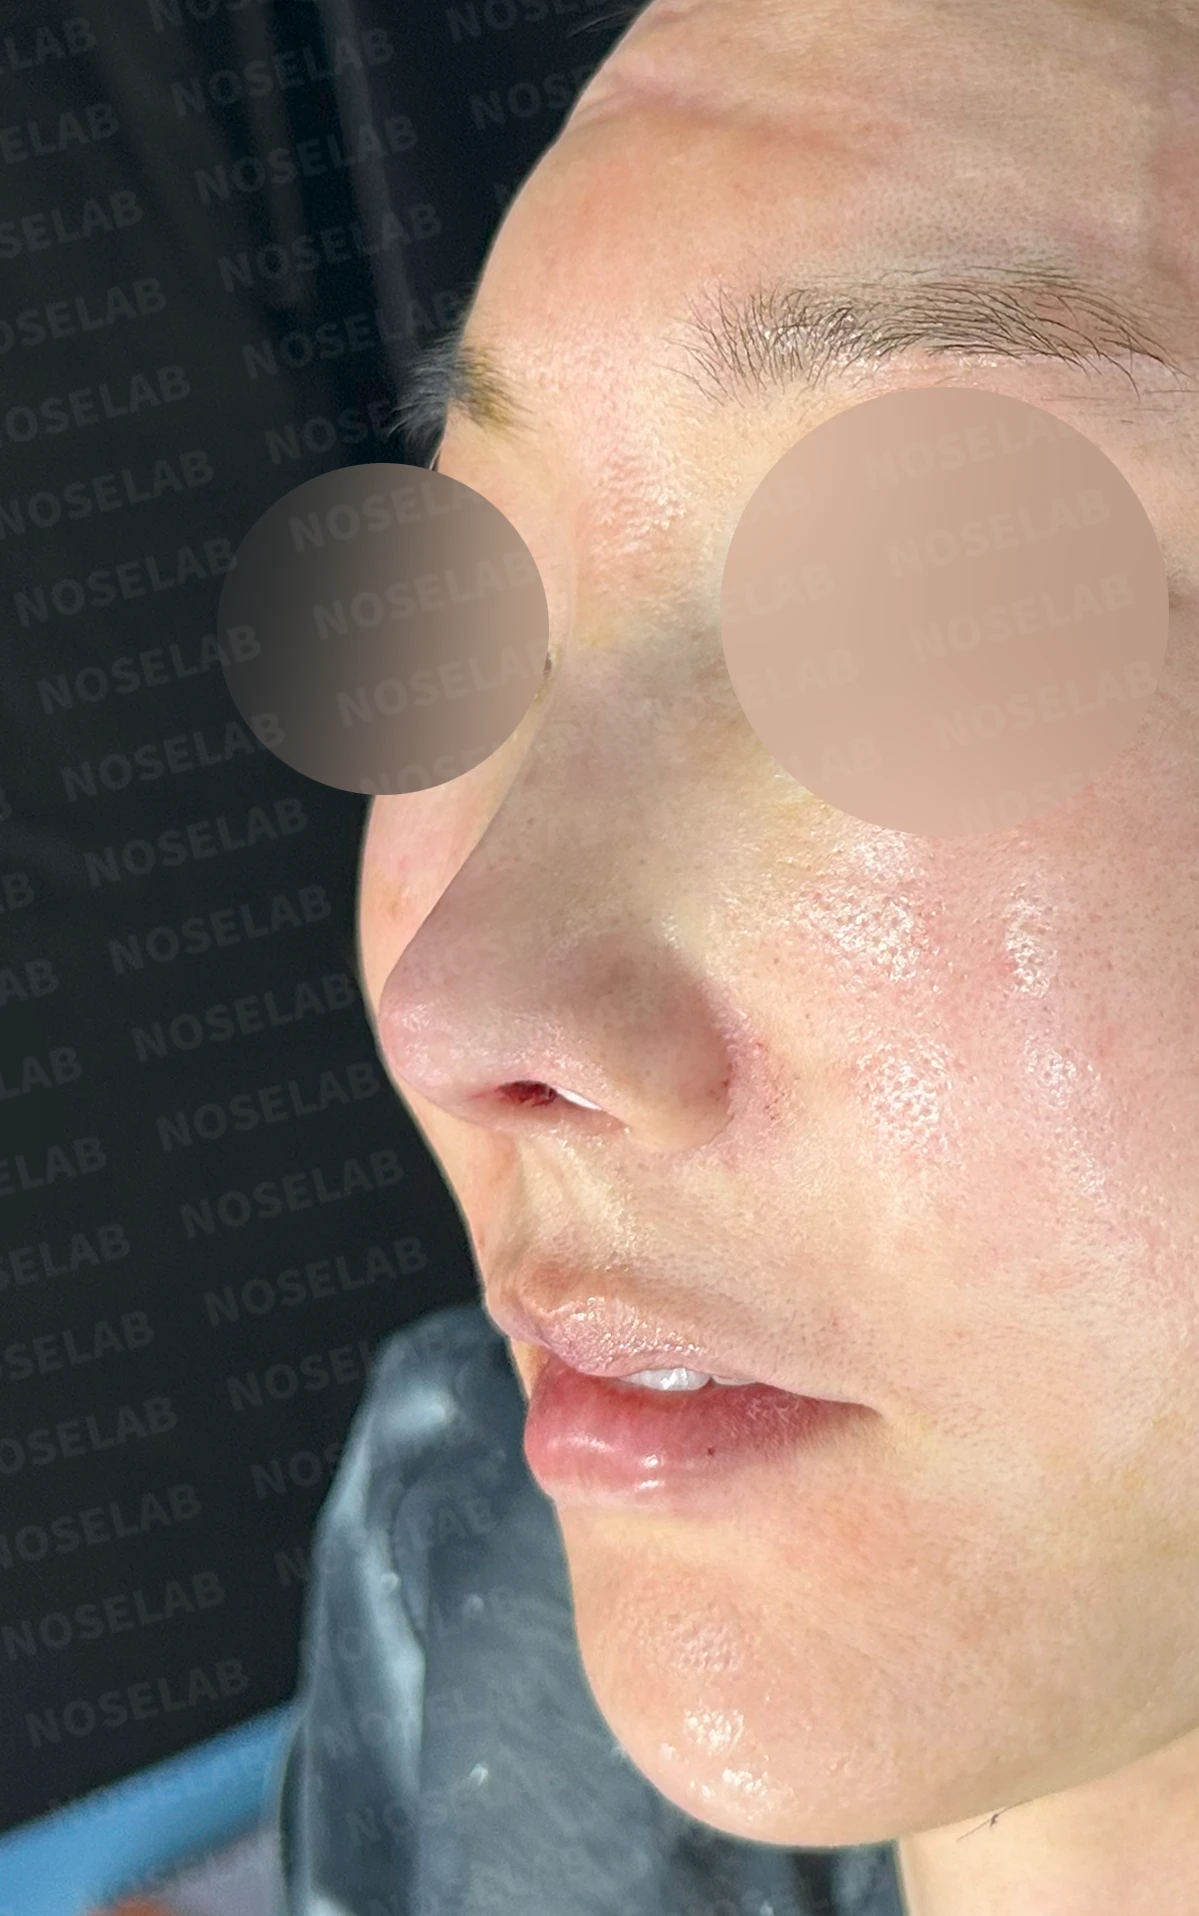
Before surgery / Day 0 immediately after surgery Photos taken immediately after surgery show swelling and may differ from the final result.
Nostrils
Nostril asymmetry is corrected
The tilted columella is straightened
Balanced nostril shape
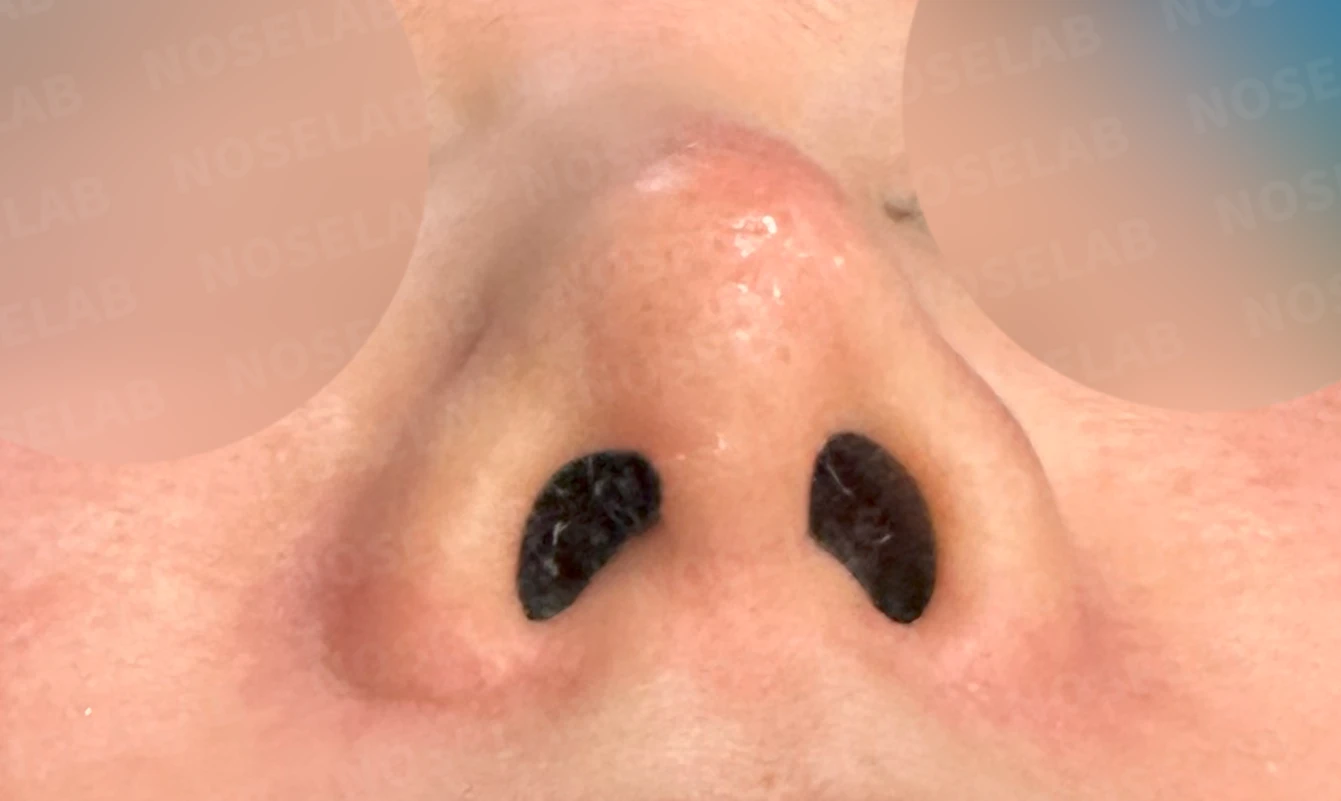
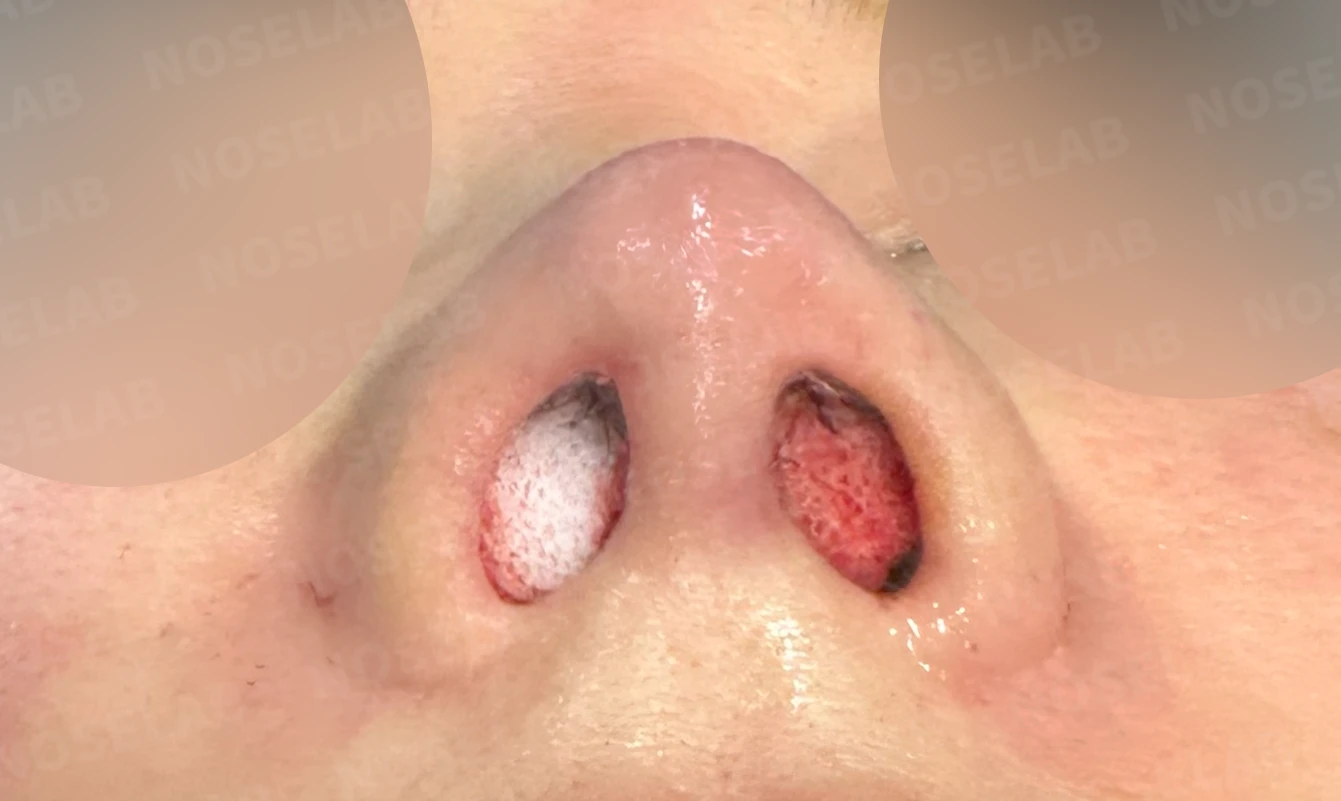
Before surgery / Day 0 immediately after surgery Photos taken immediately after surgery show swelling and may differ from the final result.
👨⚕️ Specialist's assessment
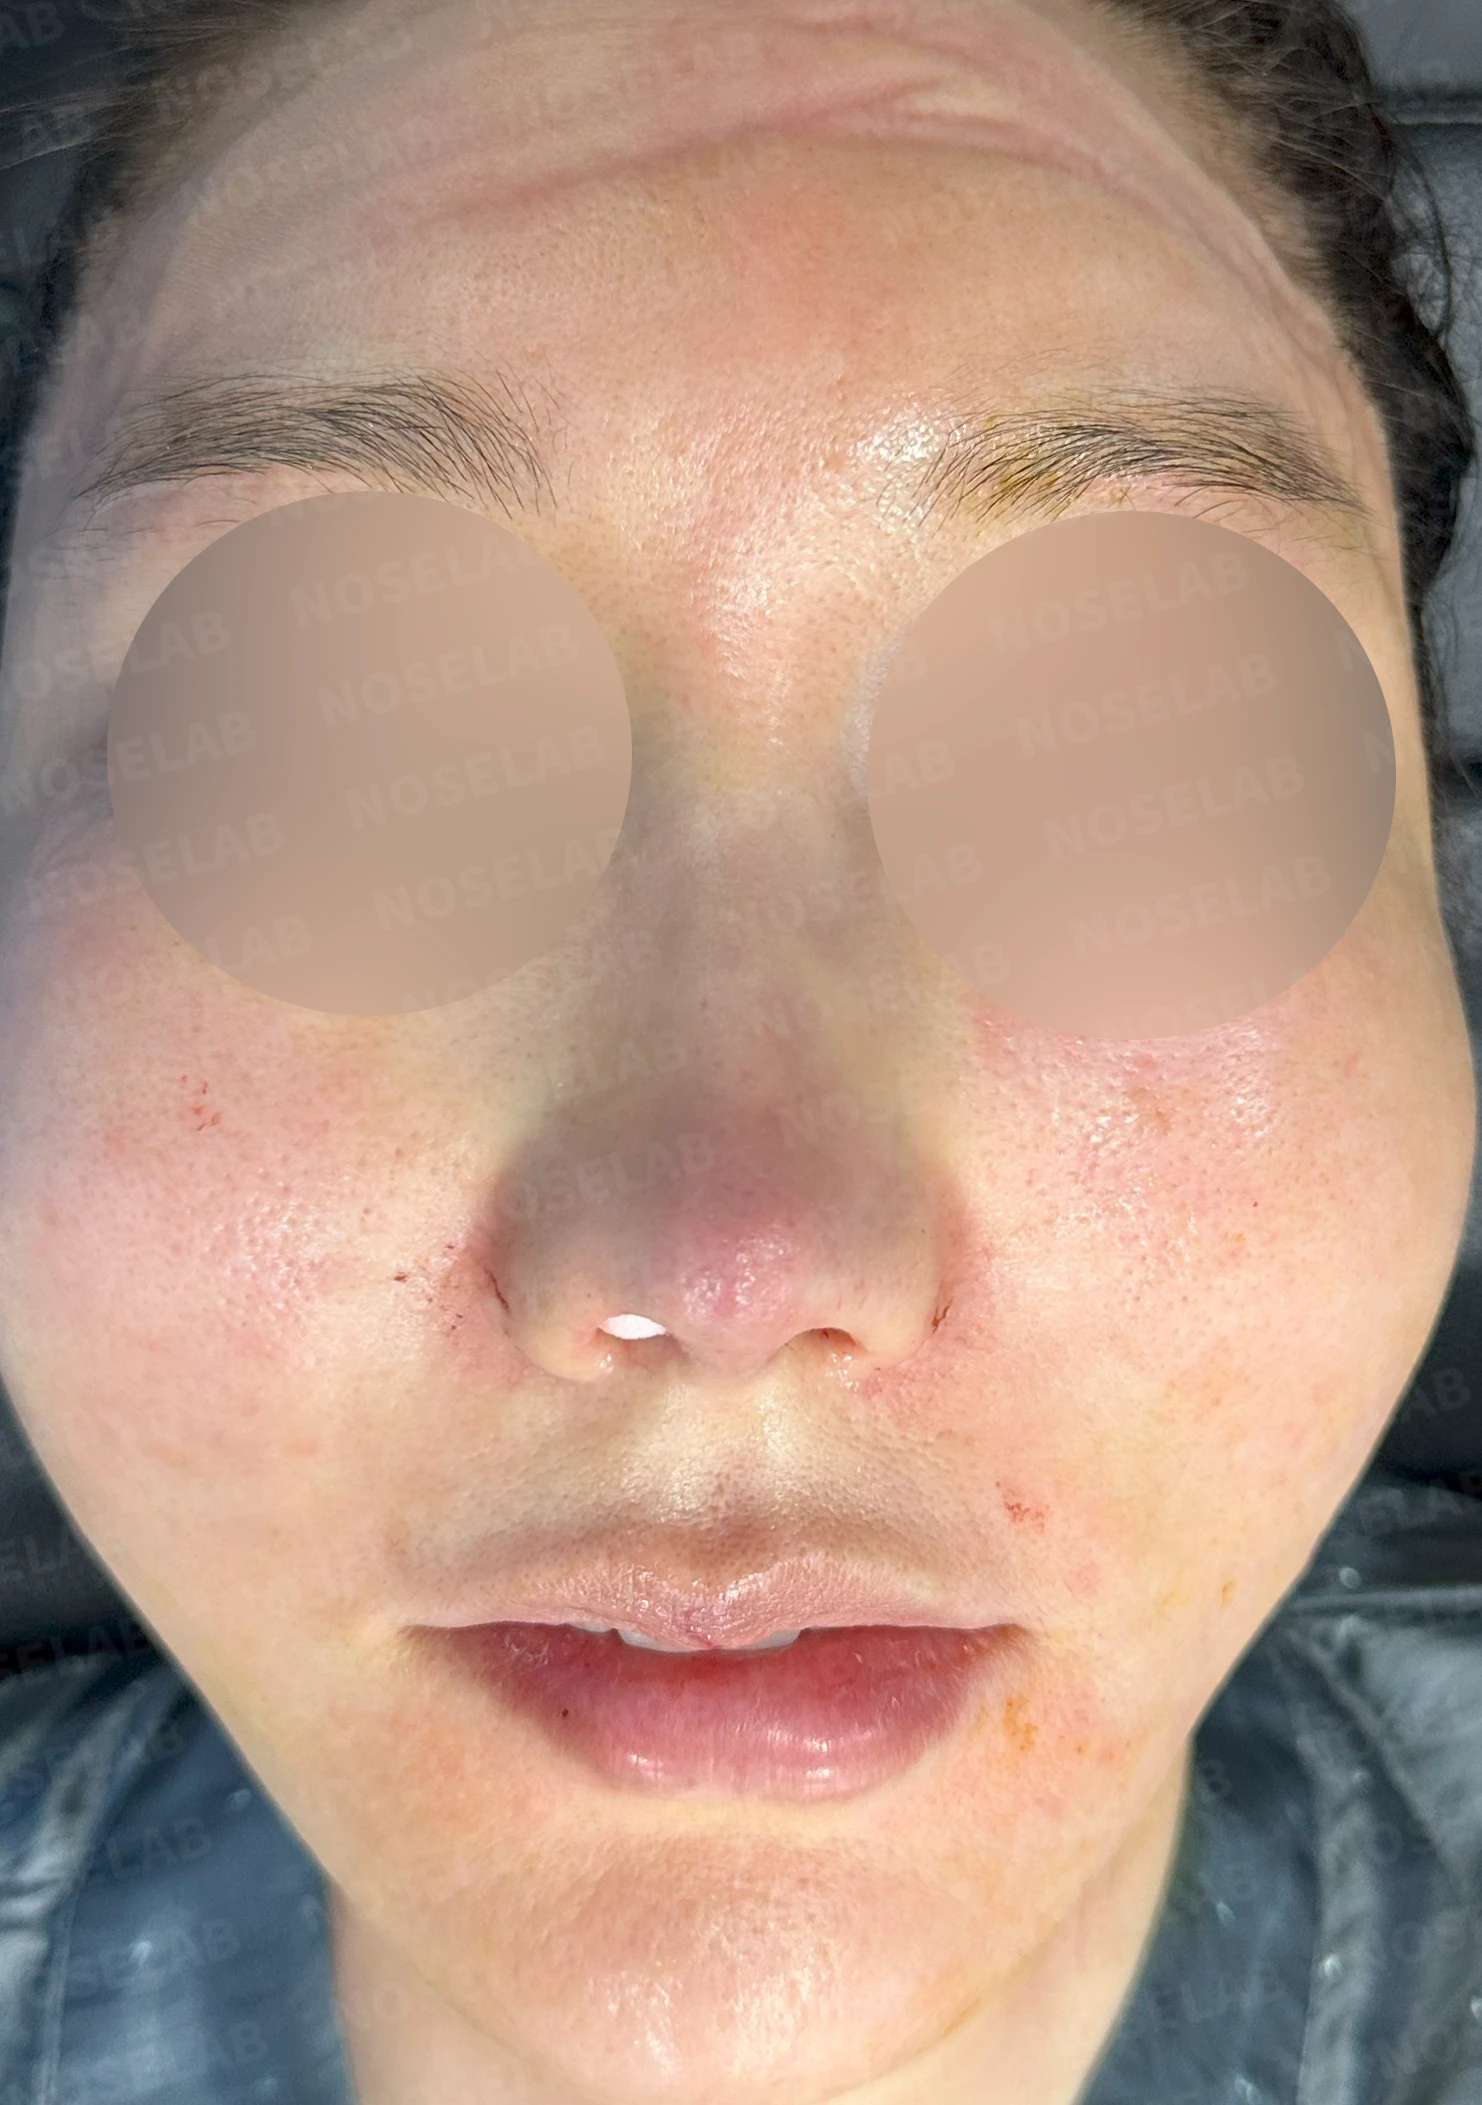
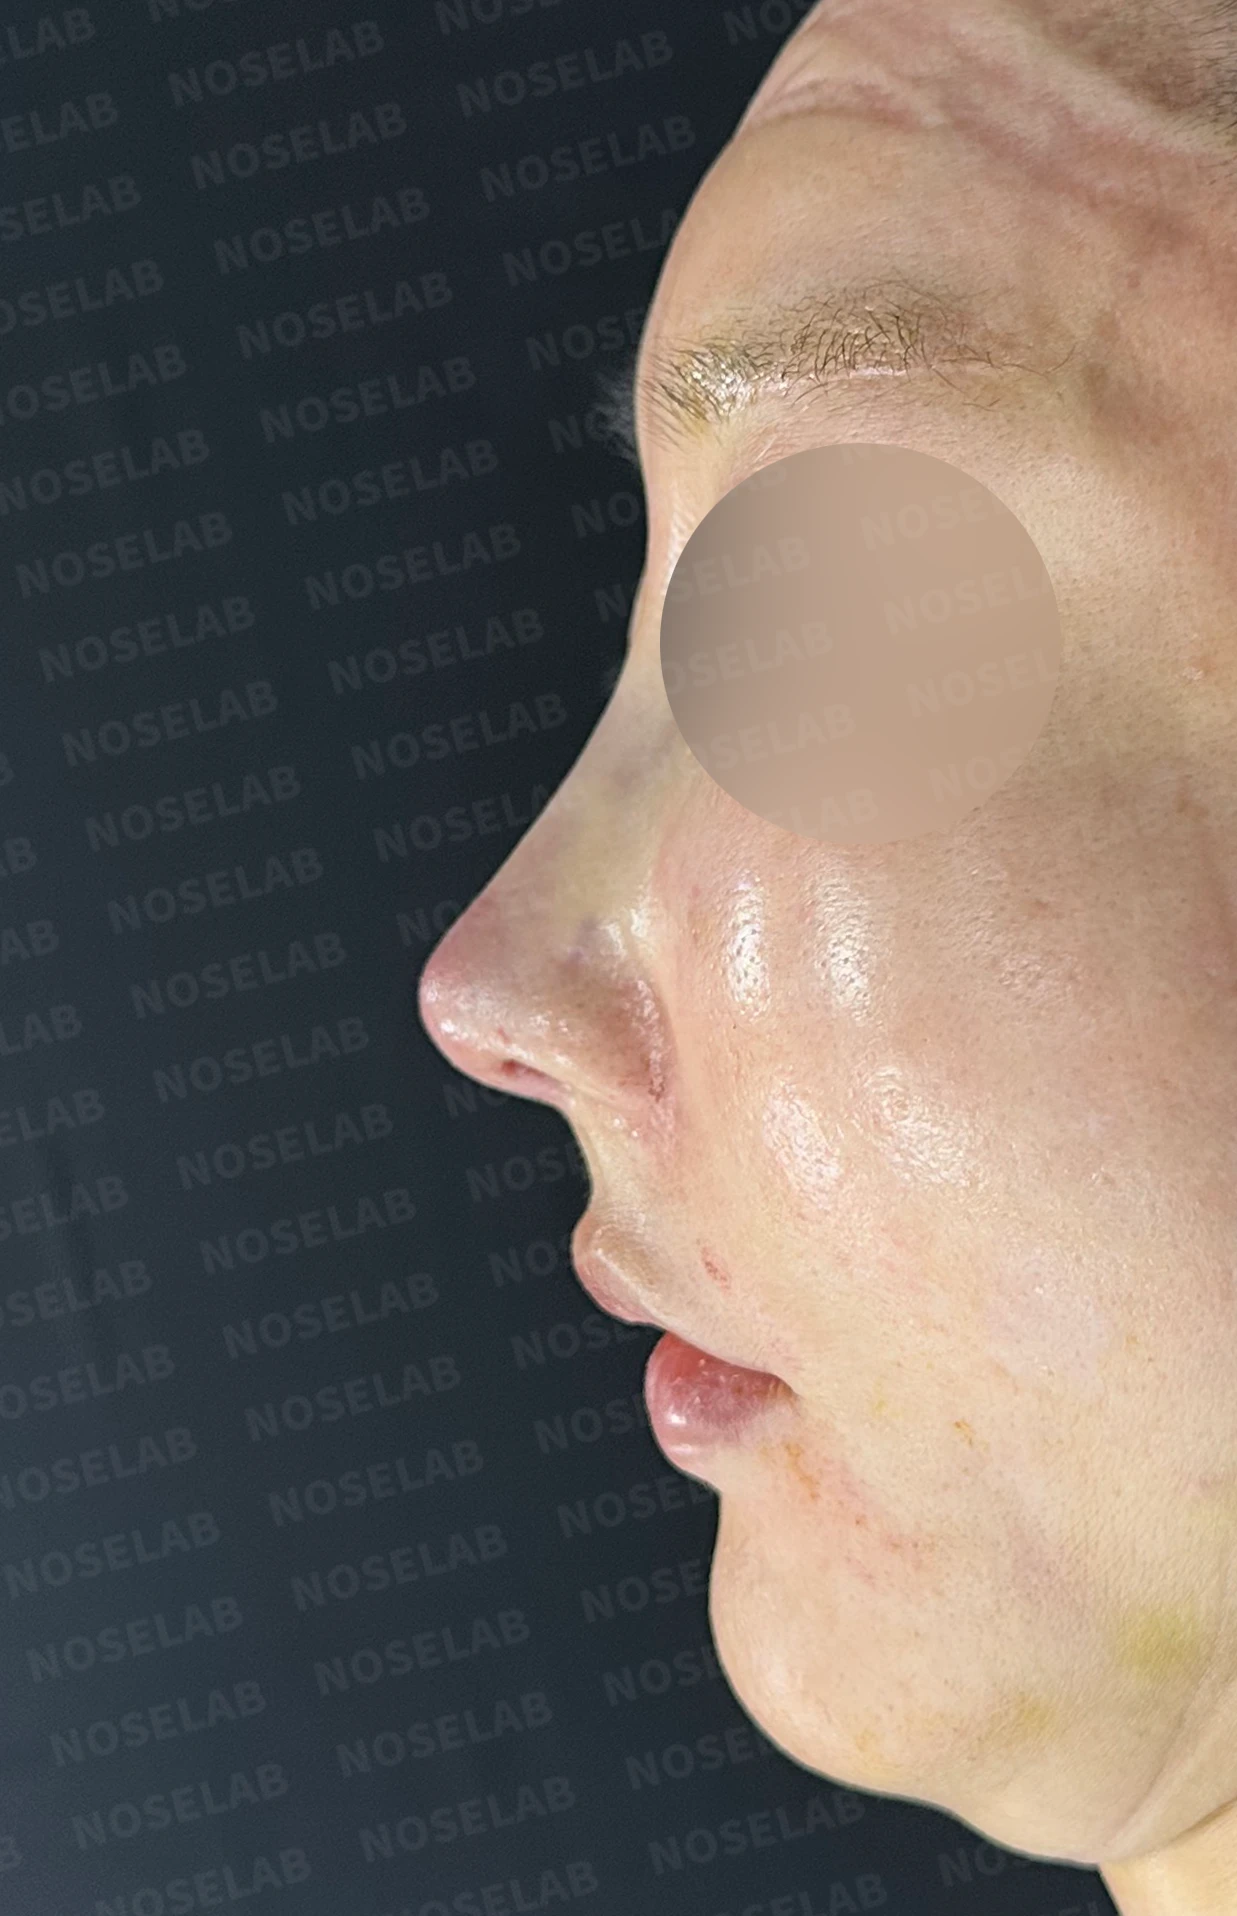
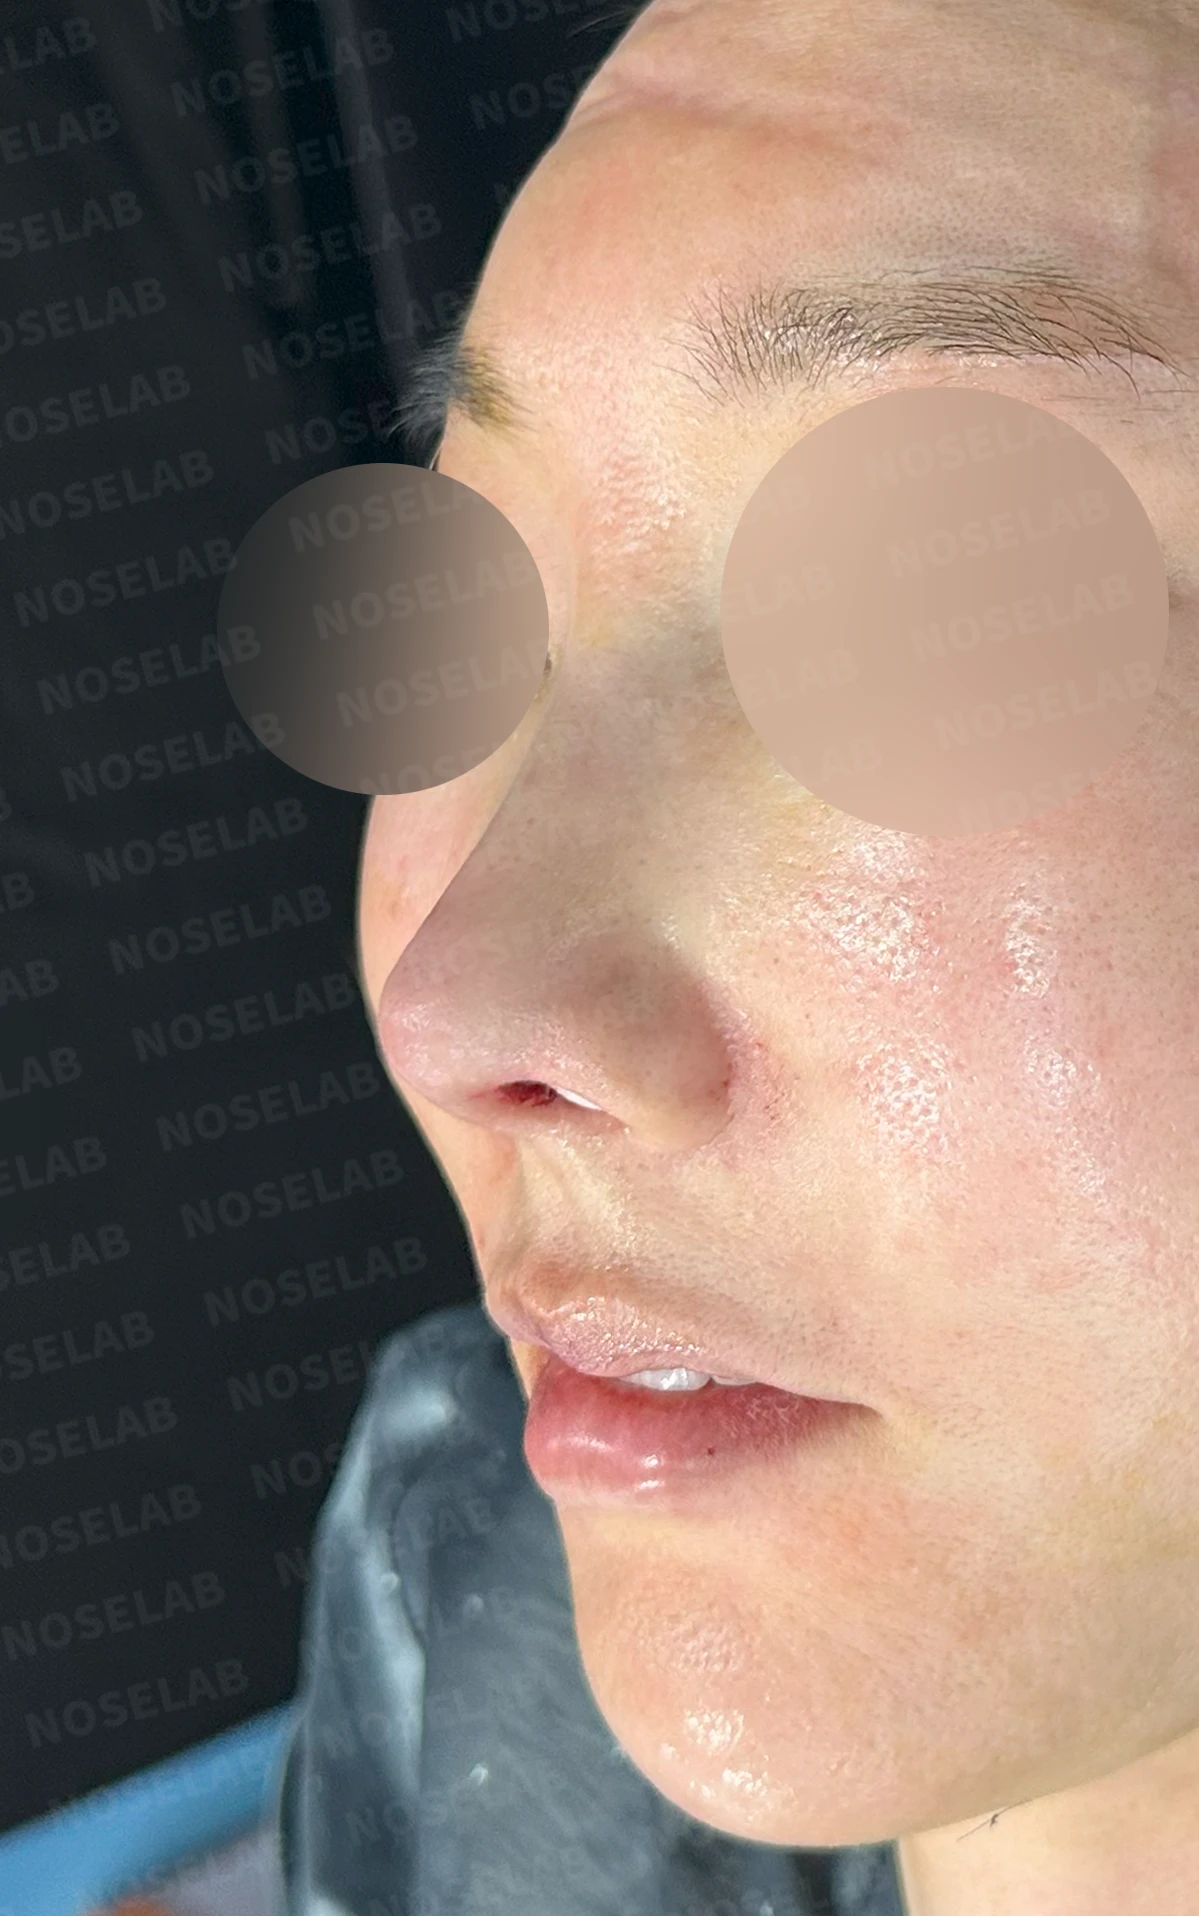
Front, profile, and oblique views immediately after surgery on day 0 Photos taken immediately after surgery show swelling and may differ from the final result.
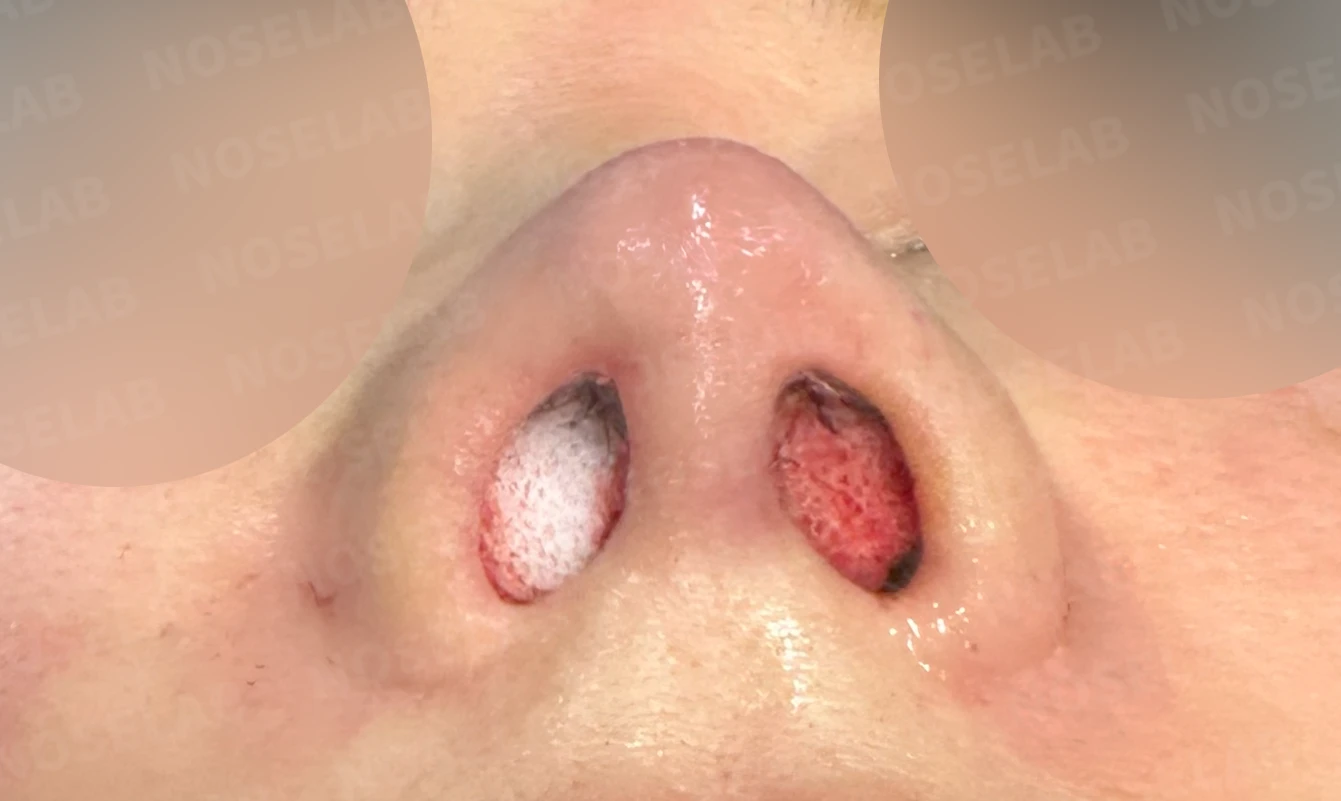
Nostril view on day 0 immediately after surgery Photos taken immediately after surgery show swelling and may differ from the final result.
This case presented complex concerns resulting from dorsal hump surgery 17 years prior and filler treatments 10 years ago. From the front view, the widened, flat nasal contour and excessive nostril show were evident; from the profile view, the drooping tip, obtuse nasolabial angle, and residual dorsal hump were the patient's primary concerns.
The primary focus was to improve the excessive nostril show and achieve a harmonious nasal bridge height. Lowering the nasal tip position effectively improved the excessive nostril show, while septal extension using autologous rib cartilage established a stable, well-balanced nasal framework. Additionally, lateral osteotomies were performed to correct the crooked nose, and completely removing the old filler before rebuilding the structure resolved the preexisting asymmetry.
To fulfill the patient's request for 'a result harmonious with the face,' the height and contour of the nose were carefully balanced with the patient's other facial proportions. Frontal nasal symmetry and nostril balance combined naturally with the harmonious profile height and refined nasolabial angle, improving the overall facial balance.
The residual dorsal hump and excessive nostril show were naturally improved, successfully achieving the look the patient desired without appearing artificial.
This has been Dr. Peter C. Kang, medical director.
Thank you.
#closedrhinoplasty #dorsalhumpcorrection #nostrilcorrection #revisionrhinoplasty #nasolabialanglecorrection #customrhinoplasty

Limitations and risks
When autologous rib cartilage is used, scarring and pain may remain at the donor site on the chest, and pneumothorax (pleural injury) can occur rarely. Over time, the grafted cartilage may warp or undergo partial resorption.
When foreign materials such as injected fillers are removed and reconstructed, contracture may recur, nasal height and length may decrease, and staged surgery may be necessary depending on the skin condition.
When the septum is corrected at the same time, nasal obstruction may persist or recur, and in rare cases, septal perforation or changes in smell may occur.
Common potential risks include infection, bleeding, asymmetry, scarring, skin necrosis, and insufficient improvement; results vary depending on individual skin condition and previous surgical history.